Related Experiment Video
Updated: Jul 12, 2025


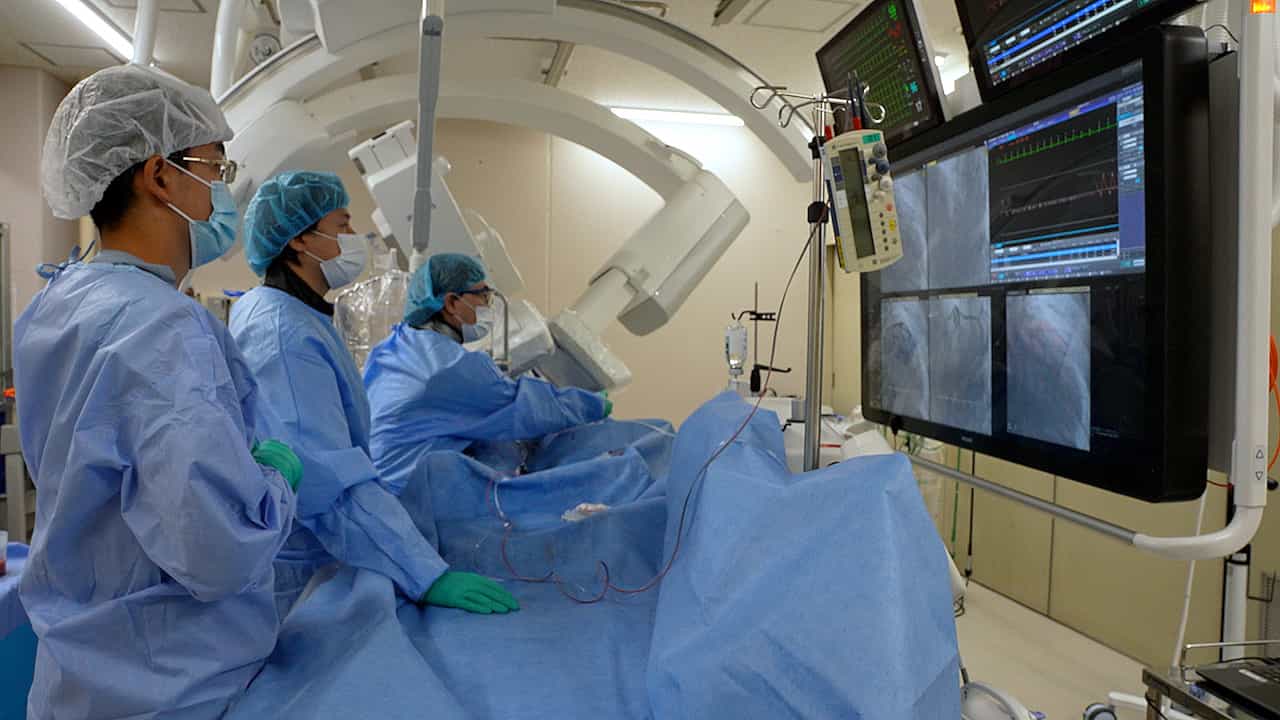
Intracoronary Acetylcholine Provocation Testing for Assessment of Coronary Vasomotor Disorders
Published on: August 18, 2016
Which Coronary Artery Should Be Preferred for Starting the Coronary Spasm Provocation Test?
Hiroki Teragawa1, Yuko Uchimura1, Chikage Oshita1
1Department of Cardiovascular Medicine, JR Hiroshima Hospital, 3-1-36, Futabanosato, Higashi-ku, Hiroshima 732-0057, Japan.

Insights
Initiating the spasm provocation test (SPT) in the left coronary artery (LCA) may lead to a higher incidence of multivessel spasm (MVS), particularly in the left circumflex artery. However, diagnostic rates for vasospastic angina (VSA) and complication frequencies remain similar regardless of the starting vessel.
Area of Science:
- Cardiology
- Diagnostic Testing
- Interventional Cardiology
Background:
- The spasm provocation test (SPT) is crucial for diagnosing vasospastic angina (VSA).
- The optimal artery (right coronary artery or left coronary artery) for initiating SPT remains undetermined.
- This study evaluates SPT outcomes and complications based on the initial vessel choice.
Purpose of the Study:
- To compare the diagnostic yield and complication rates of SPT when initiated in the right coronary artery (RCA) versus the left coronary artery (LCA).
- To investigate the influence of the initial SPT vessel on the occurrence of multivessel spasm (MVS).
Main Methods:
- A cohort of 225 patients undergoing coronary angiography and SPT was analyzed.
- Patients were divided into two groups: SPT initiated in the RCA (n=133) or LCA (n=92).
- Propensity score matching (PSM) was applied to 120 patients for balanced group comparison.
Main Results:
- No significant differences in VSA diagnosis or SPT-related complications were found between RCA and LCA groups initially.
- Spasms occurred most frequently in the left anterior descending artery in both groups.
- The LCA group showed a higher frequency of left circumflex artery spasms and MVS, even after PSM.
Conclusions:
- While VSA diagnostic rates and complication frequencies are comparable, initiating SPT in the LCA increases the likelihood of MVS due to higher rates of left circumflex artery spasm.
- Starting routine SPT from the LCA is suggested based on these findings.
Background:
The spasm provocation test (SPT) is a critical test for diagnosing vasospastic angina (VSA). However, the choice of vessel to be preferred for initiating the SPT-the right coronary artery (RCA) or the left coronary artery (LCA)-is unclear. This study aimed to assess SPT results including SPT-related complications while initiating the SPT in the RCA and LCA.
Methods:
We enrolled 225 patients who underwent coronary angiography and SPTs. The SPT was first performed in the RCA in 133 patients (RCA group) and the LCA in 92 patients (LCA group). We defined VSA as >90% narrowing of the coronary artery during the SPT, accompanied by chest pain and/or ST-T changes on the electrocardiogram. When coronary spasm occurs in two or more major coronary arteries, it is referred to as a multivessel spasm (MVS). SPT-related complications comprised atrial fibrillation, ventricular fibrillation, and unstable hemodynamics following catecholamine use. Analyses using propensity score matching (PSM) were performed in 120 patients.
Results:
No significant differences in the frequencies of VSA and complications were observed between the two groups (RCA: 79% and 19%, respectively; LCA: 85% and 22%, respectively). In both groups, spasms were most frequently provoked in the left anterior descending coronary artery (both p < 0.001) whereas spasms in the left circumflex coronary artery (LCX) were higher in the LCA group than in the RCA group (p = 0.015). Furthermore, no significant difference in the frequency of MVS was observed between both groups (RCA: 50%, LCA: 62%; p = 0.122). After PSM, no significant difference in the frequencies of VSA and complications were observed between the two groups (RCA: 82% and 15%, respectively; LCA: 88% and 18%, respectively). The frequencies of LCX spasms (RCA: 8%, LCA: 23%; p = 0.022) and MVS (RCA: 40%, LCA: 62%; p = 0.020) were higher in the LCA group than in the RCA group.
Conclusions:
Although the diagnostic rate of VSA and frequency of SPT-related complications were similar in the two groups, the frequency of MVS was higher in the LCA group than in the RCA group because of the increase in the number of LCX spasms. A routine SPT may be started from the LCA.

Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Acute Coronary Syndrome I: Introduction
 01:29
Angina III: Clinical Manifestations and Assessment
 01:30
Angina I: Introduction
 01:21
Coronary Circulation
Coronary circulation begins at the base of the aorta, where two main arteries arise—the left and right coronary arteries. These arteries encircle the heart in the coronary sulcus and supply the...
 01:27
Coronary Artery Disease V: Interprofessional Care