Related Experiment Video
Updated: Jul 12, 2025
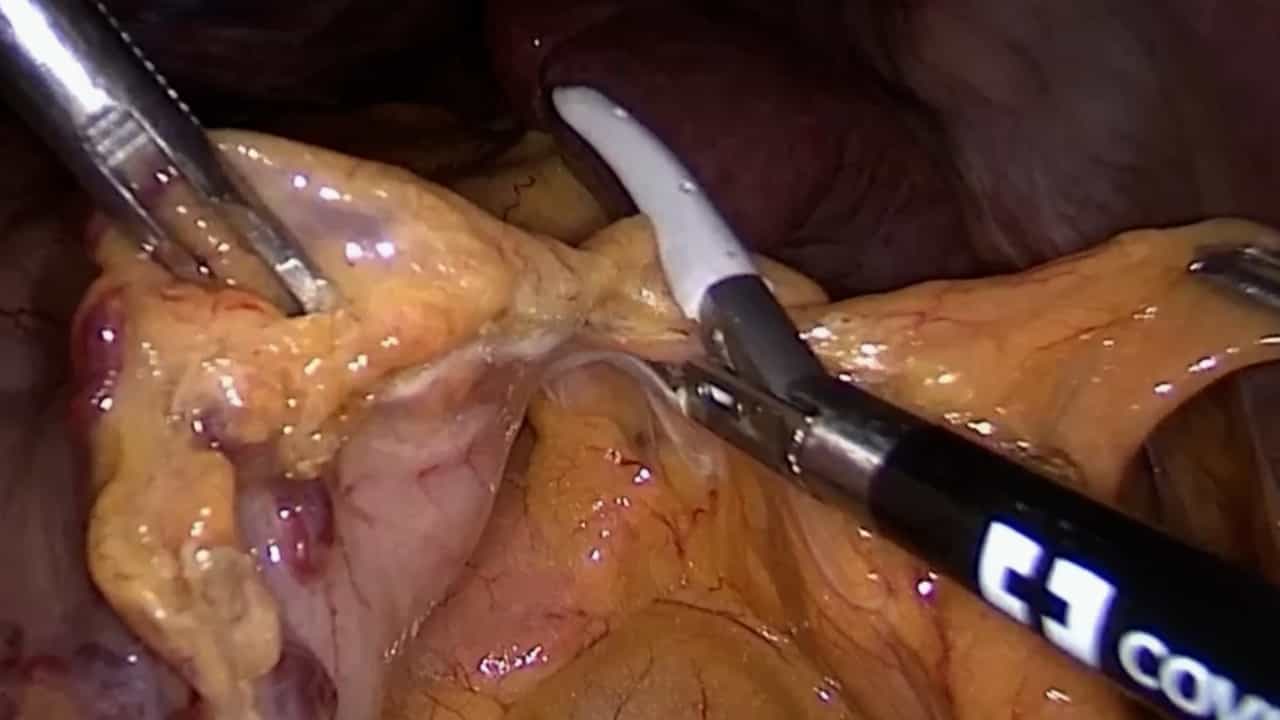

Application of Laparoscopic Partial Splenectomy with Total Blood Flow Occlusion in Benign Splenic Lesions
Published on: December 20, 2024
Impact of Treatment Modalities on Discharge Disposition in Blunt Splenic Injuries
Kimberly Seal1, Bryan Richmond2, Sachin Jain2
1Vascular Surgery, Charleston Area Medical Center, West Virginia University, Charleston, USA.

Background:
Management of blunt splenic trauma has evolved over several decades, trending towards nonoperative management and splenic artery embolization. Extensive research has been conducted regarding the management of blunt splenic injuries, but there is little data on the association of treatment modality with discharge disposition.
Methods:
This is an observational retrospective study conducted at a level-one trauma center with blunt splenic trauma patients of age ≥18 years between January 2010 and December 2021. The primary outcome of unfavorable discharge was defined as discharge to an acute care facility, intermediate care facility, long-term care facility, rehabilitation (inpatient) facility, or skilled nursing facility.
Results:
Five hundred seventy-nine patients were included in the analysis, with 108 (18.7%) in the unfavorable group and 471 (81.3%) in the favorable group. Most patients were managed nonoperatively (69.3%), followed by splenectomy (25.0%) and embolization (5.7%). Due to the low number of embolizations performed during the study period, treatment modalities were grouped into two broad categories: intervention (embolization and splenectomies) and nonintervention. The treatment modality was found to have no significant impact on unfavorable discharge. Independent risk factors for unfavorable discharge included age >55 years, injury severity score (ISS) >15, hospital-acquired pneumonia, and in-hospital complications of sepsis.
Conclusions:
This study provides an understanding of specific demographic and clinical factors that may predispose blunt splenic injury trauma patients to an unfavorable discharge. Providers may apply these data to identify at-risk patients and subsequently adapt the care they provide in an effort to prevent the development of in-hospital pneumonia and sepsis.

Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:29
Venous Thrombosis III: Interprofessional Care
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...