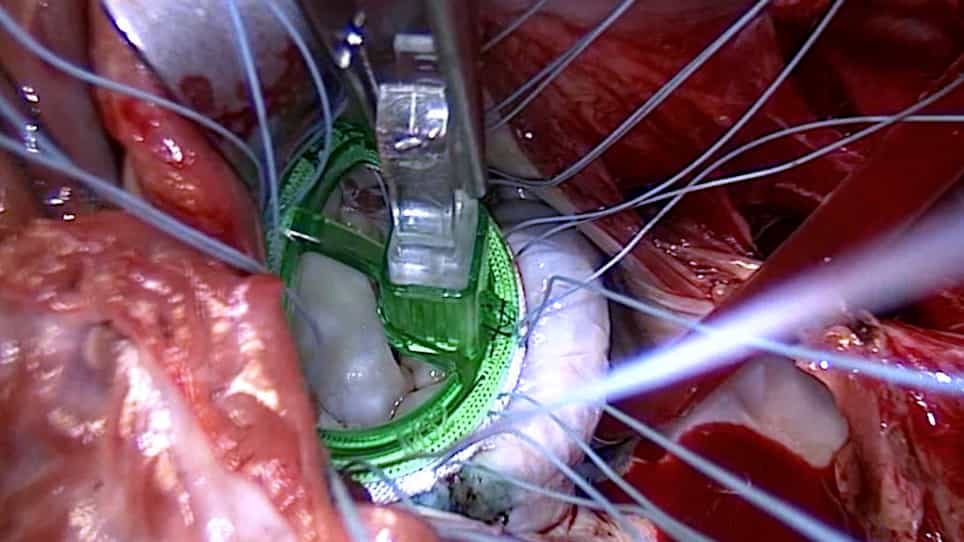
[Mitral valve replacement in patients with obstructive hypertrophic cardiomyopathy]
Related Experiment Video
Updated: Jul 12, 2025
Cox-Maze IV Procedure Concomitant with Valvular Surgery In Situs Inversus Dextrocardia: A Single-Center Experience in China
Published on: February 11, 2022
A V Lysenko1, G I Salagaev1, P V Lednev1
1Petrovsky National Research Center of Surgery, Moscow, Russia.

Insights
Mitral valve replacement is sometimes necessary after septal myectomy for obstructive hypertrophic cardiomyopathy (HCM) if severe mitral insufficiency persists. This involuntary strategy addresses high left ventricular outflow tract pressure gradients.
Area of Science:
- Cardiovascular Surgery
- Cardiology
- Cardiac Valve Disease
Context:
- Obstructive hypertrophic cardiomyopathy (HCM) often involves severe mitral valve insufficiency.
- Surgical intervention aims to relieve left ventricular outflow tract (LVOT) obstruction and address mitral valve issues.
- Chronic heart failure (NYHA class III) is a common presentation in these patients.
Purpose:
- To determine the incidence and etiological factors of mitral valve replacement (MVR) in patients with obstructive HCM.
- To analyze outcomes of surgical correction for LVOT obstruction and mitral valve repair.
Summary:
- A study of 172 patients with obstructive HCM and severe mitral insufficiency found that 12 (7.0%) required mitral valve replacement.
- In 5 cases, MVR was primary due to organic mitral valve lesions; in 7 cases, it was necessitated by ineffective septal myectomy.
- Successful surgical correction of LVOT obstruction and mitral valve repair was achieved in 93.0% of patients.
Impact:
- Mitral valve replacement emerges as an involuntary but necessary strategy when septal myectomy is ineffective in resolving severe mitral insufficiency and high LVOT pressure gradients.
- Findings inform surgical decision-making for complex HCM cases requiring combined LVOT decompression and mitral valve intervention.
Objective:
To analyze the incidence and causes of mitral valve replacement in patients with obstructive hypertrophic cardiomyopathy (HCM).
Material And Methods:
There were 172 patients (98 women and 74 men) with obstructive HCM and severe mitral valve insufficiency between November 2017 and May 2023. All patients complained of chronic heart failure NYHA class III. Surgical correction of left ventricular outflow tract (LVOT) obstruction and mitral valve repair with elimination of systolic anterior motion were technically successful in 160 (93.0%) patients.
Results:
The need for mitral valve replacement was noted in 12 (7.0%) patients. Mean cardiopulmonary bypass time was 83.5±19.2 min (94; 127), aortic cross-clamping - 62.8±14.3 min (70; 102). In 5 cases, primary mitral valve replacement was scheduled due to obvious organic lesion of the mitral valve (tearing of chords, rheumatic lesion with leaflet restriction). In 7 patients, valve replacement was forced after ineffective primary septal myectomy (LVOT pressure gradient, severe mitral insufficiency).
Conclusion:
Mitral valve replacement is an involuntary strategy after ineffective myectomy with severe mitral insufficiency and high LVOT pressure gradient.


Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Cardiomyopathy V: Interprofessional Care
 01:26
Mitral Stenosis III: Medical Management
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:22
Mitral Valve Prolapse II: Assessment and Management
 01:25
Mitral Regurgitation III: Medical Management