Related Experiment Video
Updated: Jul 11, 2025
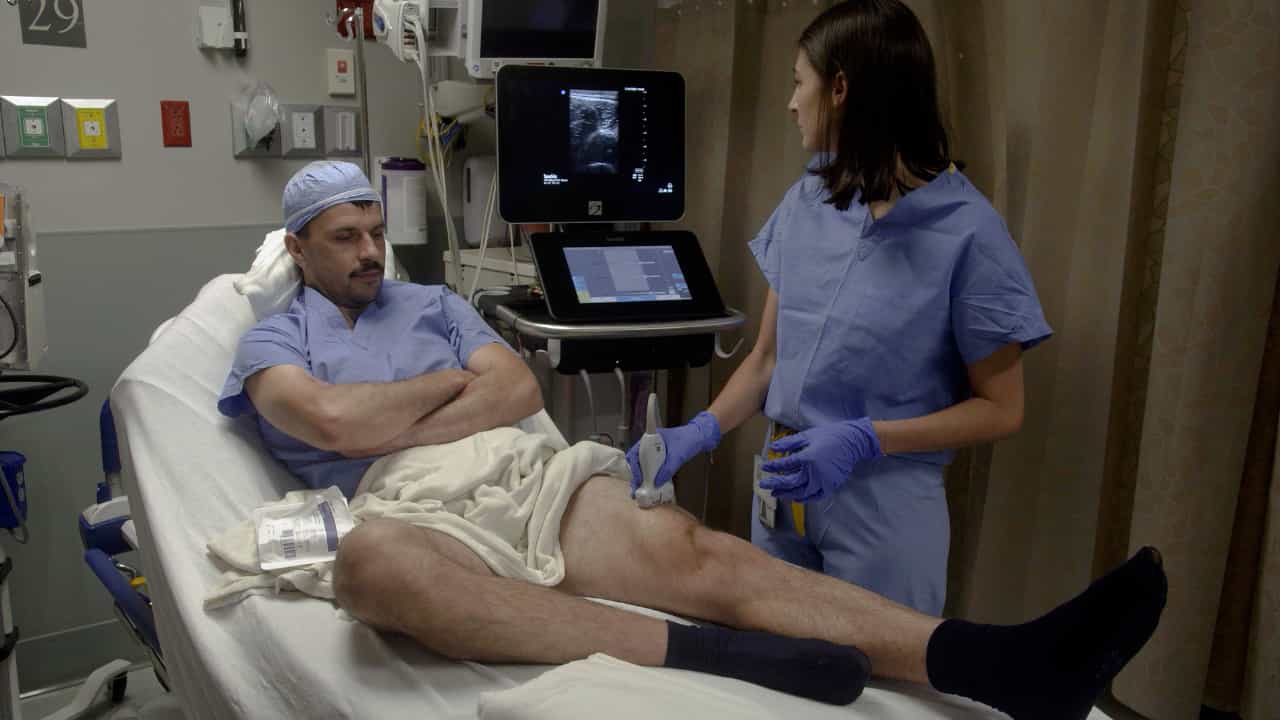
Author Spotlight: Assessing Surgical Frailty with Point-of-Care Ultrasound of Quadriceps Muscles
Published on: July 26, 2024
The Association of Frailty and Neighborhood Disadvantage with Emergency Department Visits and Hospitalizations in
Kristin M Lenoir1,2,3, Rajib Paul4, Elena Wright5,6
1Department of Biostatistics and Data Science, Division of Public Health Sciences, Wake Forest University School of Medicine, Winston-Salem, NC, USA. klenoir@wakehealth.edu.

Background:
Risk stratification and population management strategies are critical for providing effective and equitable care for the growing population of older adults in the USA. Both frailty and neighborhood disadvantage are constructs that independently identify populations with higher healthcare utilization and risk of adverse outcomes.
Objective:
To examine the joint association of these factors on acute healthcare utilization using two pragmatic measures based on structured data available in the electronic health record (EHR).
Design:
In this retrospective observational study, we used EHR data to identify patients aged ≥ 65 years at Atrium Health Wake Forest Baptist on January 1, 2019, who were attributed to affiliated Accountable Care Organizations. Frailty was categorized through an EHR-derived electronic Frailty Index (eFI), while neighborhood disadvantage was quantified through linkage to the area deprivation index (ADI). We used a recurrent time-to-event model within a Cox proportional hazards framework to examine the joint association of eFI and ADI categories with healthcare utilization comprising emergency visits, observation stays, and inpatient hospitalizations over one year of follow-up.
Key Results:
We identified a cohort of 47,566 older adults (median age = 73, 60% female, 12% Black). There was an interaction between frailty and area disadvantage (P = 0.023). Each factor was associated with utilization across categories of the other. The magnitude of frailty's association was larger than living in a disadvantaged area. The highest-risk group comprised frail adults living in areas of high disadvantage (HR 3.23, 95% CI 2.99-3.49; P < 0.001). We observed additive effects between frailty and living in areas of mid- (RERI 0.29; 95% CI 0.13-0.45; P < 0.001) and high (RERI 0.62, 95% CI 0.41-0.83; P < 0.001) neighborhood disadvantage.
Conclusions:
Considering both frailty and neighborhood disadvantage may assist healthcare organizations in effectively risk-stratifying vulnerable older adults and informing population management strategies. These constructs can be readily assessed at-scale using routinely collected structured EHR data.
More Related Videos
 05:53
Measuring Frailty in HIV-infected Individuals. Identification of Frail Patients is the First Step to Amelioration and Reversal of Frailty
Published on: July 24, 2013
 06:52
Assessment of Dependence in Activities of Daily Living Among Older Patients in an Acute Care Unit
Published on: September 30, 2020
Related Concept Videos
 01:18
Factors Affecting Illness
For instance, risk factors are connected to illness,...
 01:26
Heart Failure III: Clinical Manifestations
 01:30
Heart Failure VII: Nursing Interventions
 01:29
Documentation in Long-Term and Home Healthcare Setting
Long-Term Care Facilities
 01:30
Heart Failure V: Medical Management
 01:30
Specialized Care Centers and Settings-II
Rural health centers are specialized care facilities in remote locations with very few medical personnel. The primary care providers who run the centers are mostly Registered Nurse Practitioners. Here, emergency treatment is provided to critically ill or injured patients before they are transferred to the closest hospital. Fortunately, due to advancement in technology, many rural healthcare facilities and professionals have easy access to diagnostic and treatment...