Related Experiment Video
Updated: Jul 11, 2025
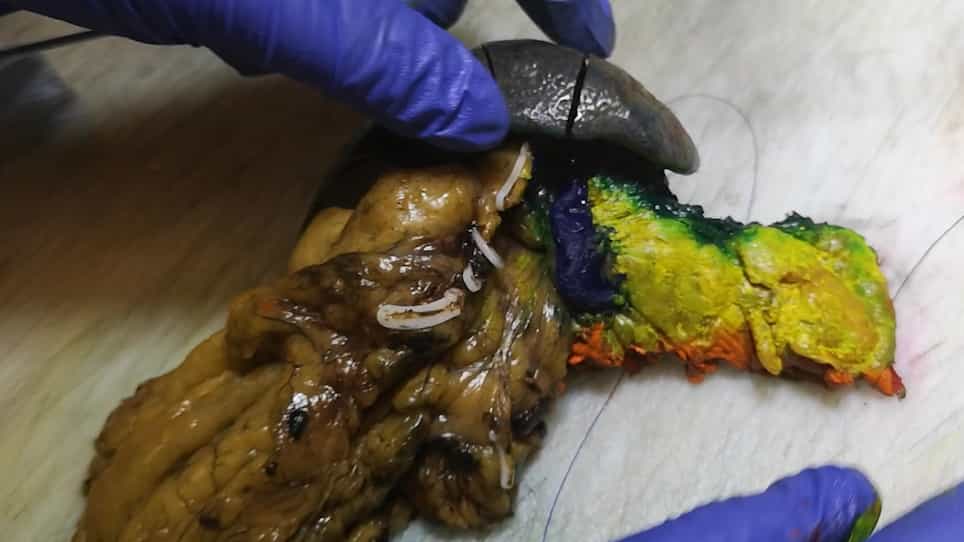
DIPLOMA Approach for Standardized Pathology Assessment of Distal Pancreatectomy Specimens
Published on: February 1, 2020
Management and outcomes of hemorrhage after distal pancreatectomy: a multicenter study at high volume centers
Côme Duclos1, Thibault Durin2, Ugo Marchese3
1Department of Digestive Surgical Oncology, Liver Transplantation Unit. CHU Besançon, Besançon, France.

Insights
Clinically relevant post-pancreatectomy hemorrhage (CR-PPH) after distal pancreatectomy (DP) is uncommon but significantly increases 90-day mortality and failure-to-rescue rates. Understanding risk factors is crucial for managing this rare complication.
Area of Science:
- Surgical Oncology
- Gastroenterology
- Hepatobiliary Surgery
Background:
- Limited data exist on clinically relevant post-pancreatectomy hemorrhage (CR-PPH) following distal pancreatectomy (DP).
- Existing studies primarily focus on pancreatoduodenectomy, leaving a gap in understanding DP-specific hemorrhage risks.
Purpose of the Study:
- To evaluate the incidence, risk factors, management, and outcomes of CR-PPH after distal pancreatectomy (DP).
- To compare the severity and outcomes of CR-PPH with other post-pancreatectomy complications.
Main Methods:
- Retrospective analysis of non-extended DP procedures performed between 2014 and 2018.
- Inclusion criteria encompassed Grade B and C post-pancreatectomy hemorrhage (PPH).
- Multivariable analysis was used to identify independent risk factors for CR-PPH.
Main Results:
- 5.5% of patients developed CR-PPH, requiring reintervention in 87.7% of cases.
- CR-PPH was significantly associated with increased 90-day mortality, morbidity, and hospital stay.
- Prolonged operative time and concurrent pancreatico-enteric fistula (POPF) were independent risk factors for CR-PPH.
Conclusions:
- CR-PPH after DP is a rare but severe complication.
- It is linked to significantly higher 90-day mortality and failure-to-rescue rates compared to POPF.
- Identifying and managing risk factors for CR-PPH is critical for improving patient outcomes.
Background:
Data on clinically relevant post-pancreatectomy hemorrhage (CR-PPH) are derived from series mostly focused on pancreatoduodenectomy, and data after distal pancreatectomy (DP) are scarce.
Methods:
All non-extended DP performed from 2014 to 2018 were included. CR-PPH encompassed grade B and C PPH. Risk factors, management, and outcomes of CR-PPH were evaluated.
Results:
Overall, 1188 patients were included, of which 561 (47.2 %) were operated on minimally invasively. Spleen-preserving DP was performed in 574 patients (48.4 %). Ninety-day mortality, severe morbidity and CR-POPF rates were 1.1 % (n = 13), 17.4 % (n = 196) and 15.5 % (n = 115), respectively. After a median interval of 8 days (range, 0-37), 65 patients (5.5 %) developed CR-PPH, including 28 grade B and 37 grade C. Reintervention was required in 57 patients (87.7 %). CR-PPH was associated with a significant increase of 90-day mortality, morbidity and hospital stay (p < 0.001). Upon multivariable analysis, prolonged operative time and co-existing POPF were independently associated with CR-PPH (p < 0.005) while a chronic use of antithrombotic agent trended towards an increase of CR-PPH (p = 0.081). As compared to CR-POPF, the failure-to-rescue rate in patients who developed CR-PPH was significantly higher (13.8 % vs. 1.3 %, p < 0.001).
Conclusion:
CR-PPH after DP remains rare but significantly associated with an increased risk of 90-day mortality and failure-to-rescue.

Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management