Related Experiment Video
Updated: Jul 11, 2025

Magnetic Resonance Imaging of Multiple Sclerosis at 7.0 Tesla
Published on: February 19, 2021
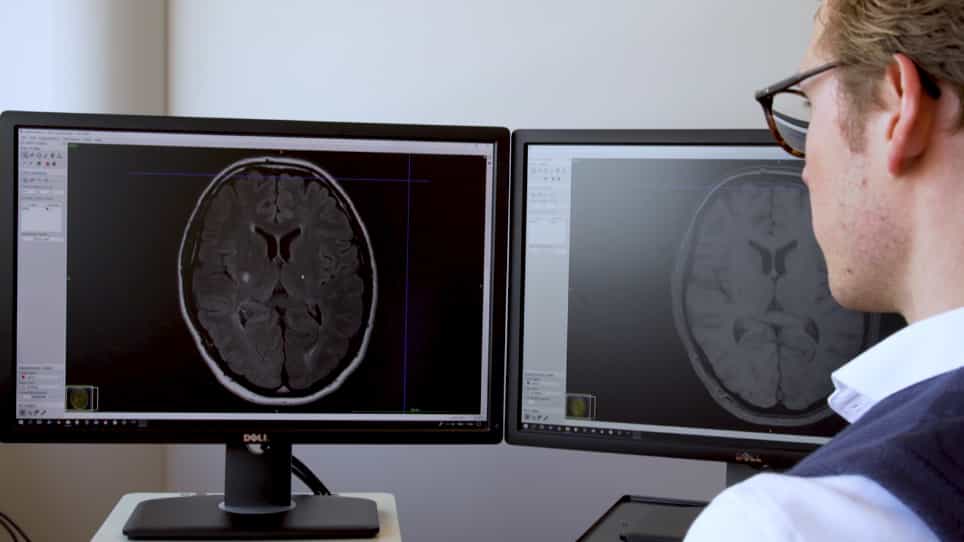
Assessment of white matter hyperintensity severity using multimodal magnetic resonance imaging
Olivier Parent1,2, Aurélie Bussy1,2, Gabriel Allan Devenyi1,3
1Cerebral Imaging Centre, Douglas Mental Health University Institute, Montreal, Quebec H4H 1R3, Canada.

Abstract:
White matter hyperintensities are radiological abnormalities reflecting cerebrovascular dysfunction detectable using MRI. White matter hyperintensities are often present in individuals at the later stages of the lifespan and in prodromal stages in the Alzheimer's disease spectrum. Tissue alterations underlying white matter hyperintensities may include demyelination, inflammation and oedema, but these are highly variable by neuroanatomical location and between individuals. There is a crucial need to characterize these white matter hyperintensity tissue alterations in vivo to improve prognosis and, potentially, treatment outcomes. How different MRI measure(s) of tissue microstructure capture clinically-relevant white matter hyperintensity tissue damage is currently unknown. Here, we compared six MRI signal measures sampled within white matter hyperintensities and their associations with multiple clinically-relevant outcomes, consisting of global and cortical brain morphometry, cognitive function, diagnostic and demographic differences and cardiovascular risk factors. We used cross-sectional data from 118 participants: healthy controls (n = 30), individuals at high risk for Alzheimer's disease due to familial history (n = 47), mild cognitive impairment (n = 32) and clinical Alzheimer's disease dementia (n = 9). We sampled the median signal within white matter hyperintensities on weighted MRI images [T1-weighted (T1w), T2-weighted (T2w), T1w/T2w ratio, fluid-attenuated inversion recovery (FLAIR)] as well as the relaxation times from quantitative T1 (qT1) and T2* (qT2*) images. qT2* and fluid-attenuated inversion recovery signals within white matter hyperintensities displayed different age- and disease-related trends compared to normal-appearing white matter signals, suggesting sensitivity to white matter hyperintensity-specific tissue deterioration. Further, white matter hyperintensity qT2*, particularly in periventricular and occipital white matter regions, was consistently associated with all types of clinically-relevant outcomes in both univariate and multivariate analyses and across two parcellation schemes. qT1 and fluid-attenuated inversion recovery measures showed consistent clinical relationships in multivariate but not univariate analyses, while T1w, T2w and T1w/T2w ratio measures were not consistently associated with clinical variables. We observed that the qT2* signal was sensitive to clinically-relevant microstructural tissue alterations specific to white matter hyperintensities. Our results suggest that combining volumetric and signal measures of white matter hyperintensity should be considered to fully characterize the severity of white matter hyperintensities in vivo. These findings may have implications in determining the reversibility of white matter hyperintensities and the potential efficacy of cardio- and cerebrovascular treatments.
Insights
Quantitative T2* (qT2*) MRI signal measures in white matter hyperintensities are sensitive to tissue damage and associated with clinical outcomes. Combining qT2* with volumetric measures may improve white matter hyperintensity severity characterization.
Area of Science:
- Neuroimaging
- Cerebrovascular Biology
- Alzheimer's Disease Research
Background:
- White matter hyperintensities (WMH) are MRI-detectable abnormalities linked to cerebrovascular dysfunction, common in aging and Alzheimer's disease (AD).
- WMH tissue alterations (demyelination, inflammation, edema) vary by location and individual, necessitating in vivo characterization for improved prognosis and treatment.
- Current understanding of how MRI measures of tissue microstructure relate to WMH damage and clinical outcomes is limited.
Purpose of the Study:
- To compare six MRI signal measures within WMH for their association with clinically relevant outcomes.
- To determine which MRI measures best capture WMH tissue damage and its clinical impact.
- To inform strategies for characterizing WMH severity and potential treatment efficacy.
Main Methods:
- Cross-sectional analysis of 118 participants (healthy controls, familial AD risk, mild cognitive impairment, AD dementia).
- Acquisition of T1w, T2w, FLAIR, quantitative T1 (qT1), and quantitative T2* (qT2*) MRI data.
- Sampling median MRI signal within WMH and correlating with brain morphometry, cognition, demographics, and cardiovascular risk factors.
Main Results:
- qT2* and FLAIR signals in WMH showed age- and disease-related trends distinct from normal-appearing white matter.
- WMH qT2* signal, particularly in periventricular and occipital regions, consistently associated with all clinical outcomes across analyses.
- qT1 and FLAIR showed multivariate clinical associations; T1w, T2w, and T1w/T2w ratios did not consistently correlate with clinical variables.
Conclusions:
- The qT2* MRI signal is sensitive to clinically relevant microstructural tissue alterations specific to WMH.
- Combining volumetric and signal measures (especially qT2*) is recommended for comprehensive WMH severity assessment.
- Findings may guide reversibility assessments and efficacy of cardio- and cerebrovascular treatments for WMH.