Related Experiment Video
Updated: Jul 11, 2025
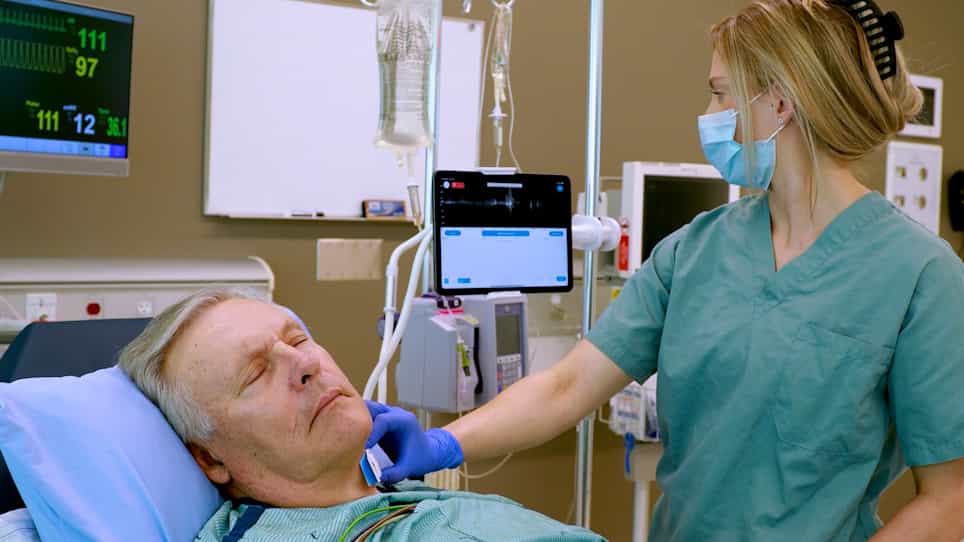
Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
The Influence of Food Intake and Preload Augmentation on Cardiac Functional Parameters: A Study Using Both Cardiac
Lasse Visby1, Rasmus Møgelvang1,2,3, Frederik Fasth Grund1
1Department of Cardiology, The Heart Center Rigshospitalet, Blegdamsvej 9, DK-2100 Copenhagen, Denmark.

Insights
Food intake and fluid loading significantly impact cardiac output and ventricular volumes. Standardizing oral intake before cardiac imaging like TTE and CMR is recommended for accurate hemodynamic assessment.
Area of Science:
- Cardiology
- Medical Imaging
- Physiology
Background:
- Cardiac output (CO) and ventricular volumes are crucial hemodynamic parameters.
- The influence of food intake and preload augmentation on these parameters requires further investigation.
Purpose of the Study:
- To investigate the effects of food intake and preload augmentation on cardiac output (CO), and left ventricle (LV) and right ventricle (RV) volumes.
- To compare assessment methods including cardiac magnetic resonance (CMR) and trans-thoracic echocardiography (TTE).
Main Methods:
- Eighty-two subjects (40 with cardiac disease, 42 without) underwent CMR and TTE before and after saline infusion.
- Subjects were divided into 'food/fluid' (meal during infusion) and 'fasting/fluid' groups.
- Analysis included end-diastolic (EDV) and end-systolic (ESV) volumes, feature tracking (FT), LV global longitudinal strain (GLS), and RV longitudinal strain (LS).
Main Results:
- Cardiac output (CO) increased significantly in both groups, with a greater increase in the food/fluid group.
- Left ventricle (LV) stroke volume (SV) increased via enhanced contractility, increased LV end-diastolic volume (EDV), decreased LV end-systolic volume (ESV), and improved LV feature tracking (FT) and global longitudinal strain (GLS).
- Right ventricle (RV) SV increased through volume expansion, with increased RV EDV and RV ESV, and stable RV FT and RV longitudinal strain (LS) in the fasting/fluid group.
Conclusions:
- Preload augmentation and food intake significantly alter hemodynamic and cardiac functional parameters.
- Standardized recommendations for oral intake before cardiac assessments (TTE, CMR, right heart catheterization) are warranted.
- The LV and RV utilize distinct mechanisms to augment stroke volume: LV via contractility, RV via volume expansion.
Abstract:
(1) Background: To investigate how food intake and preload augmentation affect the cardiac output (CO) and volumes of the left ventricle (LV) and right ventricle (RV) assessed using cardiac magnetic resonance (CMR) and trans-thoracic echocardiography (TTE). (2) Methods: Eighty-two subjects with (n = 40) and without (n = 42) cardiac disease were assessed using both CMR and TTE immediately before and after a fast infusion of 2 L isotonic saline. Half of the population had a meal during saline infusion (food/fluid), and the other half were kept fasting (fasting/fluid). We analyzed end-diastolic (EDV) and end-systolic (ESV) volumes and feature tracking (FT) using CMR, LV global longitudinal strain (GLS), and RV longitudinal strain (LS) using TTE. (3) Results: CO assessed using CMR increased significantly in both groups, and the increase was significantly higher in the food/fluid group: LV-CO (ΔLV-CO: +2.6 ± 1.3 vs. +0.7 ± 1.0 p < 0.001), followed by increased heart rate (HR) (ΔHR: +12 ± 8 vs. +1 ± 6 p < 0.001). LV and RV achieved increased stroke volume (SV) through different mechanisms. For the LV, through increased contractility, increased LV-EDV, decreased LV-ESV, increased LV-FT, and GLS were observed. For the RV, increased volumes, increased RV-EDV, increased RV-ESV, and at least for the fasting/fluid group, unchanged RV-FT and RV-LS were reported. (4) Conclusions: Preload augmentation and food intake have a significant impact on hemodynamic and cardiac functional parameters. This advocates for standardized recommendations regarding oral intake of fluid and food before cardiac assessment, for example, TTE, CMR, and right heart catheterization. We also demonstrate different approaches for the LV and RV to increase SV: for the LV by increased contractility, and for the RV by volume expansion.
More Related Videos


Related Concept Videos
 01:29
Pathophysiology of Cardiac Performance
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
 01:29
Heart Failure II: Pathophysiology
 01:17
Pathophysiology of Heart Failure
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...