Related Experiment Video
Updated: Jul 10, 2025
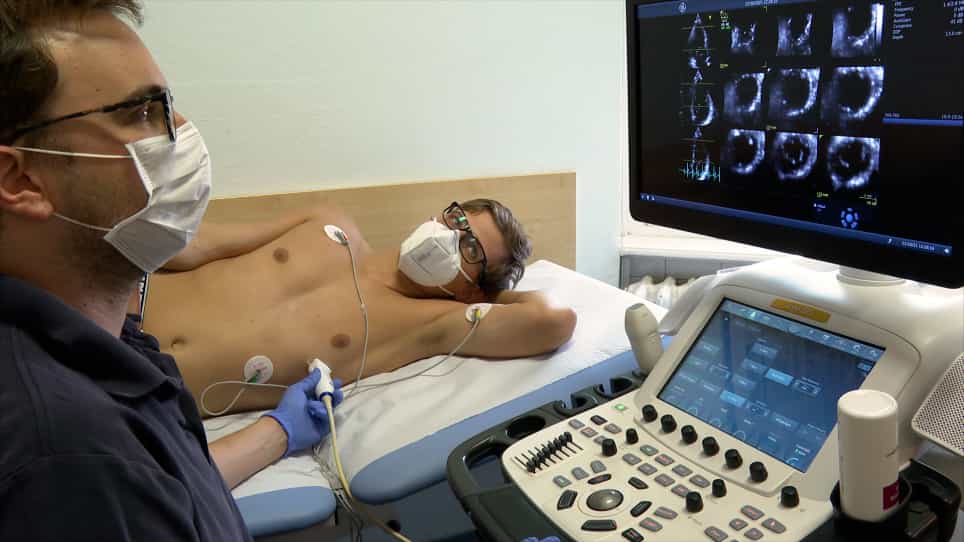
Evaluation of Left Ventricular Structure and Function using 3D Echocardiography
Published on: October 28, 2020
Total 25-Hydroxyvitamin D Is an Independent Marker of Left Ventricular Ejection Fraction in Heart Failure with
Timea Magdolna Szabo1,2, Előd Ernő Nagy3,4, Ádám Kirchmaier2
1Doctoral School of Medicine and Pharmacy, George Emil Palade University of Medicine, Pharmacy, Science and Technology of Târgu Mureș, 540142 Târgu Mureș, Romania.

Insights
Vitamin D deficiency is linked to worse heart failure outcomes. Lower 25-hydroxyvitamin D (25(OH)D) levels correlate with reduced left ventricular ejection fraction (LVEF) in heart failure patients, suggesting a need for targeted supplementation.
Area of Science:
- Cardiology
- Endocrinology
- Biochemistry
Background:
- Vitamin D is a recognized prognostic biomarker in heart failure (HF), but its therapeutic role remains debated.
- Previous studies show mixed results regarding vitamin D supplementation benefits in HF patients, with improvements in cardiac remodeling and quality of life not consistently translating to better physical performance or survival.
- Vitamin D deficiency may serve as a marker for left ventricular (LV) systolic dysfunction in heart failure with reduced and mildly reduced ejection fraction (HFrEF, HFmrEF).
Purpose of the Study:
- To investigate the association between vitamin D levels, serum albumin, and uric acid with LV systolic dysfunction in patients with HFrEF and HFmrEF.
- To explore vitamin D deficiency as a potential marker for LV systolic dysfunction in heart failure.
- To analyze the relationship between 25-hydroxyvitamin D (25(OH)D) and left ventricular ejection fraction (LVEF) in HF patients.
Main Methods:
- Seventy patients with LVEF < 50% underwent comprehensive evaluation including ECG, echocardiography, lung ultrasound (LUS), blood sampling, and the six-minute walk test (6MWT).
- Health-related quality of life (HRQoL) was assessed using the Minnesota Living with Heart Failure Questionnaire (MLHFQ).
- Statistical analyses, including univariate and multiple regression, were performed to determine correlations and independent associations, adjusting for potential confounders.
Main Results:
- Significant positive correlations were observed between LVEF and 25(OH)D, serum uric acid (UA), and albumin.
- Patients with severely reduced LVEF exhibited higher serum UA, NT-proBNP levels, and MLHFQ scores, but lower 25(OH)D concentrations.
- 25(OH)D was independently associated with LVEF, even after adjusting for factors like age, NT-proBNP, chronic coronary syndrome, hypertension, and anemia.
Conclusions:
- 25-hydroxyvitamin D (25(OH)D) is closely associated with left ventricular ejection fraction (LVEF) in heart failure patients.
- The findings support the necessity of establishing appropriate vitamin D supplementation strategies and dietary interventions for individuals with heart failure.
- Observed changes in LVEF, 25(OH)D, serum UA, and albumin levels in HFrEF and HFmrEF suggest a shared pathophysiological background.
Abstract:
Vitamin D emerged as an important prognostic biomarker in heart failure (HF), with currently highly debated therapeutic implications. Several trials on vitamin D supplementation in HF showed improvements in left ventricular (LV) remodeling and function and health-related quality of life (HRQoL), which did not translate into mid- to long-term beneficial effects regarding physical performance and mortality. We addressed total 25-hydroxyvitamin D (25(OH)D), serum albumin, and uric acid (UA) levels, focusing mainly on vitamin D deficiency, as potential markers of LV systolic dysfunction in HF with reduced and mildly reduced ejection fraction (HFrEF, HFmrEF). Seventy patients with LVEF < 50% were comprehensively evaluated using ECG, echocardiography, lung ultrasound (LUS), blood sampling, and the six-minute walk test (6MWT). HRQoL was also assessed using the Minnesota Living with Heart Failure Questionnaire (MLHFQ). Statistically significant positive correlations were found between LVEF, 25(OH)D, serum UA, and albumin, respectively (p = 0.008, p = 0.009, and p = 0.001). Serum UA (7.4 ± 2.4 vs. 5.7 ± 2.1, p = 0.005), NT-proBNP levels (1090.4 (675.2-2664.9) vs. 759.0 (260.3-1474.8), p = 0.034), and MLHFQ scores (21.0 (14.0-47.0) vs. 14.5 (4.5-25.5), p = 0.012) were significantly higher, whereas 25(OH)D concentrations (17.6 (15.1-28.2) vs. 22.7 (19.5-33.8), p = 0.010) were lower in subjects with severely reduced LVEF. Also, 25(OH)D was independently associated with LVEF in univariate and multiple regression analysis, maintaining its significance even after adjusting for confounders such as age, NT-proBNP, the presence of chronic coronary syndrome, hypertension, and anemia. According to our current findings, 25(OH)D is closely associated with LVEF, further supporting the need to establish correct vitamin D supplementation schemes and dietary interventions in HF. The changes in LVEF, 25(OH)D, serum UA, and albumin levels in HFrEF and HFmrEF indicate a similar pathophysiological background.
Related Concept Videos
 01:19
Blood Studies for Cardiovascular System II: CRP, Hcy, and Cardiac Natriuretic Peptide Markers
These markers indicate stress or strain on the heart muscle:
Natriuretic Peptides (BNP)
Cardiac myocytes produce these hormones in response to ventricular stretching...
 01:17
Pathophysiology of Heart Failure
 01:22
Heart Failure Drugs: Diuretics