Related Experiment Video
Updated: Jul 10, 2025
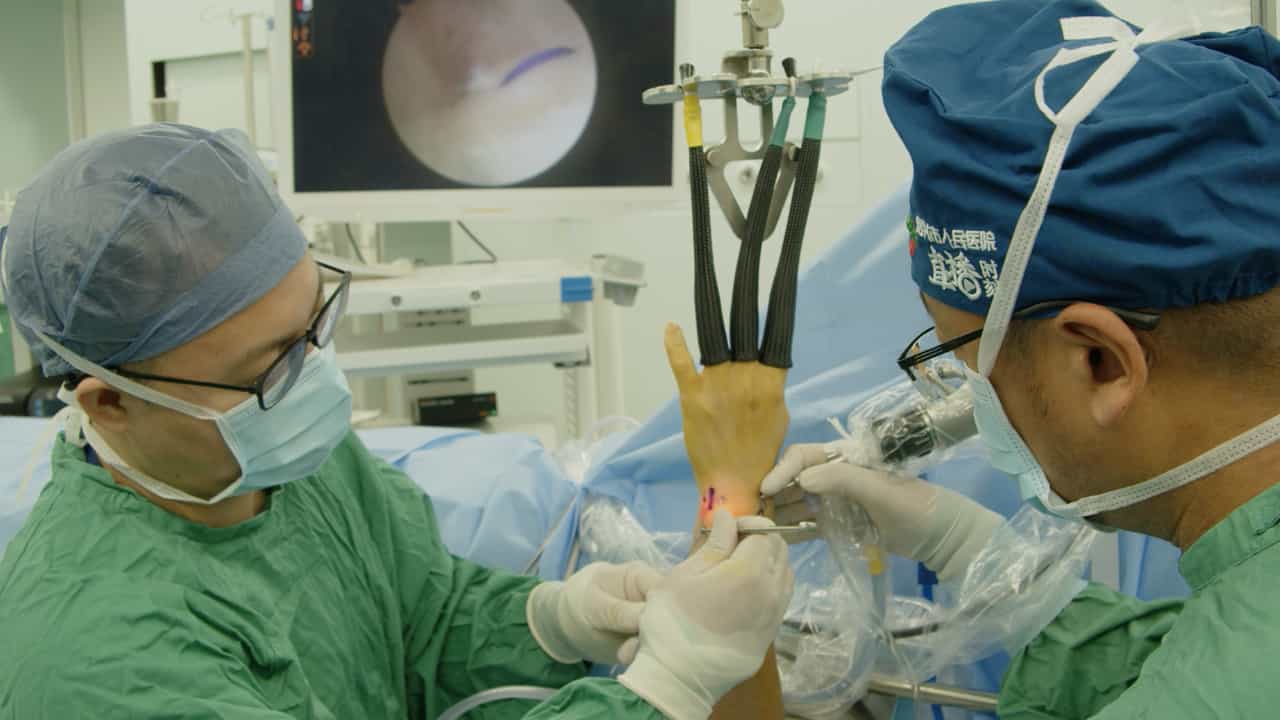

Novel Triple-Loop Technique for Suturing TFCC Injuries without Transosseous Tunnel
Published on: May 23, 2025
Locked Tension Band Wiring: A Modified Technique for Olecranon Fractures-A Multicenter Study Comparing Clinical
Yutaro Kuwahara1, Yasuhiko Takegami2, So Mitsuya3
1Department of Orthopaedic Surgery, Orthopaedic Registrar, Nagoya University Graduate School of Medicine, Nagoya, Japan.

Purpose:
Tension band wiring is the standard treatment for olecranon fractures, but it is associated with high rate of implant-related complication. To reduce this high complication rate, we developed a modified technique, locked tension band wiring (LTBW). The aim of this study was to investigate whether LTBW reduces complication and reoperation rates compared to conventional methods (CTBW).
Methods:
We identified 213 olecranon fractures treated with tension band wiring: 183 were treated with CTBW, and 30 were treated with LTBW, and patients in each group were selected using propensity score matching. We evaluated operation time, intraoperative bleeding, complication and reoperation rates, the amount of Kirschner's wire (K-wire) back-out, and Mayo Elbow Performance Index (MEPI). Complications included nonunion, loss of fracture reduction, implant failure, infection, neurological impairment, heterotopic ossification, and implant irritation. Implant removal included at the patient's request with no symptoms.
Results:
We finally investigated 29 patients in both groups. The mean operation time was significantly longer in the LTBW (106.7 ± 17.5 vs. 79.7 ± 21.1 min; p < 0.01). Complication rates were significantly lower in the LTBW than the CTBW group (10.3 vs. 37.9%; p = 0.03). The rate of implant irritation was more frequent in the CTBW, but there was no significant difference (3.4 vs. 20.7%; p = 0.10). Removal rate was significantly lower in the LTBW (41.4 vs. 72.4%; p = 0.03). The mean amount of K-wire backout at last follow-up was significantly less in the LTBW (3.79 ± 0.65 mm vs. 8.97 ± 3.54 mm; p < 0.01). There were no significant differences in mean MEPI at all follow-up periods (77.4 ± 9.0 vs. 71.5 ± 14.0; p = 0.07, 87.4 ± 7.2 vs. 85.2 ± 10.3; p = 0.40, 94.6 ± 5.8 vs. 90.4 ± 9.0; p = 0.06, respectively).
Conclusion:
Our modified TBW significantly increased operation time compared to conventional method, but reduced the complication and removal rate and had equivalent functional outcomes in this retrospective study.
More Related Videos
 04:42
Treatment with Locking Intramedullary Nailing for Intertrochanteric Fracture of the Femur Utilizing a New Awl with a Distal Positioner
Published on: June 6, 2025
 15:11
Surgical Fixation of Sternal Fractures: Preoperative Planning and a Safe Surgical Technique Using Locked Titanium Plates and Depth Limited Drilling
Published on: January 5, 2015