Related Experiment Video
Updated: Jul 9, 2025


Assessment of Static Graviceptive Perception in the Roll-Plane using the Subjective Visual Vertical Paradigm
Published on: April 28, 2020
Inversion Test and Sitting-Up Oculomotor Patterns in Patients with Graviceptive Heavy Posterior Cupula - A Case
Ajay Kumar Vats1, Sudhir Kothari2, Renu Khamesra3
1Chaudhary Hospital and Medical Research Centre Private Limited, Udaipur, Rajasthan, India.

Abstract:
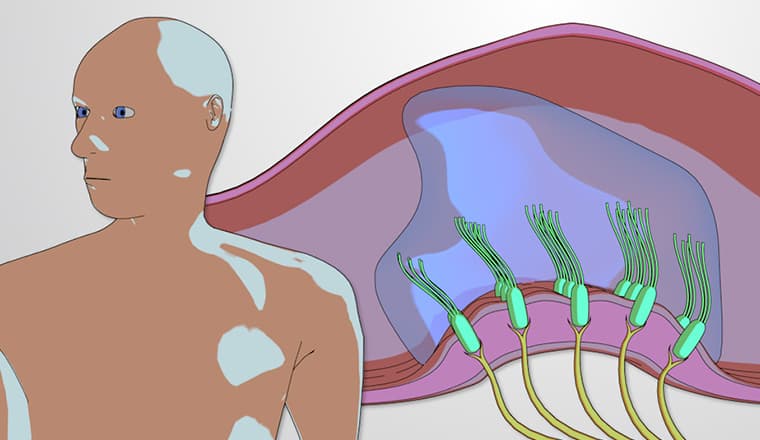
A graviceptive heavy posterior cupula typically results from cupulolithiasis and clinically manifests as short vertigo spells when the head moves in the provocative position. Half-Hallpike test (HHT) in posterior cupulolithiasis (PSC-BPPV-cu) elicits an upbeating ipsitorsional nystagmus (UBITN), which lasts more than a minute as per the consensus criteria developed by the Barany Society. In the last decade, cases with canalolithiasis in the short arm of the posterior semicircular canal (PSC-BPPV-sa), wherein the otoconial debris falls on the utricular side of the posterior cupula on getting up from supine, rendering it heavy (graviceptive), have been reported. Such patients complain of sitting-up vertigo, associated with a constant disequilibrium, and anteroposterior truncal oscillations are recorded by ad hoc posturography in many of these patients. The oculomotor patterns generated in such patients during the HHT may be identical to those resulting from PSC-BPPV-cu. Rarely do the two conditions (PSC-BPPV-cu and PSC-BPPV-sa) coexist. Nine cases of graviceptive heavy cupula were diagnosed at our center over a period of 6 months from September 1, 2022, to March 31, 2023, with their characteristic diagnostic oculomotor patterns, distinguishing features, and management discussed. We propose a grading system for the inversion test during the HHT that reliably distinguishes PSC-BPPV-cu from PSC-BPPV-sa, as well as when the two conditions coexist.