Related Experiment Video
Updated: Jul 9, 2025

Voluntary Breath-hold Technique for Reducing Heart Dose in Left Breast Radiotherapy
Published on: July 3, 2014
Correlation between maximum heart distance and thoracic diameter changes and diaphragmatic descent in left-sided
He-Gou Wu1, Guang-Wei Zhang1, Jian-Feng Liu1
1Department of Radiation Oncology, Shenzhen People's Hospital, The Second Clinical Medical College of Jinan University, Shenzhen, Guangdong, People's Republic of China.

Background:
Cardioprotection is valued in radiotherapy for patients with left-sided breast cancer. Deep inspiration breath-hold (DIBH) technique can achieve cardioprotection well. However, during DIBH, the extent to which the heart enters the radiation field is affected by the movement of the thorax and diaphragm. The aim of this study was to analyze the correlation between the maximum distance of the heart entering the field (maximum heart distance, MHD) and thoracic diameter changes and diaphragmatic descent in left-sided breast cancer patients during DIBH.
Patients And Methods:
Ninety-eight patients with left-sided breast cancer were included in this retrospective study. They performed simulation in Sentinel-guided DIBH, and two sets of CT images were collected under both free breathing (FB) and DIBH, and diaphragm positions, anteroposterior thoracic diameter (ATD), transverse thoracic diameter (TTD), gating window level (GWL), and MHD were measured, and the change (Δ) of each parameter in DIBH relative to that in FB were calculated. Pearson or Spearman test were used to analyze the correlation between ΔMHD and the changes in other parameters.
Results:
For all patients with DIBH, the average of ΔMHD was -8.3 mm, and the average of ΔATD and ΔTTD were 11.0 and 8.6 mm, and the median of both left diaphragmatic descent (LDD) and right diaphragmatic descent (RDD) were 35.0 mm, and the median of GWL was 11.1 mm. The correlation coefficients between MHD decrease (ΔMHD) and LDD, RDD, and ΔTTD were -0.430 (p = 0.000), -0.592 (p = 0.000) and 0.208 (p = 0.040), respectively, but not significantly correlated with ΔATD or GWL.
Conclusions:
The MHD decrease showed a moderate correlation with diaphragmatic descent In Sentinel-guided DIBH for patients with left-sided breast cancer, while there was a weak or no correlation with thoracic diameter changes or GWL. Abdominal breathing can lower diaphragm more and may be more beneficial to the heart stay away from tangential field.


Related Concept Videos
 01:29
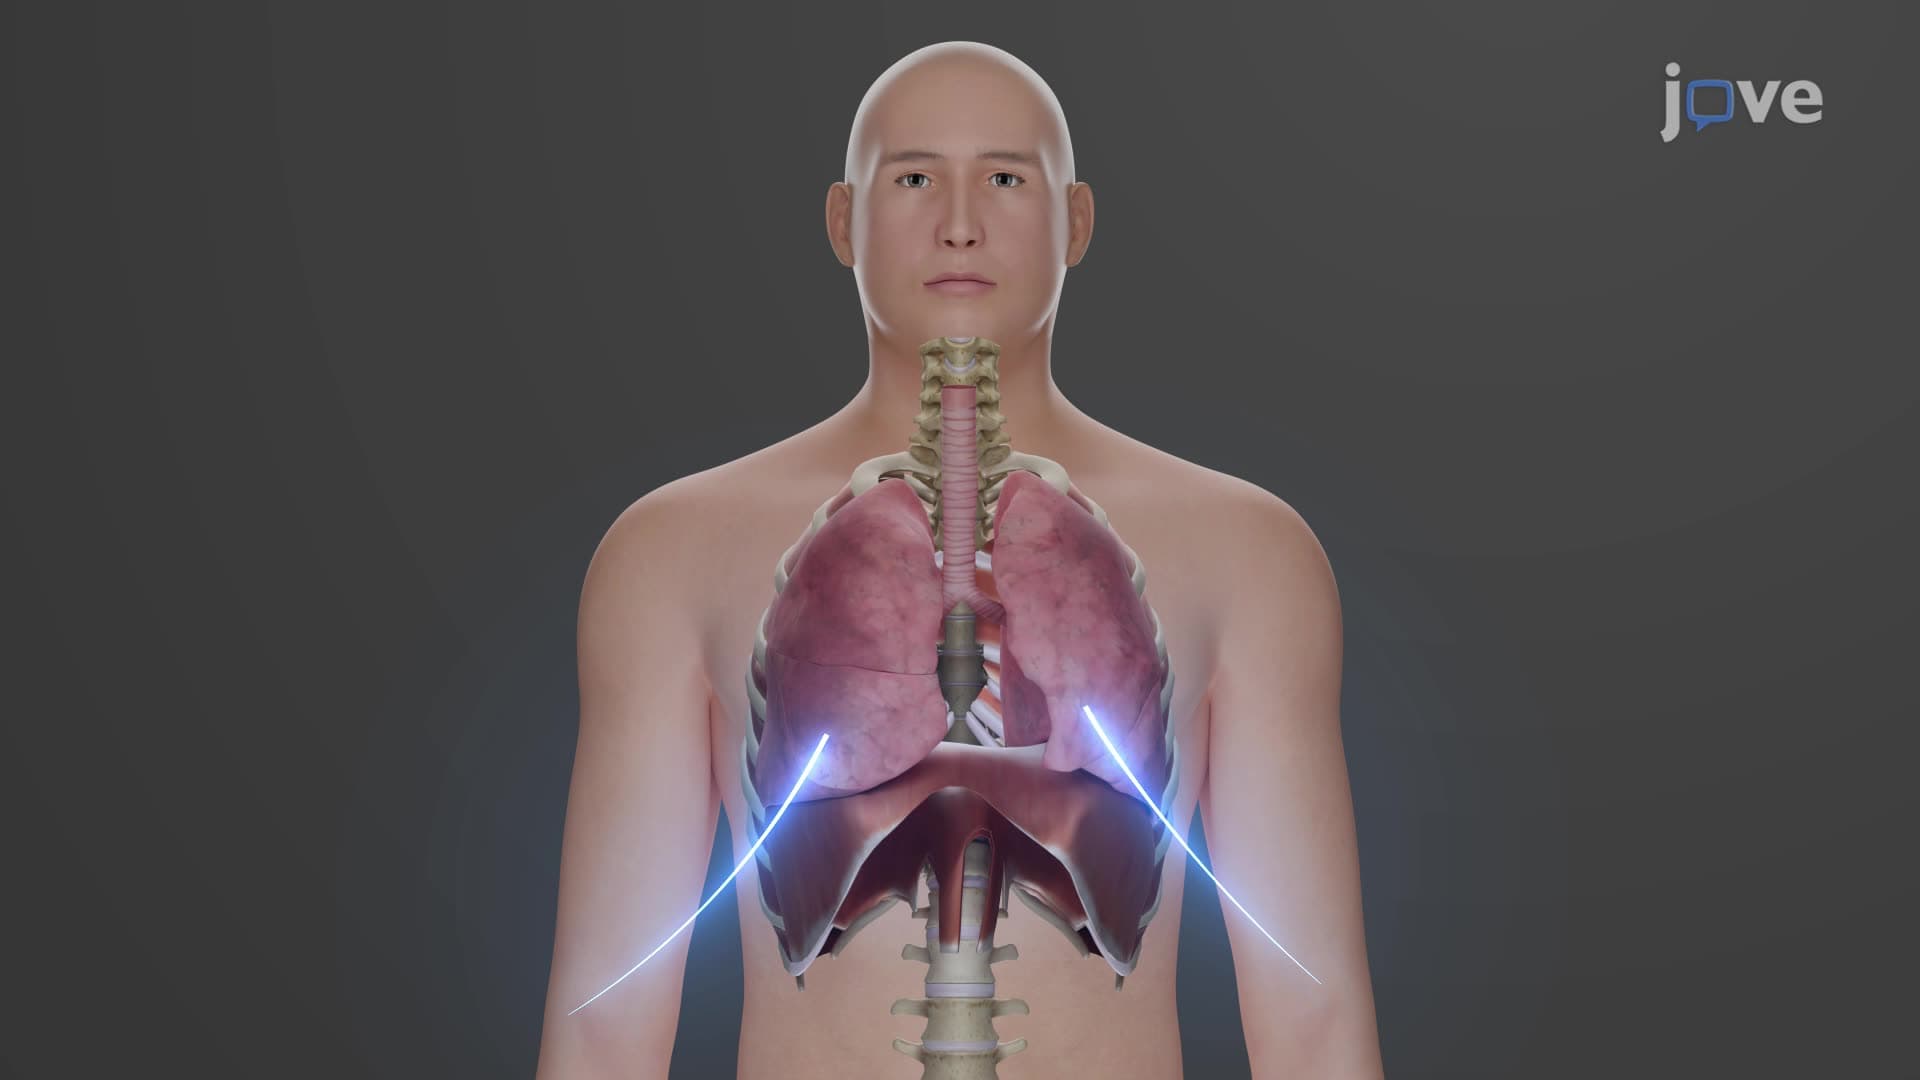
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:24
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:24
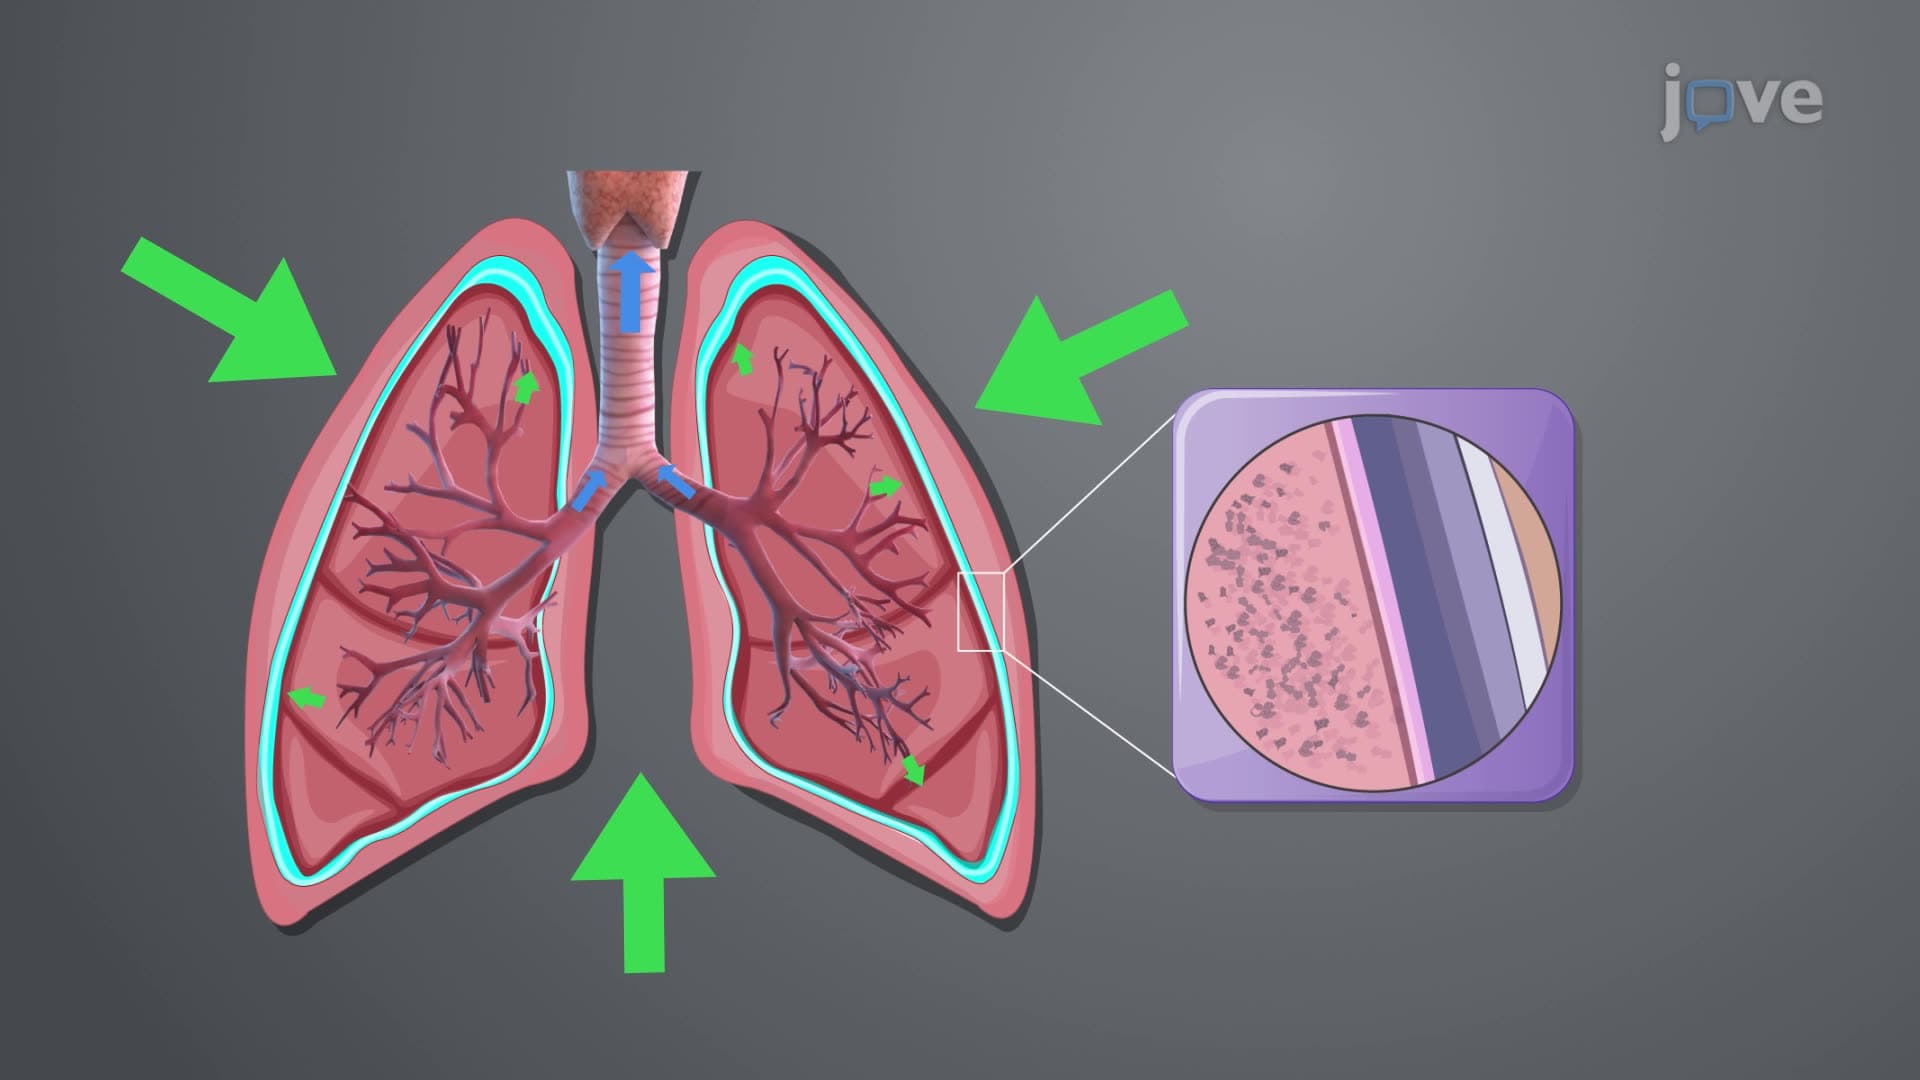
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...
 01:21
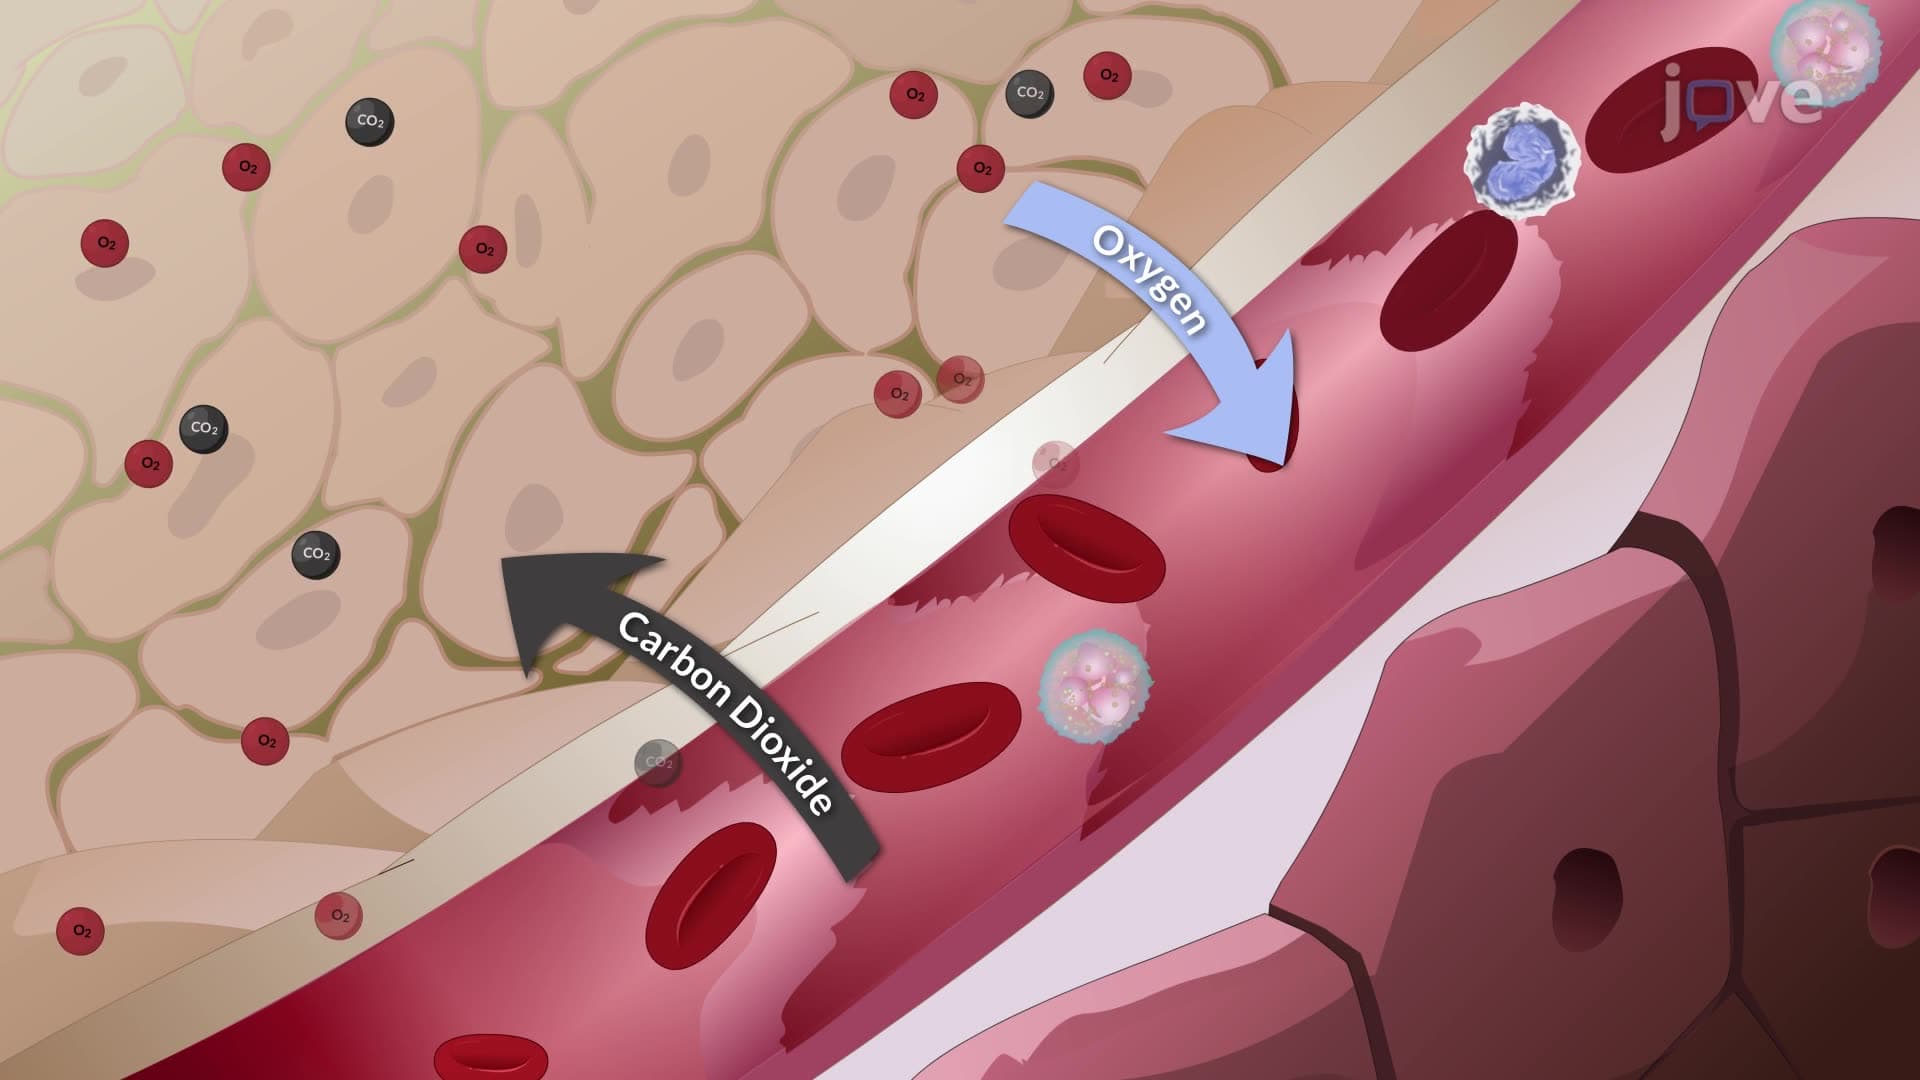
Mechanism of Breathing III: The Accessory Muscles
The respiratory system is a complex network that relies on primary respiratory muscles like the diaphragm, but also involves accessory muscles to enhance lung expansion and airflow during both inhalation and exhalation.
Enhancing Inhalation with Accessory Muscles:
Accessory muscles such as the sternocleidomastoid, scalene, intercostal, and abdominal muscles are crucial when additional respiratory effort is required, such as during deep...