Related Experiment Video
Updated: Jul 9, 2025


Anterior Cervical Discectomy and Fusion in the Ovine Model
Published on: October 5, 2009
C2 versus C3 or C4 as the upper instrumented vertebra for long-segment cervical fusions: a systematic review and
Esteban Quiceno1, Amna Hussein1, Annie Pico1
11Department of Neurosurgery, University of Arizona College of Medicine, Phoenix, Arizona; and.

Objective:
Selecting C2 versus C3 or C4 (i.e., C3/C4) as the rostral anchoring level in long-segment cervical fusions is a common clinical conundrum. The data regarding proximal failure in long constructs of the cervical spine is scarce. The objective of this study was to systematically review the published literature and perform a meta-analysis of the incidence for proximal adjacent-segment disease (ASD) in the context of long cervical fusions and cervicothoracic fusions ending in C2 versus those ending in the subaxial spine (C3 or C4).
Methods:
Using the PRISMA guidelines, the authors performed a search of the PubMed/MEDLINE, Embase/Ovid, and Cochrane Central databases to identify all full-text articles in the English-language literature with the following inclusion criteria: 1) studies including patients with the upper instrumented vertebra (UIV) at C2 versus C3/C4; 2) patients undergoing ≥ 3-level posterior cervical fusion; and 3) indication for surgery of degenerative disc disease, cervical spondylotic myelopathy, or cervical deformity. Studies that were not published in the English language, case reports, review articles, letters to the editor, and meeting abstracts were excluded. A meta-analysis was conducted using a fixed-effects model when I2 values were below 70%. Conversely, when I2 values were equal to or greater than 70%, a random-effects model was used. A funnel plot was used to assess the presence of publication bias.
Results:
Seven studies consisting of 1215 patients were included in the meta-analysis. There were 403 (32.8%) patients in the C2 UIV group and 812 (67.2%) patients in the C3/C4 UIV group. When the 7 studies were analyzed, the overall rate of reoperation was comparable between the C2 (9.2%) and C3/C4 (9.4%) UIV groups (p = 0.93) but the rate of surgical ASD due to proximal pathology was 1.2% and 3%, respectively (OR 0.36, 95% CI 0.15-0.86; p = 0.02). When comparing between groups, no statistical difference was found regarding the rate of reoperation due to distal pathology or surgical infection.
Conclusions:
Long-segment cervical or cervicothoracic constructs that anchor into C2 may have similar complication rates but lower revision rates for proximal ASD than constructs that anchor into the subaxial spine.
Related Concept Videos
 01:28
Articulations of the Vertebral Column
 01:16
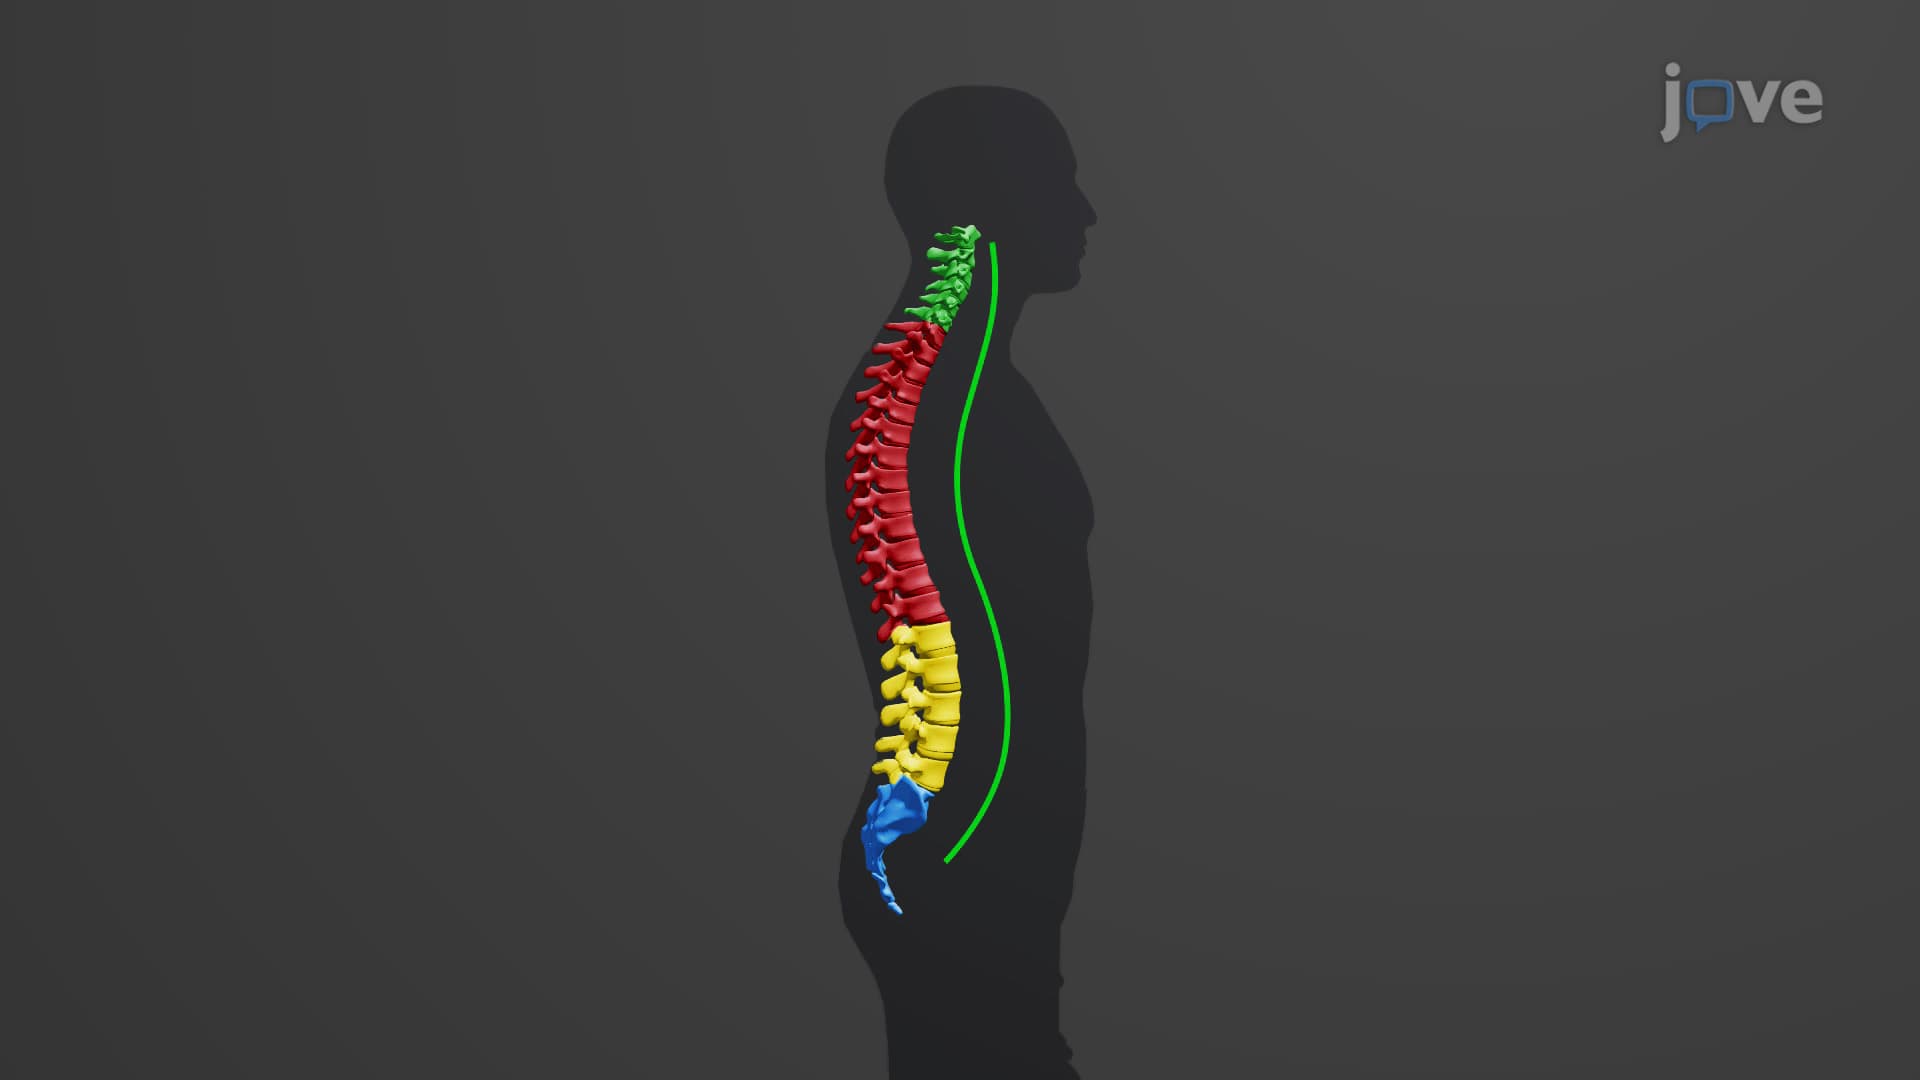
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
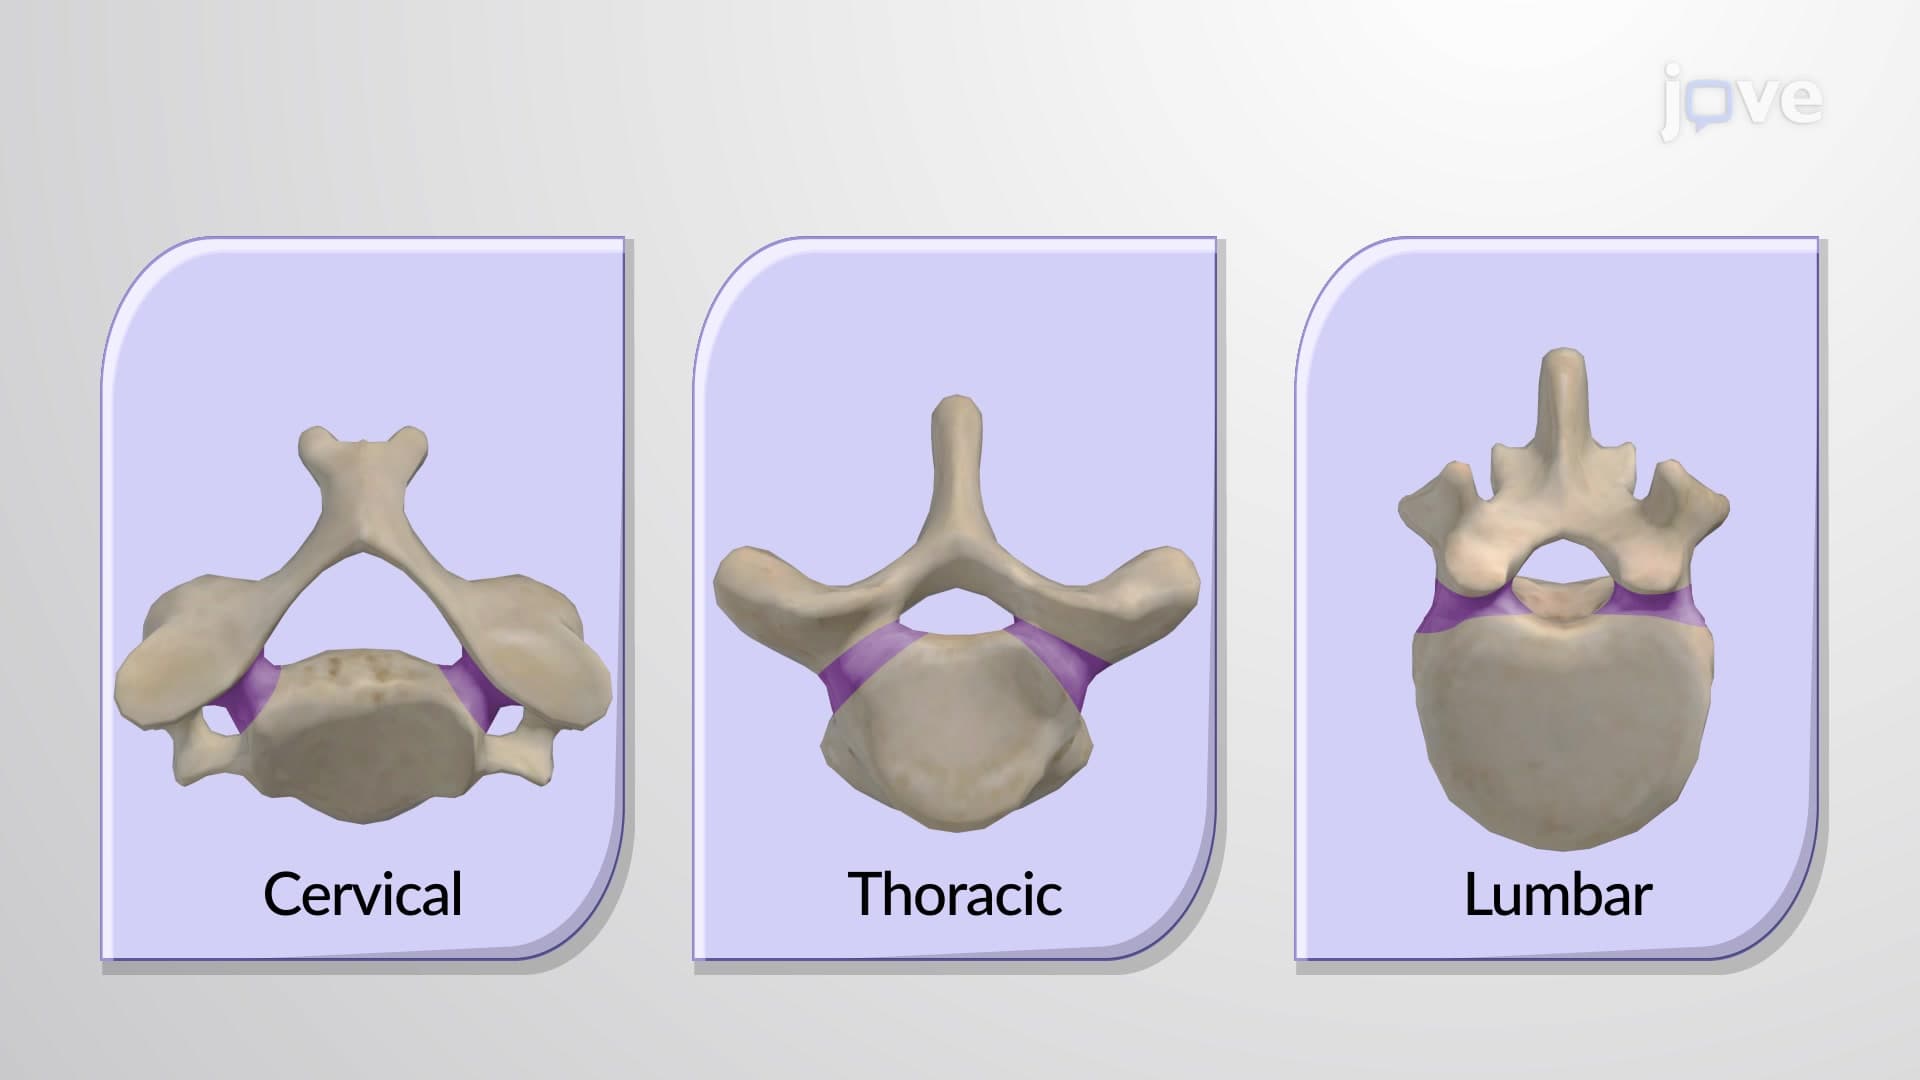
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:30
General Structure of a Vertebra
 01:17
Structural Joints: Cartilaginous Joints
There are two types of cartilaginous joints:
Synchondrosis
A synchondrosis ("joined by cartilage") is a cartilaginous joint where bones are connected by hyaline cartilage. Synchondrosis may be temporary...
 01:15
Spinal Cord: Gross Anatomy
 01:19
Muscles that Move the Head
The bilateral sternocleidomastoid, or SCM, and the suprahyoid and infrahyoid muscles are significant head flexors. The SCM muscles originate at the sternum and clavicle and attach to the mastoid process of the temporal bone. The SCM contracts bilaterally to bend the head forward, whereas...