Related Experiment Video
Updated: Aug 7, 2026
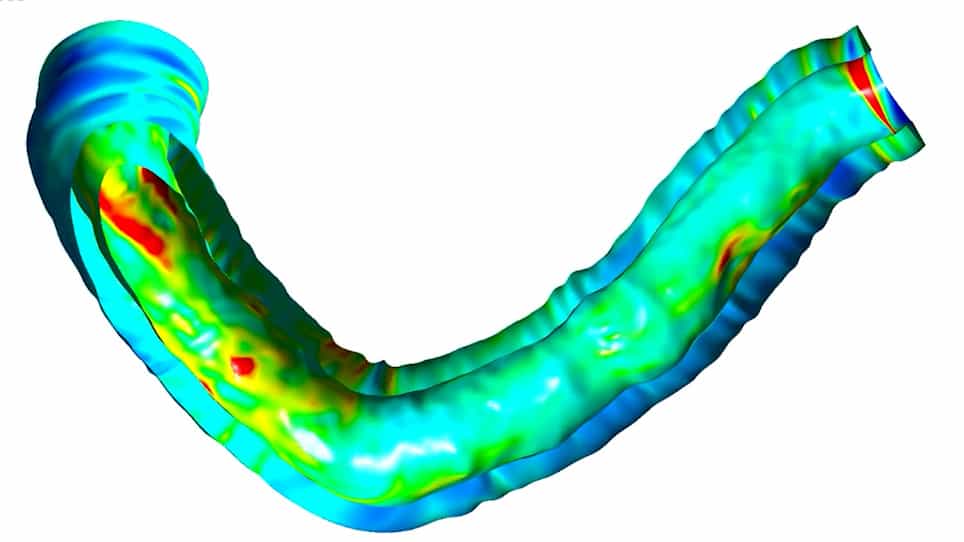

Optical Coherence Tomography Based Biomechanical Fluid-Structure Interaction Analysis of Coronary Atherosclerosis Progression
Published on: January 15, 2022
External validation of novel clinical likelihood models to predict obstructive coronary artery disease and prognosis
Laust Dupont Rasmussen1,2, Michelle Claire Williams3, David E Newby3
1Department of Cardiology, Gødstrup Hospital, Herning, Denmark lausra@rm.dk.

Insights
New clinical likelihood models, risk factor-weighted (RF-CL) and coronary artery calcium score-weighted (CACS-CL), better identify patients with very low risk of obstructive coronary artery disease (CAD). These models offer improved categorization with favorable long-term prognosis.
Area of Science:
- Cardiology
- Medical Imaging
- Risk Stratification
Background:
- Obstructive coronary artery disease (CAD) diagnosis relies on accurate risk stratification.
- Existing models like the European Society of Cardiology pretest probability (ESC-PTP) require external validation for novel approaches.
- Risk factor-weighted clinical likelihood (RF-CL) and coronary artery calcium score-weighted clinical likelihood (CACS-CL) models aim to improve CAD risk assessment.
Purpose of the Study:
- To externally validate the RF-CL and CACS-CL models for identifying obstructive CAD and guiding revascularisation decisions.
- To compare the performance of RF-CL and CACS-CL against the ESC-PTP model.
- To investigate the long-term prognosis of patients categorized into very-low clinical likelihood groups.
Main Methods:
- A cohort of 1585 stable chest pain patients undergoing coronary CT angiography (CTA) was analyzed.
- Obstructive CAD was defined as >70% diameter stenosis on CTA.
- Clinical likelihood scores (ESC-PTP, RF-CL, CACS-CL) were calculated, and revascularisation decisions were recorded. Patient outcomes were followed for 5 years.
Main Results:
- Both RF-CL and CACS-CL models classified significantly more patients into the very-low clinical likelihood (<5%) group compared to ESC-PTP (52.2% and 41.4% vs. 19.2%, p<0.001).
- In the very-low likelihood group, prevalences of obstructive CAD (≤6%) and revascularisation (<1%) were low.
- This low-risk group demonstrated a favorable prognosis with a low rate of non-fatal myocardial infarction or cardiovascular death over 5 years.
Conclusions:
- The RF-CL and CACS-CL models provide improved categorization of patients with suspected obstructive CAD into a very-low risk group.
- These novel models demonstrate preserved accuracy in identifying obstructive CAD and revascularisation needs within the low-risk stratum.
- The validated models indicate a favorable long-term prognosis for patients classified as very-low risk, supporting their clinical utility.
Objectives:
The risk factor-weighted and coronary artery calcium score-weighted clinical likelihood (RF-CL and CACS-CL, respectively) models improve discrimination of patients with suspected obstructive coronary artery disease (CAD). However, external validation is warranted.Compared to the 2019 European Society of Cardiology pretest probability (ESC-PTP) model, the aims were (1) to validate the RF-CL and CACS-CL models for identification of obstructive CAD and revascularisation, and (2) to investigate prognosis by CL thresholds.
Methods:
Stable de novo chest pain patients (n=1585) undergoing coronary CT angiography (CTA) were investigated. Obstructive CAD was defined as >70% diameter stenosis in a major epicardial vessel on CTA. Decision of revascularisation within 120 days was based on onsite judgement. The endpoint was non-fatal myocardial infarction or cardiovascular death. The ESC-PTP was calculated based on age, sex and symptom typicality, the RF-CL additionally included number of risk factors, and the CACS-CL incorporated CACS to the RF-CL.
Results:
Obstructive CAD was present in 386/1585 (24.4%) patients, and 91/1585 (5.7%) patients underwent revascularisation. Both the RF-CL and CACS-CL classified more patients to very-low CL (<5%) of obstructive CAD compared with the ESC-PTP model (41.4% and 52.2% vs 19.2%, p<0.001). In very-low CL patients, obstructive CAD and revascularisation prevalences (≤6% and <1%) remained similar combined with low event risk during 5.0 years follow-up.
Conclusion:
In an external validation cohort, the novel RF-CL and CACS-CL models improve categorisation to a very-low CL group with preserved prevalences of obstructive CAD, revascularisation and favourable prognosis.


Related Concept Videos
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:30
Coronary Artery Disease I: Introduction
 01:30
Coronary Artery Disease III: Clinical Manifestations
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation