Related Experiment Video
Updated: Jul 9, 2025


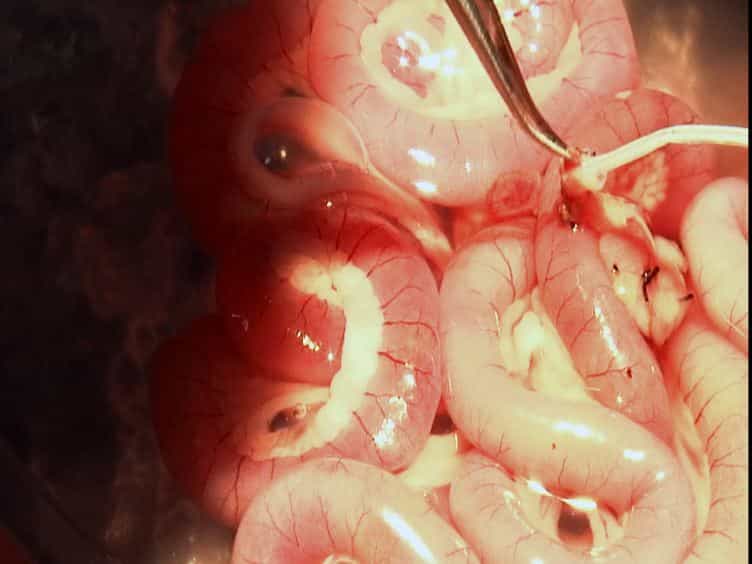
Tissue Engineering of the Intestine in a Murine Model
Published on: December 1, 2012
Parenteral support and micronutrient deficiencies in children with short bowel syndrome: A comprehensive
V Chatzidaki1, R Wood1, A Alegakis2
1Department of Pediatric Gastroenterology, Royal Manchester Children's Hospital, NHS Foundation Trust, UK.

Background & Aims:
Short bowel syndrome (SBS) is the leading cause of chronic intestinal failure. The duration of parenteral support (PS) and the long-term micronutrient needs in children with SBS vary, based on their clinical and anatomical characteristics. Our study aimed to review the clinical course and identify high risk patient groups for prolonged PS and long-term micronutrient supplementation.
Methods:
A retrospective review was conducted on electronic medical records of children with SBS and chronic intestinal failure who were enrolled in the multidisciplinary intestinal rehabilitation program at Manchester Children's Hospital, UK. Children were included in the review if they required PN for more than 60 days out of 74 consecutive days and had at least 3 years of follow-up. Statistical analysis was performed using IBM SPSS Statistics 24.0.
Results:
40 children with SBS achieved enteral autonomy (EA) and 14 remained dependent on PS after 36 months of follow up. Necrotizing enterocolitis was the most common cause for intestinal resection (38.9%) followed by gastroschisis (22.2%), malrotation with volvulus (20.4%), segmental volvulus (9.3%) and long segment Hirschsprung disease (1.9%). Those who achieved EA had significantly longer intestinal length 27.5% (15.0-39.3) than those who remained on PS 6.0% (1.5-12.5) (p < 0.001). Type I SBS was only found in the PS cohort. Median PN dependence was 10.82 months [IQR 5.73-20.78]. Congenital diagnosis was associated with longer PN dependence (21.0 ± 20.0) than acquired (8.7 ± 7.8 months), (p = 0.02). The need for micronutrient supplementation was assessed after the transition to EA; 87.5% children had at least one micronutrient depletion, most commonly Vitamin D (64.1%), followed by iron (48.7%), Vitamin B12 (34.2%), and vitamin E (28.6%). Iron deficiency and vitamin A depletion were correlated with longer PS after multivariate analysis (OR: 1.103, 1.006-1.210, p = 0.037 and OR: 1.048, 0.998-1.102, p = 0.062 respectively).
Conclusion:
In our cohort, small bowel length was the main predictor for EA. Children on longer PS, had more often a congenital cause of resection and were at risk for micronutrient deficiencies in EA.

Related Concept Videos
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the...
 01:27
Parentral Nutrition: Centeral and Peripheral Parental Nutrition
PN can be administered through two primary routes:
1. Central Parenteral Nutrition (CPN):
CPN involves delivering a high concentration of nutrients through a large vein. This is typically achieved using a Peripherally Inserted Central Catheter (PICC) or,...
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...
 01:29
Inflammatory Bowel Disease IV: Pharmacological Management
Pharmacologic...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment: