Related Experiment Video
Updated: Jun 16, 2026


Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
Electrical Impedance Tomography during Abdominal Laparoscopic Surgery: A Physiological Pilot Study
Michela Rauseo1, Savino Spadaro2, Lucia Mirabella1
1Department of Surgical and Medical Science, Anesthesia and Intensive Care Unit, Policlinico Riuniti di Foggia, University of Foggia, Viale Pinto 1, 71122 Foggia, Italy.

Background:
Both general anesthesia and pneumoperitoneum insufflation during abdominal laparoscopic surgery can lead to atelectasis and impairment in oxygenation. Setting an appropriate level of external PEEP could reduce the occurrence of atelectasis and induce an improvement in gas exchange. However, in clinical practice, it is common to use a fixed PEEP level (i.e., 5 cmH2O), irrespective of the dynamic respiratory mechanics. We hypothesized setting a PEEP level guided by EIT in order to obtain an improvement in oxygenation and respiratory system compliance in lung-healthy patients than can benefit a personalized approach.
Methods:
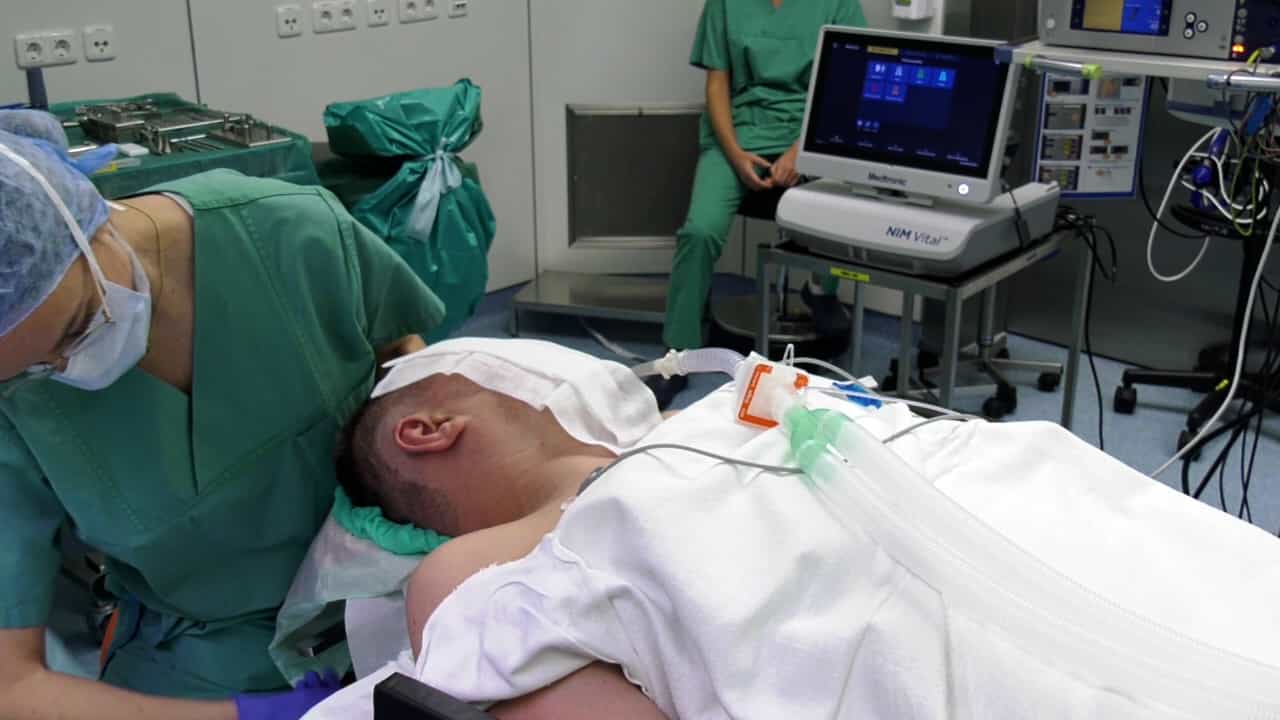
Twelve consecutive patients scheduled for abdominal laparoscopic surgery were enrolled in this prospective study. The EIT Timpel Enlight 1800 was applied to each patient and a dedicated pneumotachograph and a spirometer flow sensor, integrated with EIT, constantly recorded respiratory mechanics. Gas exchange, respiratory mechanics and hemodynamics were recorded at five time points: T0, baseline; T1, after induction; T2, after pneumoperitoneum insufflation; T3, after a recruitment maneuver; and T4, at the end of surgery after desufflation.
Results:
A titrated mean PEEP of 8 cmH2O applied after a recruitment maneuver was successfully associated with the "best" compliance (58.4 ± 5.43 mL/cmH2O), with a low percentage of collapse (10%), an acceptable level of hyperdistention (0.02%). Pneumoperitoneum insufflation worsened respiratory system compliance, plateau pressure, and driving pressure, which significantly improved after the application of the recruitment maneuver and appropriate PEEP. PaO2 increased from 78.1 ± 9.49 mmHg at T0 to 188 ± 66.7 mmHg at T4 (p < 0.01). Other respiratory parameters remained stable after abdominal desufflation. Hemodynamic parameters remained unchanged throughout the study.
Conclusions:
EIT, used as a non-invasive intra-operative monitor, enables the rapid assessment of lung volume and regional ventilation changes in patients undergoing laparoscopic surgery and helps to identify the "optimal" PEEP level in the operating theatre, improving ventilation strategies.