Related Experiment Video
Updated: Jul 8, 2025
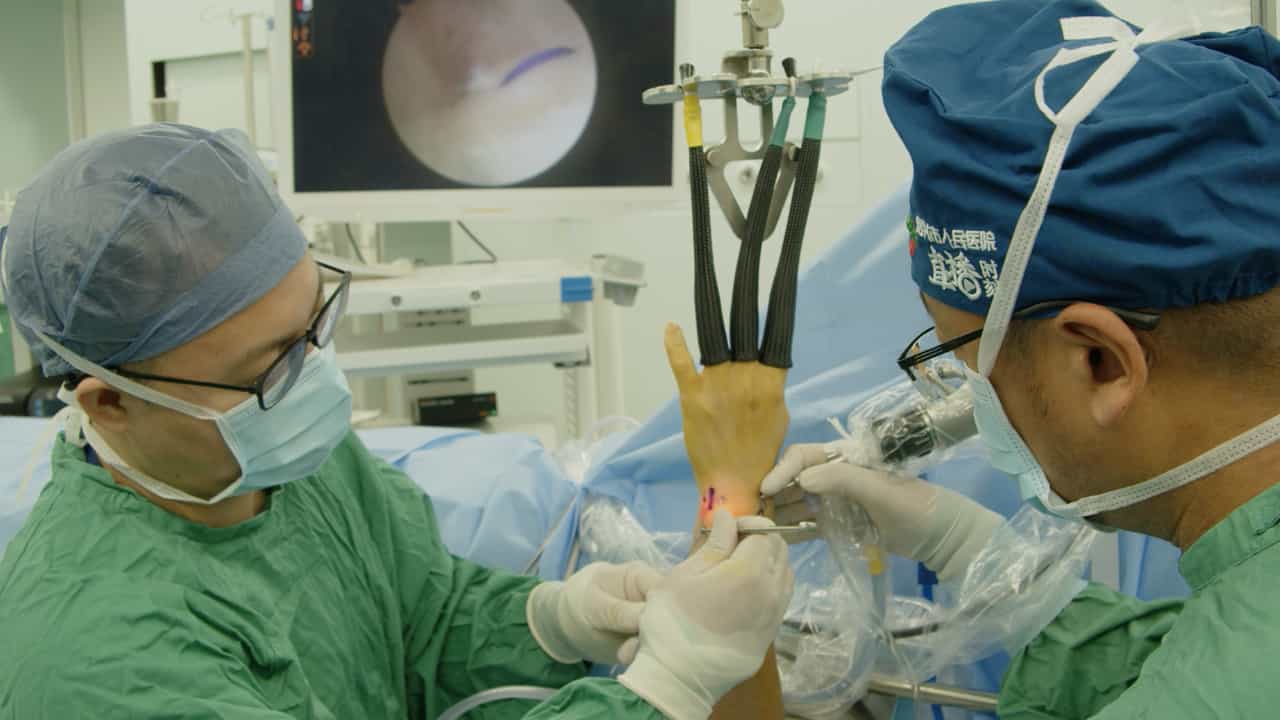

Novel Triple-Loop Technique for Suturing TFCC Injuries without Transosseous Tunnel
Published on: May 23, 2025
Association between imaging parameter changes and triangular fibrocartilage complex injury after distal radius
Chunye Tan1, Zeyu Wang1, Linwei Li2,3
1First People's Hospital of Changzhou Affiliated to Soochow University, Changzhou, Jiangsu, People's Republic of China.

Background:
Triangular fibrocartilage complex (TFCC) injury is a frequent soft tissue injury that has been observed to accompany distal radius fractures (DRFs) with concomitant changes in radiologic parameters. The aim of this study was to investigate the relevance of distal radial radiologic parameters associated with DRF and traumatic TFCC injury.
Methods:
A total of 172 patients with distal radius fractures who underwent X-ray, CT, and MRI before undergoing volar locking plate or external splint fixation between October 2021 and December 2022 were included in this study. An analysis of various radiologic parameters and the classification of fracture type and TFCC injuries by CT and MRI was performed. All patients were divided into the TFCC uninjured group and the injured group. The incidence and relevant radiologic parameters were compared.
Results:
This study included 76 males and 96 females with a mean age of 56.1 years. Among all patients, 33 (19.2%), 40 (23.2%), and 99 (57.6%) had DRF with A, B, and C fractures, respectively, according to the AO/OTA classification. In patients with fractures, the TFCC was found to be injured in 54.1% (93/172) of patients (type 1A in 21, 1B in 46, 1C in 39, and 1D in 35) but uninjured in 45.9% (79/172). There were significant differences between the TFCC injured and uninjured groups regarding the radius length (p = 0.044) and DRUJ distance (p = 0.040) of radiologic parameters that changed with DRF, although there were no differences between the two groups regarding gender, age, injured side, intra- and extra-articular, radius inclination and palmer tilt angle, or sagittal translation. Within the TFCC injured group, the radius length and DRUJ distance were 4.83 mm and 2.95 mm less or wider than 7.19 mm and 1.83 mm of the uninjured group. Moreover, shorter radius length was related to type lB TFCC injury (p = 0.041). Both radius length (AUC = 0.658) and DRUJ distance (AUC = 0.582) had no convincing predictive value for TFCC injury in DRF.
Conclusion:
1B TFCC injury is most common in patients with DRF and concomitant TFCC injury. Both radius length and DRUJ distance have a significant statistical correlation with TFCC injury, and patients with TFCC injury tend to have a shortened radius and wider DRUJ distance, although they have no predictive value for TFCC injury in DRF. In addition, a shorter radius length was related to type lB TFCC injury.
More Related Videos
 06:27
Author Spotlight: Investigating Early Events and Long-Term Effects of ACL Injuries for Osteoarthritis Progression
Published on: September 29, 2023
 08:36
Development of an Uncomplicated Mild Traumatic Brain Injury Model Modified by Weight-Drop Method and Evidenced by Magnetic Resonance Imaging
Published on: April 11, 2025