Related Experiment Video
Updated: Jul 8, 2025
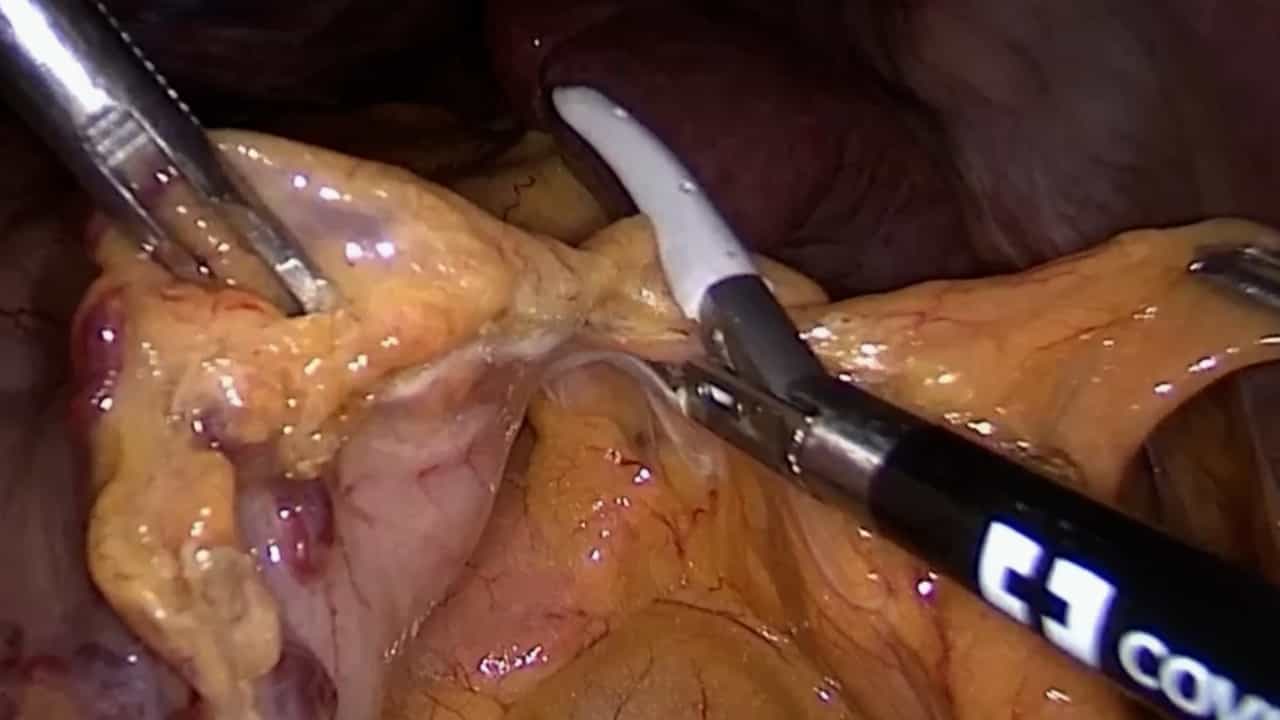

Application of Laparoscopic Partial Splenectomy with Total Blood Flow Occlusion in Benign Splenic Lesions
Published on: December 20, 2024
Large supralevator haematoma: a dilemma in diagnosis and management
Nipasa Sarma1, Shripad Hebbar2, Ruthvika Kundoor3
1Junior Resident, Department of Obstetrics and Gynaecology, Kasturba Medical College, Manipal, Manipal Academy of higher education, Manipal, Karnataka, India nipasasharma@gmail.com shripad.hebbar@manipal.edu.

This is a case of postpartum haemorrhage following vaginal delivery of a primigravida in her late 20s resulting from a supralevator haematoma. She delivered in a low-resource hospital setting, with a late diagnosis of severe pre-eclampsia and haemolysis, elevated liver enzymes and low platelet count (HELLP), subsequently developed traumatic postpartum haemorrhage and vaginal haematoma, and was referred to our hospital for further management. She was constantly monitored, and serial ultrasonography revealed an expanding paravaginal haematoma. CT, 4 hours after admission, showed a large ill-defined collection with hyperdense areas of blood attenuation measuring ~8.0×6.2×12.2 cm in toto in the vaginal canal and right paravaginal region with supralevator extension, abutting the rectum posteriorly. The expanding haematoma caused gradual hypovolaemic shock, and hence, she was taken up for vaginal evacuation of supralevator haematoma with drainage tube insertion under ultrasound guidance. She received multiple blood product transfusion. Drain tube was removed on postoperative day 3. Follow-up scan was done and resolving haematoma noted. The patient was discharged on postoperative day 5 in a stable condition. She was followed up in outpatient department, and there was complete resolution of haematoma by 4 weeks.
This is a case of postpartum haemorrhage following vaginal delivery of a primigravida in her late 20s resulting from a supralevator haematoma. She delivered in a low-resource hospital setting, with a late diagnosis of severe pre-eclampsia and haemolysis, elevated liver enzymes and low platelet count (HELLP), subsequently developed traumatic postpartum haemorrhage and vaginal haematoma, and was referred to our hospital for further management. She was constantly monitored, and serial ultrasonography revealed an expanding paravaginal haematoma. CT, 4 hours after admission, showed a large ill-defined collection with hyperdense areas of blood attenuation measuring ~8.0×6.2×12.2 cm in toto in the vaginal canal and right paravaginal region with supralevator extension, abutting the rectum posteriorly. The expanding haematoma caused gradual hypovolaemic shock, and hence, she was taken up for vaginal evacuation of supralevator haematoma with drainage tube insertion under ultrasound guidance. She received multiple blood product transfusion. Drain tube was removed on postoperative day 3. Follow-up scan was done and resolving haematoma noted. The patient was discharged on postoperative day 5 in a stable condition. She was followed up in outpatient department, and there was complete resolution of haematoma by 4 weeks.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations: