Related Experiment Video
Updated: Jul 8, 2025


Digital Home-Monitoring of Patients after Kidney Transplantation: The MACCS Platform
Published on: April 12, 2021
Managing comorbidities in chronic kidney disease reduces utilization and costs
Yong Li1, Kanchan Barve2, Meghan Cockrell2
1Humana Healthcare Research, Humana Inc, 500 W Main Street, Louisville, KY, 40202, USA. yli4@humana.com.

Insights
Effective management of diabetes and hypertension in chronic kidney disease (CKD) patients lowers healthcare use and costs. Controlling glucose and blood pressure is key for CKD care coordination.
Area of Science:
- Nephrology
- Endocrinology
- Health Services Research
Background:
- Chronic kidney disease (CKD) management is complex, especially with comorbid diabetes and hypertension.
- Understanding the health plan perspective on managing these comorbidities in CKD is crucial for optimizing patient outcomes.
- This study addresses the gap in knowledge regarding the association between effective comorbid disease management and healthcare resource utilization (HCRU) in CKD patients.
Purpose of the Study:
- To evaluate the association between effective management of comorbid diabetes and/or hypertension and HCRU in patients with CKD.
- To analyze the impact of disease control on healthcare utilization from a health plan perspective.
- To identify key management strategies that influence HCRU in the CKD population.
Main Methods:
- Retrospective cohort study using the Humana Research Database (2017).
- Included patients with CKD Stage ≥3a, enrolled in Medicare Advantage Prescription Drug plans for ≥12 months pre- and post-index date.
- Excluded patients with end-stage renal disease, kidney transplant, or hospice preindex. Assessed adherence to monitoring (HbA1c), medications (glucose-lowering, cardiovascular, ACEi/ARB), and provider visits (nephrologist/PCP). HCRU evaluated for 12 months postindex.
Main Results:
- A cohort of 241,628 patients (55% female, 77% White, average age 75) with Stage 3 CKD was analyzed.
- Patients meeting good disease management criteria showed significantly lower rates of inpatient hospitalization (up to 40% reduction) and emergency department visits (up to 30% reduction).
- Total monthly healthcare costs were reduced by as much as 17% for well-managed patients compared to those not meeting criteria.
Conclusions:
- Effective management of comorbid diabetes and hypertension in CKD patients is associated with reduced healthcare resource utilization and lower overall costs.
- Care coordination programs for CKD patients should prioritize stringent glucose and blood pressure control.
- Optimizing management of these common comorbidities can lead to significant economic benefits and improved patient care pathways.
Background:
Effective management of comorbid diabetes and hypertension in patients with chronic kidney disease (CKD) is important for optimal outcomes. However, little is known about this relationship from a health plan perspective. The objective of this study was to evaluate the association of effective management of comorbid diabetes and/or hypertension with healthcare resource utilization (HCRU) in patients with chronic kidney disease (CKD).
Methods:
This retrospective cohort study used the Humana Research Database to identify patients with CKD Stage ≥ 3a in 2017. Eligible patients were enrolled in a Medicare Advantage Prescription Drug plan for ≥ 12 months before and after the index date (first observed evidence of CKD). Patients with end-stage renal disease, kidney transplant, or hospice election preindex were excluded. Recommended comorbid disease management included hemoglobin A1c monitoring; adherence to glucose-lowering, cardiovascular, and angiotensin-converting enzyme inhibitors/angiotensin receptor blocker medications; and nephrologist/primary care provider (PCP) visits. HCRU was evaluated for 12 months postindex.
Results:
The final cohort of 241,628 patients was 55% female and 77% White, with an average age of 75 years. Approximately 90% of patients had Stage 3 CKD. Half had both diabetes and hypertension, and most of the remaining half had hypertension without diabetes. Patients meeting the criteria for good disease management, compared with patients not meeting those criteria, were less likely to experience an inpatient hospitalization, by as much as 40% depending on the criterion and the comorbidities present, or an emergency department visit, by as much as 30%. Total monthly healthcare costs were as much as 17% lower.
Conclusions:
Management of comorbid diabetes and hypertension in patients with CKD was associated with lower HCRU and costs. Care coordination programs targeting patients with CKD must give careful attention to glucose and blood pressure control.
Trial Registration:
Not applicable.


Related Concept Videos
 01:22
Heart Failure Drugs: Diuretics
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:29
Chronic Obstructive Pulmonary Disease-V: Management
Smoking Cessation
 01:15
Methods of Documentation VI: Case Management Model
For example, a patient with a chronic...
 01:06
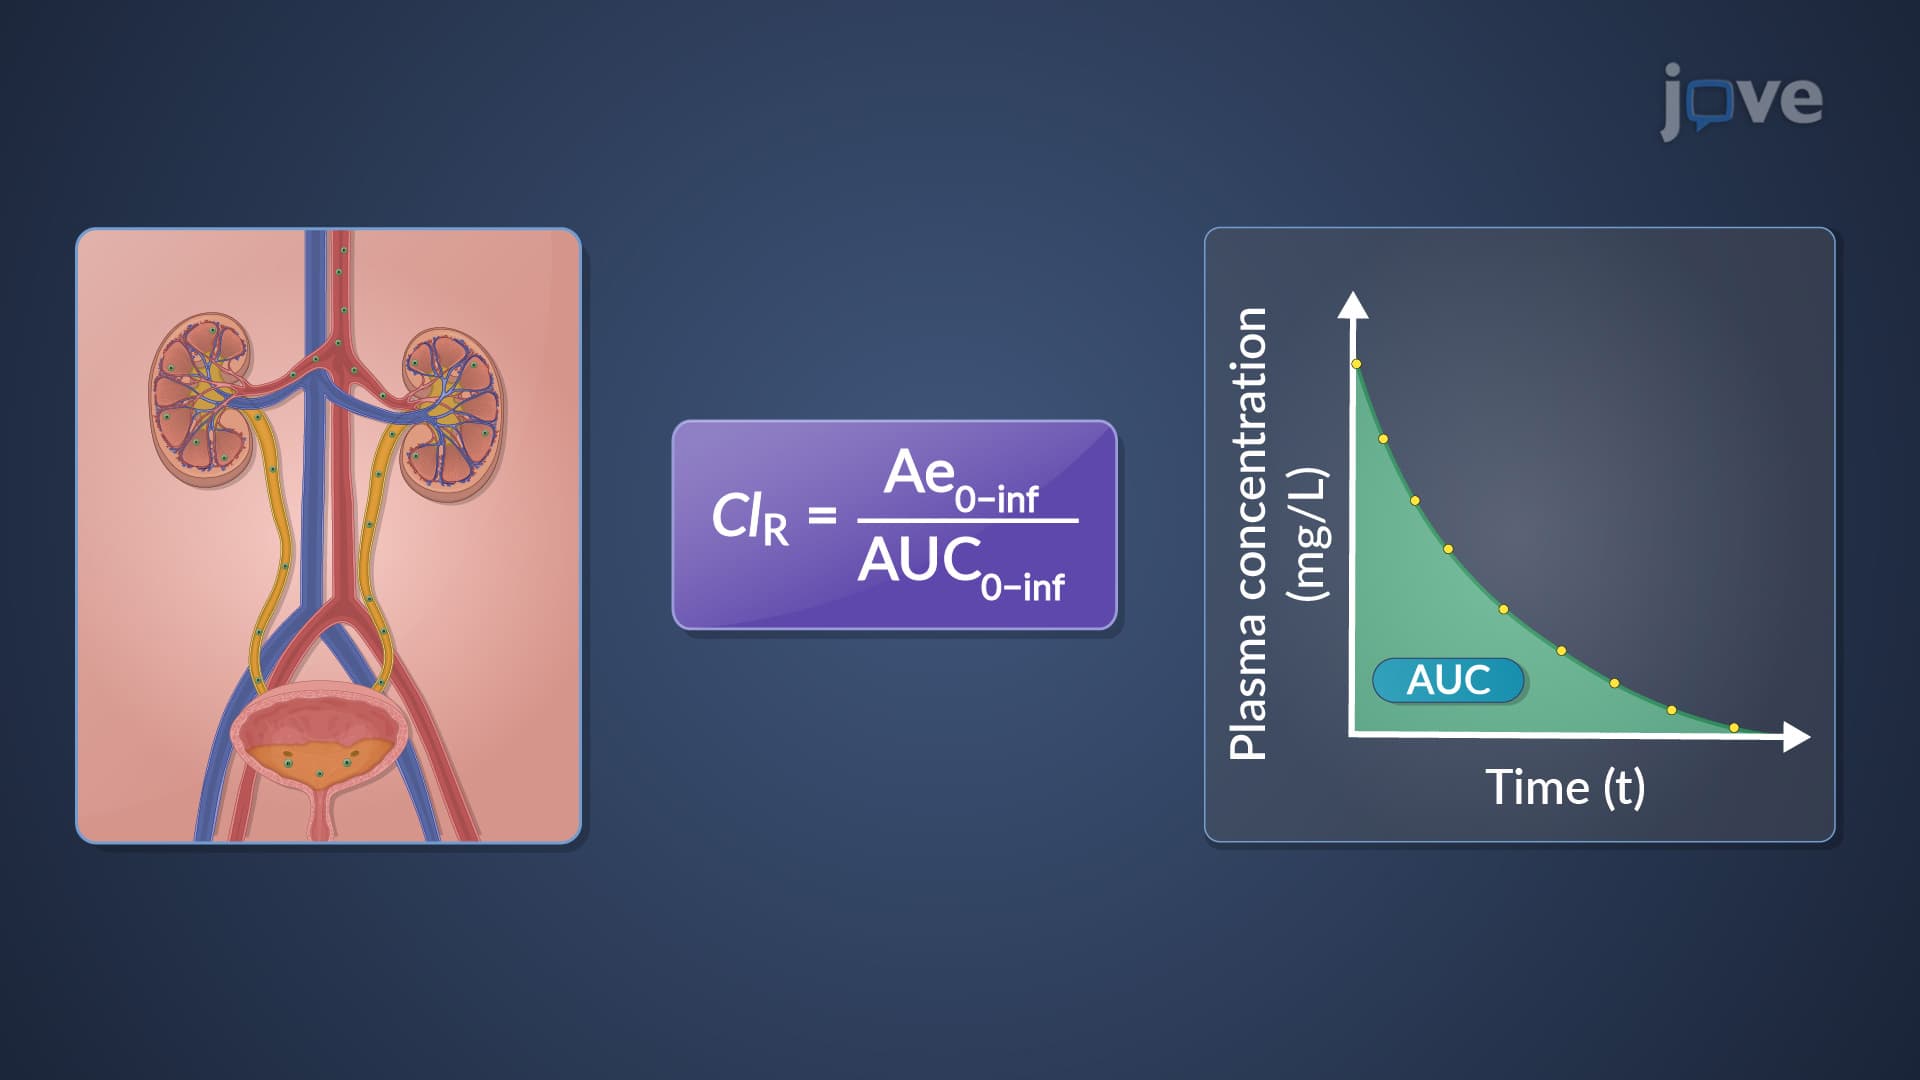
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...