Related Experiment Video
Updated: Jun 26, 2026
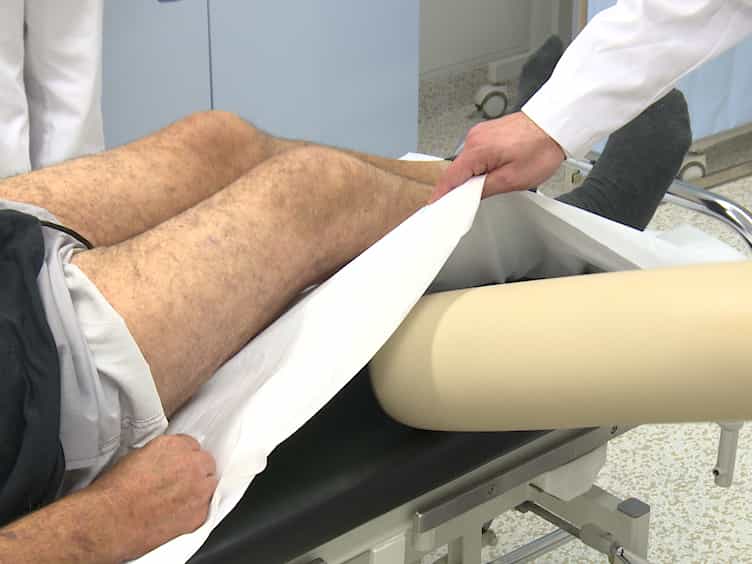

Novel Diagnostics in Revision Arthroplasty: Implant Sonication and Multiplex Polymerase Chain Reaction
Published on: December 3, 2017
Prosthetic joint infections: 6 weeks of oral antibiotics results in a low failure rate
Pierre-Marie Roger1,2, Frédéric Assi1, Eric Denes3
1Infectiologie, Clinique Les Fleurs, Ave Frédéric Mistral, Ollioules, France.

Background:
Need for parenteral administration and total duration of antibiotic therapy for prosthetic joint infection (PJI) are debated. We report our PJI management, in which outpatient care is privileged.
Methods:
This was a retrospective multicentre cohort study of PJI managed from January 2017 to Jun 2021. Microbial diagnosis was based on surgical samples. Surgical procedures and antibiotic treatments were reported. Chronic PJI was defined by a course >1 month. Oral antibiotic therapy (OAT) was defined by exclusive use of oral antibiotics or by ≤3 days of parenteral treatments. Management failure was defined by clinical and/or microbial relapse of PJI over 24 months after surgical treatment.
Results:
One hundred and seventy-two patients from 13 institutions were included: 103 were male (60%) and mean age was (±SD): 73 ± 12 years. Sites for PJI were mainly hip (50%) and knee (35%), being chronic infections in 70 cases (41%). The main bacterial genus in monomicrobial infections was Staphylococcus spp. (60%). We recorded 41 (24%) implant exchanges. An OAT was prescribed in 76 cases (44%), and the median (range) course for parenteral route was 6 days (4-180) for 96 cases. Median (range) duration of antimicrobials was 42 days (21-180). Management failure was observed in 7/76 (9.2%) cases treated with OAT and 15/96 (15.6%) treated with prolonged parenteral therapy. In multivariate analysis, risk factors for failure were a knee PJI [adjusted OR (95% CI) = 3.27 (1.27-8.40)] and a polymicrobial infection [4.09 (1.46-11.49)].
Conclusions:
OAT for 6 weeks for PJI was associated with a low rate of management failure.
Insights
Oral antibiotic therapy (OAT) for prosthetic joint infection (PJI) over six weeks shows a low failure rate. This approach prioritizes outpatient care for PJI management, offering a viable alternative to prolonged parenteral treatments.
Area of Science:
- Orthopedics
- Infectious Diseases
- Pharmacology
Background:
- Prosthetic joint infection (PJI) management often involves debated antibiotic administration routes and durations.
- Outpatient care is increasingly favored for PJI treatment strategies.
Purpose of the Study:
- To evaluate the efficacy of oral antibiotic therapy (OAT) in managing prosthetic joint infections (PJI).
- To compare management failure rates between OAT and prolonged parenteral antibiotic therapy for PJI.
Main Methods:
- A retrospective multicenter cohort study included 172 patients with PJI from January 2017 to June 2021.
- Microbial diagnosis was based on surgical samples; chronic PJI was defined as >1 month duration.
- Oral antibiotic therapy (OAT) was defined as exclusive oral antibiotics or ≤3 days of parenteral treatment; management failure was assessed over 24 months post-surgery.
Main Results:
- Of 172 patients, 44% received OAT. Management failure occurred in 9.2% of OAT cases versus 15.6% of prolonged parenteral therapy cases.
- Risk factors for failure included knee PJI (adjusted OR 3.27) and polymicrobial infection (adjusted OR 4.09).
- The median duration of antimicrobial therapy was 42 days.
Conclusions:
- Oral antibiotic therapy (OAT) for prosthetic joint infection (PJI) over six weeks is associated with a low rate of management failure.
- This supports the use of OAT as a primary management strategy for PJI, potentially reducing the need for prolonged inpatient parenteral antibiotic administration.

Related Concept Videos
 01:26
Tonsillitis II: Management
 01:18
Endocarditis III: Medical Management
 01:29
Endocarditis IV: Nursing Management
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:26
Rocky Mountain Spotted Fever
 01:28
Diphtheria