Related Experiment Video
Updated: Jul 8, 2025
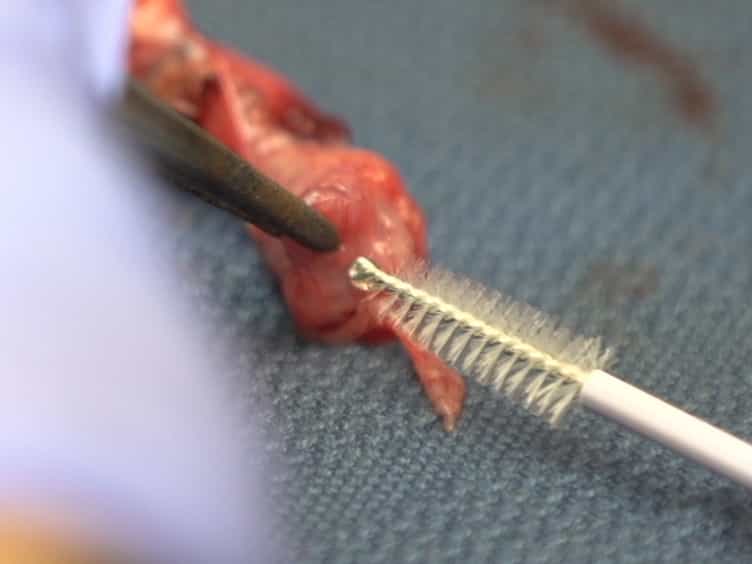

Tubal Cytology of the Fallopian Tube as a Promising Tool for Ovarian Cancer Early Detection
Published on: July 25, 2017
Bilateral or unilateral tubo-ovarian abscess: exploring its clinical significance
Yael Yagur1, Omer Weitzner2, Rebecca Shams2
1Department of Obstetrics and Gynecology, Meir Medical Center, Kfar Saba, Israel affiliated with The School of Medicine, Tel Aviv University, Tel Aviv, Israel. yaelyagur@gmail.com.

Objectives:
To assess the characteristics of patients with unilateral and bilateral tubo-ovarian abscess (TOA).
Methods:
Women diagnosed with TOA during 2003-2017 were included in this retrospective cohort study. TOA was diagnosed using sonography or computerized tomography and clinical criteria, or by surgical diagnosis. Demographics, sonographic data, clinical treatment, surgical treatment, and post-operative information were retrieved.
Results:
The study cohort included 144 women who met the inclusion criteria, of whom 78 (54.2%) had unilateral TOA and 66 (45.8%) had bilateral TOA. Baseline characteristics were not different between the groups. There was a statistical trend that women with fewer events of previous PID were less likely to have with bilateral TOA (75.3% vs. 64.1%, respectively; p = 0.074). Women diagnosed with bilateral TOA were more likely to undergo surgical treratment for bilateral salpingo-oophorectomy compared to unilateral TOA (61.5% vs. 42.3%, respectively; p = 0.04). There was no difference in maximum TOA size between groups.
Conclusions:
This study detected a trend toward increased need for surgical treatment in women diagnosed with bilateral TOA. These findings may contribute to determining the optimal medical or surgical treatment, potentially leading to a decrease in the duration of hospitalization, antibiotic exposure, and resistance. However, it is important to acknowledge that the results of the current study are limited, and further research is warranted to validate these potential outcomes.

Related Concept Videos
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 02:07
Oogenesis
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:30
Inflammatory Bowel Disease II: Crohn's Disease
Inflammatory bowel disease, commonly known as IBD, refers to a collection of disorders that lead to persistent inflammation of the gastrointestinal tract. The two types of IBD are ulcerative colitis, which impacts the colon, and Crohn's disease, which can involve any part of the gastrointestinal segment.
Crohn's disease
Crohn's disease is a chronic, systemic inflammatory bowel disease (IBD) that predominantly affects the gastrointestinal tract. It is marked by...