Related Experiment Video
Updated: Jul 8, 2025
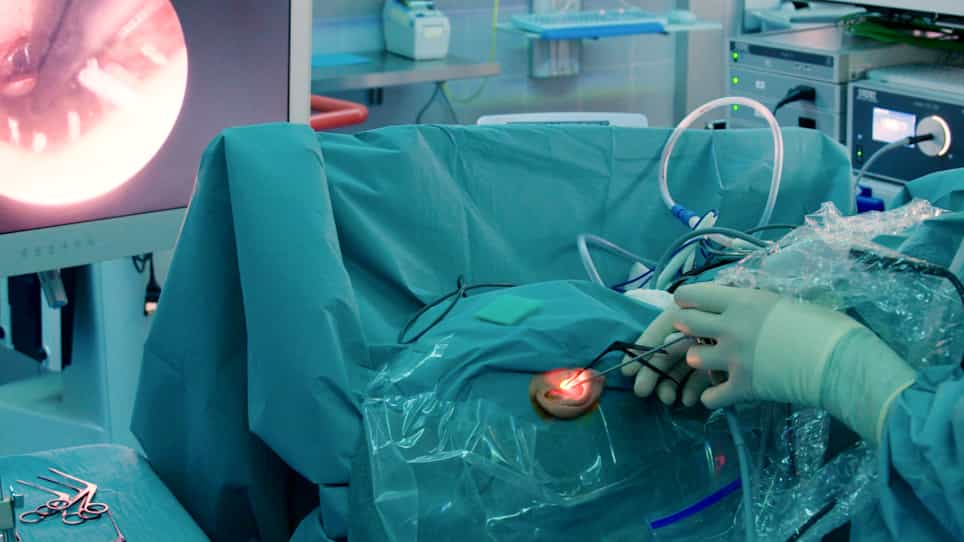

Endoscopic Cholesteatoma Surgery
Published on: January 19, 2022
Experience in the management of sigmoid sinus thrombophlebitis secondary to middle ear cholesteatoma
Jing Fei1, Xiao-Wen Peng1, Ting-Yu Yang1
1Department of Otorhinolaryngology, Head and Neck Surgery, Affiliated Hospital of Southwest Medical University, 25 Taiping Street, Luzhou City, 646000, Sichuan Province, China.

Objective:
To discuss the management of sigmoid sinus thrombophlebitis secondary to middle ear cholesteatoma.
Methods:
We retrospectively analyzed all cases of sigmoid sinus thrombophlebitis caused by middle ear cholesteatoma over a period of 7 years. 7 male and 2 female patients, ranging in age from 9 to 66 years, were diagnosed with sigmoid sinus thrombophlebitis by clinical presentation and radiological examination. By executing a modified mastoidectomy and tympanoplasty (canal wall-down tympanoplasty) to entirely remove the cholesteatoma-like mastoid epithelium, all patients were effectively treated surgically without opening the sigmoid sinus. All patients were treated with broad-spectrum antibiotics, but no anticoagulants were used.
Results:
9 patients had otogenic symptoms such as ear pus, tympanic membrane perforation, and hearing loss. In the initial stage of the surgery, modified mastoidectomy and tympanoplasty were performed on 8 of the 9 patients. 1 patient with a brain abscess underwent puncturing (drainage of the abscess) to relieve cranial pressure, and 4 months later, a modified mastoidectomy and tympanoplasty were carried out. Following surgery and medication, the clinical symptoms of every patient improved. After the follow-up of 6 months to 7 years, 3 patients were re-examined for MRV and showed partial sigmoid sinus recovery with recanalization. 4 months following middle ear surgery, the extent of a patient's brain abscess lesions was significantly reduced. 1 patient experienced facial paralysis after surgery and recovered in 3 months. None of the patients had a secondary illness, an infection, or an abscess in a distant organ.
Conclusion:
The key to a better prognosis is an adequate course of perioperative antibiotic medication coupled with surgical treatment. A stable sigmoid sinus thrombus can remain for a long time after middle ear lesions have been removed, and it is less likely to cause infection and abscesses in the distant organs. The restoration of middle ear ventilation is facilitated by tympanoplasty. It is important to work more closely with multidisciplinary teams such as neurology and neurosurgery when deciding whether to perform lateral sinusotomies to remove thrombus or whether to administer anticoagulation.
Related Concept Videos
 01:26
Tonsillitis II: Management
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:23
Chronic Pharyngitis
Etiology
It often arises from persistent viral or bacterial infections affecting sinuses and tonsils.
Additional contributing factors include inadequate dental hygiene, mouth breathing, recurring tonsillitis, allergic rhinitis, laryngopharyngeal reflux, and exposure to smoke, chemicals, and other environmental pollutants. Allergic reactions to pollen, mold, and pet dander, chronic cough, excessive voice usage,...