Related Experiment Video
Updated: Jul 7, 2025
Simultaneous Application of Transcranial Direct Current Stimulation during Virtual Reality Exposure
Published on: January 18, 2021
The Effects of Virtual Reality Telemedicine With Pediatric Patients Diagnosed With Posttraumatic Stress Disorder:
1TheraVR Inc, Emeryville, CA, United States.

Insights
Virtual reality (VR) telehealth effectively reduced PTSD symptoms in a child, improving engagement and self-coping strategies. This novel approach shows promise for pediatric trauma treatment.
Area of Science:
- Psychiatry and Behavioral Sciences
- Pediatric Psychology
- Digital Health Interventions
Background:
- Trauma-focused cognitive behavioral therapy (TF-CBT) is standard for pediatric PTSD.
- COVID-19 highlighted the need for novel, technology-based pediatric PTSD treatments.
- Virtual reality (VR) offers a new avenue for delivering TF-CBT as telehealth.
Observation:
- A 10-year-old girl with early-onset PTSD received TF-CBT over 7 months.
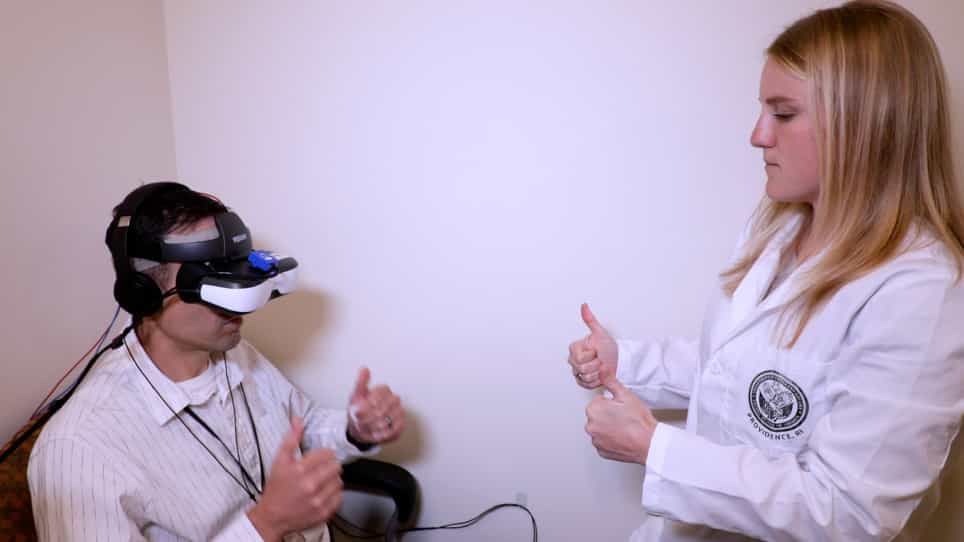
- Treatment progressed from standard telehealth to 2D VR, then to head-mounted device (HMD) VR with TheraVR software.
- Patient engagement and symptom reduction were monitored throughout the telehealth intervention.
Findings:
- Significant reduction in PTSD symptoms occurred as treatment transitioned to VR.
- VR telehealth, particularly with avatar technology, increased patient retention and adherence.
- The patient independently developed coping mechanisms using VR environments for emotional regulation.
Implications:
- VR telehealth is a potentially effective modality for pediatric trauma care.
- This approach can enhance patient engagement and treatment outcomes in young populations.
- Further research with larger trials is warranted to validate VR for severe pediatric trauma.
Background:
Trauma-focused cognitive behavioral therapy (TF-CBT) strategies are common interventions to treat child trauma and a posttraumatic stress disorder (PTSD) diagnosis in children with histories of sexual and physical abuse. With the advent of COVID-19, the disruption of child development combined with intense exposure to technology and screen time indicate a need for delivering other novel approaches to treat pediatric PTSD. Virtual reality (VR) has been used with evidence-based TF-CBT as an intervention in lab-based settings, but never as telehealth. Such technologies, including a VR head-mounted device (HMD) programmed with novel TheraVR software, for psychotherapy and treating trauma-related symptoms could redefine how pediatric populations respond to treatment.
Objective:
The aim of this exploratory single-case study was to reflect symptom improvement and patient engagement using VR as telehealth.
Methods:
The patient was a 10-year-old girl of Middle Eastern descent diagnosed with trauma and comorbid medical conditions. The patient was in divorced joint parental custody and a Child Protective Services report was made with referral for therapy. Night terrors, hallucinations, depression, anxiety, isolation, and encopresis symptoms were assessed at the beginning of treatment. Clinical analysis met the criteria for a diagnosis of early onset PTSD, which was treated over the course of 7 months using TF-CBT. A cross-analysis design was used to compare improved effectiveness in treatment and patient outcomes when moving from delivery of care with telehealth using desktop and tablet synchronous technology to 2D VR desktop telehealth with TheraVR software and subsequently HMD VR telehealth with TheraVR software. Sessions were conducted in private practice providing psychotherapy for remote patient care, collateral care with the family, and coordination of clinical care with the patient's pediatrician. Safety and protocols for reducing triggers were clinically monitored by the provider.
Results:
Over the course of treatment, and moving from standard telehealth to 2D VR to TheraVR with a standalone HMD, there was a significant reduction in PTSD symptoms. The transfer from using the standard video conferencing with face-to-face video to using customizable avatar technology with an assigned scene environment presented an increase in patient retention and follow-through with the treatment goals. The continuous use of delivery of care using VR with the TheraVR software demonstrated breakthrough clinical observations where the patient devised her own interventions for coping with mood, emotional regulation, and negative cognitive processes using the 10 different VR environments.
Conclusions:
This study shows the potential efficacy in using VR specifically for younger populations as a better modality of pediatrics care, while improving engagement with the provider through telehealth. These findings suggest the value of further research through larger clinical trials including pediatric patients diagnosed with severe trauma or trauma-related symptoms to assess the effectiveness of TheraVR software.