Related Experiment Video
Updated: Jul 7, 2025
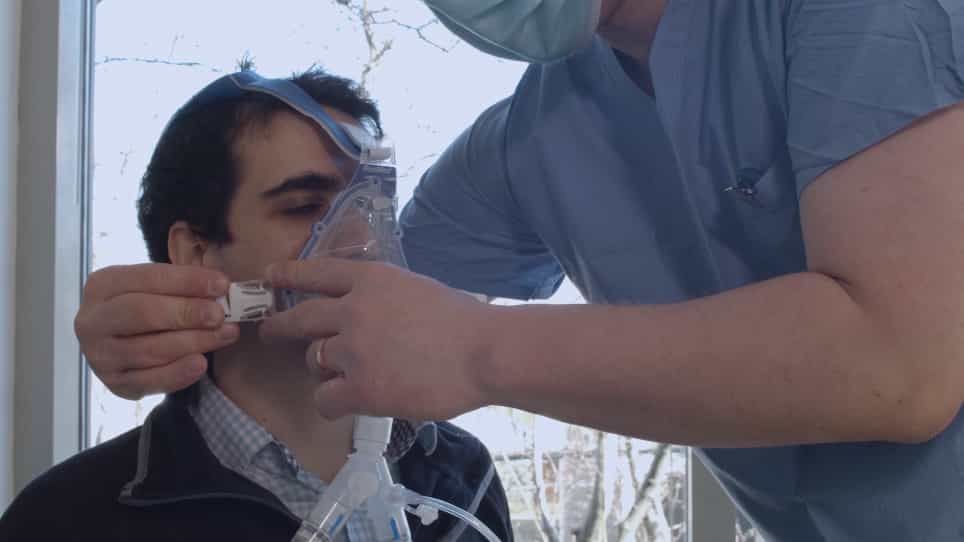

A Novel Inhalation Mask System to Deliver High Concentrations of Nitric Oxide Gas in Spontaneously Breathing Subjects
Published on: May 4, 2021
A Randomized Clinical Trial of Inhaled Nitric Oxide Treatment in Premature Infants Reveals the Effect of Maternal
Jeremy D Marks1, Michael D Schreiber1
1Departments of Pediatrics and Neurology, University of Chicago, Chicago, IL 60637, USA.

Respiratory distress syndrome increases the risk of death and bronchopulmonary dysplasia (BPD) in premature infants. Inhaled nitric oxide (iNO) may reduce these risks. Recent meta-analyses have suggested that iNO is effective only at doses higher than 5 ppm and in infants born to Black mothers. In a randomized, double-blinded, controlled trial, infants born before 32 0/7 weeks gestation, weighing <1500 g, and requiring respiratory support were assigned to receive iNO for either seven days (short iNO), or until 33 0/7 weeks PMA (long iNO). The primary outcome was death or BPD. A total of 273 patients were enrolled, of whom 83 receiving long iNO (61.5%) experienced the primary outcome, compared with 65 (47.1%) receiving short iNO (relative risk (RR) 1.37; 95% confidence interval (CI), 1.06-1.79; p = 0.017). This increase was due solely to increased BPD in infants weighing 750-999 g (RR 1.33, 95% CI 1.07-1.66, p = 0.009). However, there was no difference in the numbers of infants requiring supplemental oxygen at 40 weeks PMA. Among infants < 750 g, long-iNO-treated infants had a lower cumulative probability of death (χ2 5.12, p = 0.02). Long iNO increased the primary outcome in non-Black infants (RR 1.93, 95% CI 1.20-3.24) but not in Black infants. Understanding how maternal racial identity determines responses of premature infants to iNO may help narrow the gap in health outcomes between Black and non-Black infants.
Respiratory distress syndrome increases the risk of death and bronchopulmonary dysplasia (BPD) in premature infants. Inhaled nitric oxide (iNO) may reduce these risks. Recent meta-analyses have suggested that iNO is effective only at doses higher than 5 ppm and in infants born to Black mothers. In a randomized, double-blinded, controlled trial, infants born before 32 0/7 weeks gestation, weighing <1500 g, and requiring respiratory support were assigned to receive iNO for either seven days (short iNO), or until 33 0/7 weeks PMA (long iNO). The primary outcome was death or BPD. A total of 273 patients were enrolled, of whom 83 receiving long iNO (61.5%) experienced the primary outcome, compared with 65 (47.1%) receiving short iNO (relative risk (RR) 1.37; 95% confidence interval (CI), 1.06-1.79; p = 0.017). This increase was due solely to increased BPD in infants weighing 750-999 g (RR 1.33, 95% CI 1.07-1.66, p = 0.009). However, there was no difference in the numbers of infants requiring supplemental oxygen at 40 weeks PMA. Among infants < 750 g, long-iNO-treated infants had a lower cumulative probability of death (χ2 5.12, p = 0.02). Long iNO increased the primary outcome in non-Black infants (RR 1.93, 95% CI 1.20-3.24) but not in Black infants. Understanding how maternal racial identity determines responses of premature infants to iNO may help narrow the gap in health outcomes between Black and non-Black infants.

Related Concept Videos
 01:23
Upper Respiratory Drugs: Antitussives, Expectorants, and Mucolytics
Antitussives include codeine, dextromethorphan (Robitussin), and benzonatate (Tessalon). Codeine and dextromethorphan exert their effects centrally by suppressing the cough reflex center in the medulla. Benzonatate operates peripherally within the respiratory tract by...
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...