Related Experiment Video
Updated: Jul 7, 2025

A Novel Digital Platform for a Monitored Home-based Cardiac Rehabilitation Program
Published on: April 19, 2019
Cardiorespiratory fitness and risk of heart failure with preserved ejection fraction
Peter Kokkinos1,2,3, Charles Faselis4,5, Andreas Pittaras1,5
1Cardiology Division, DC Veterans Affairs Medical Center, Washington, DC, USA.

Aims:
Preventive strategies for heart failure with preserved ejection fraction (HFpEF) include pharmacotherapies and lifestyle modifications. However, the association between cardiorespiratory fitness (CRF) assessed objectively by a standardized exercise treadmill test (ETT) and the risk of HFpEF has not been evaluated. Thus, we evaluated the association between CRF and HFpEF incidence.
Methods And Results:
We assessed CRF in US Veterans (624 551 men; mean age 61.2 ± 9.7 years and 43 179 women; mean age 55.0 ± 8.9 years) by a standardized ETT performed between 1999 and 2020 across US Veterans Affairs Medical Centers. All had no evidence of heart failure or myocardial infarction prior to completion of the ETT. We assigned participants to one of five age- and gender-specific CRF categories (quintiles) based on peak metabolic equivalents (METs) achieved during the ETT and four categories based on CRF changes in those with two ETT evaluations (n = 139 434) ≥1.0 year apart. During a median follow-up of 10.1 years (interquartile range 6.0-14.3 years), providing 6 879 229 person-years, there were 16 493 HFpEF events with an average annual rate of 2.4 events per 1000 person-years. The adjusted risk of HFpEF decreased across CRF categories as CRF increased, independent of comorbidities. For fit individuals (≥10.5 METs) the hazard ratio (HR) was 0.48 (95% confidence interval [CI] 0.46-0.51) compared with least fit (≤4.9 METs; referent). Being unfit carried the highest risk (HR 2.88, 95% CI 2.67-3.11) of any other comorbidity. The risk of unfit individuals who became fit was 37% lower (HR 0.63, 95% CI 0.57-0.71), compared to those who remained unfit.
Conclusions:
Higher CRF levels are independently associated with lower HFpEF in a dose-response manner. Changes in CRF reflected proportional changes in HFpEF risk, suggesting that the HFpEF risk was modulated by CRF.

Related Concept Videos
 01:17
Pathophysiology of Heart Failure
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:29
Pathophysiology of Cardiac Performance
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
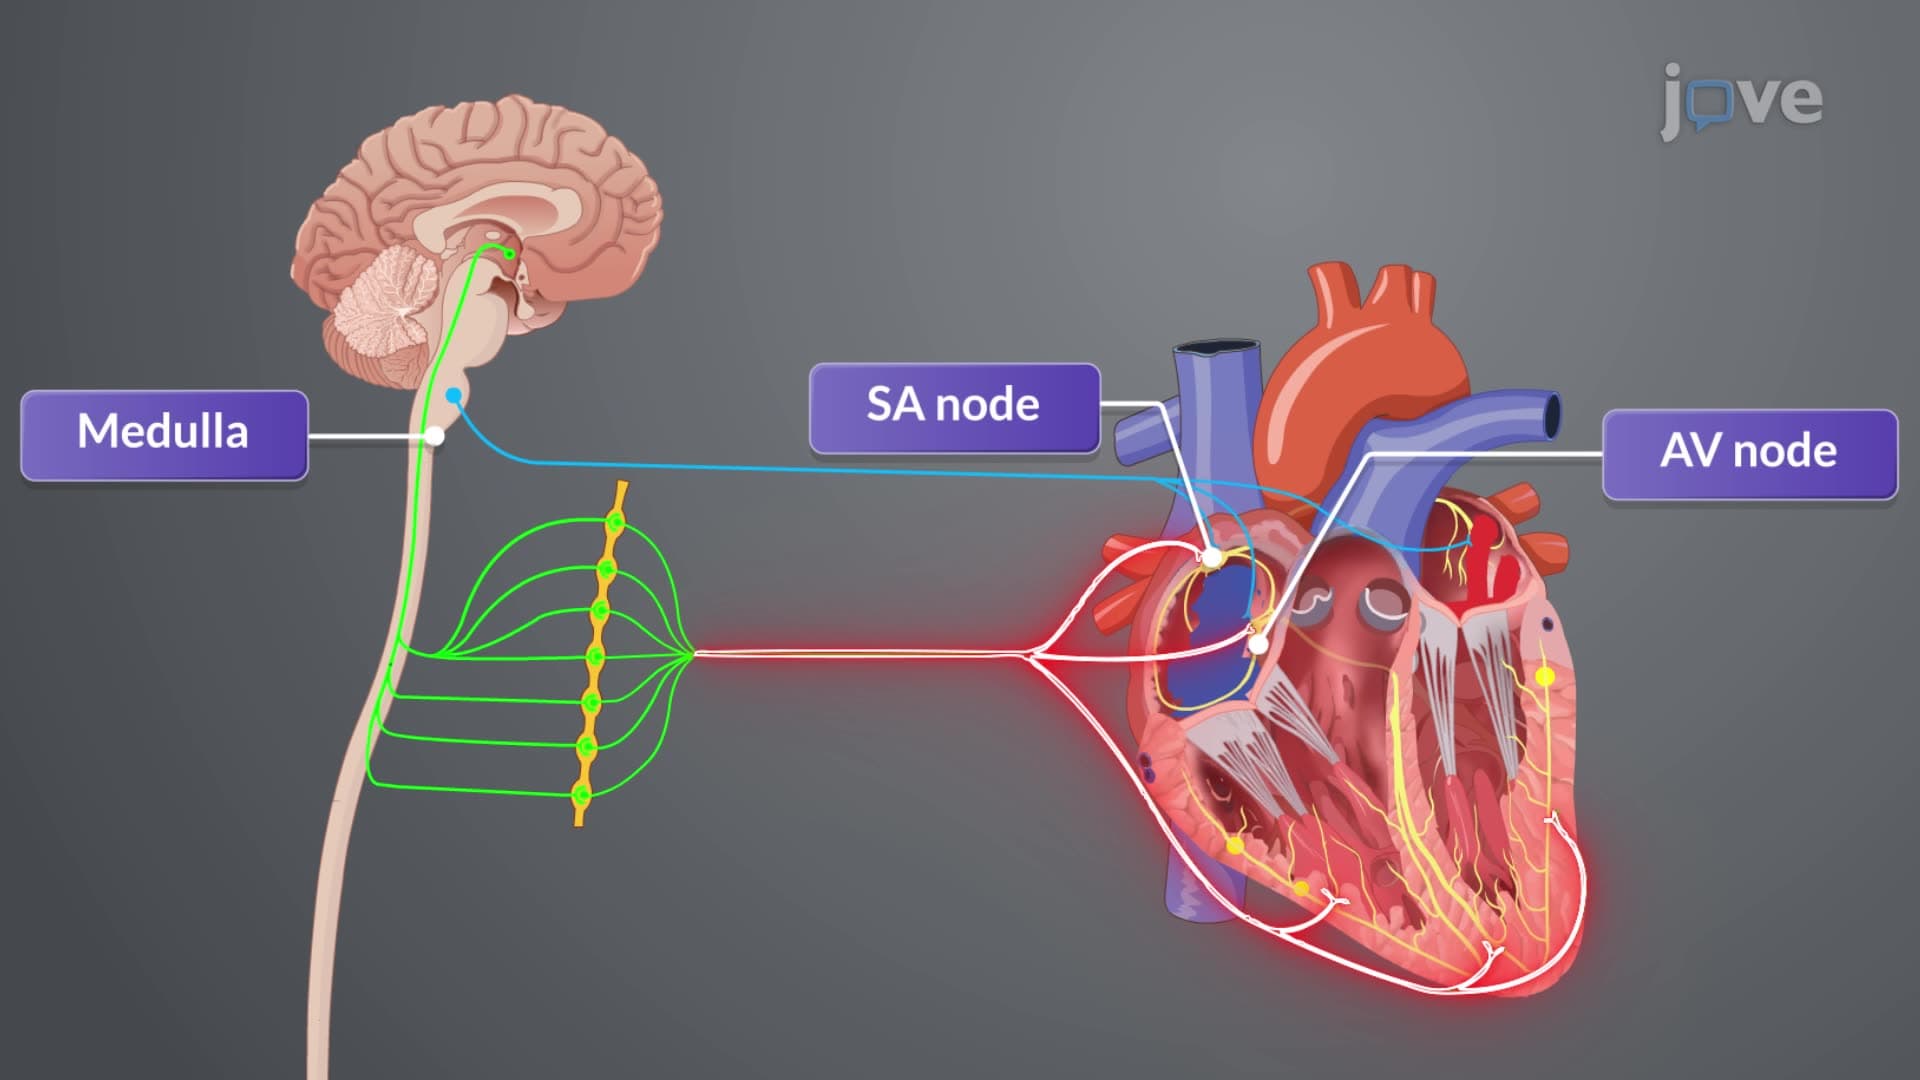
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...