Related Experiment Video
Updated: Jul 6, 2025

Breathing-controlled Electrical Stimulation BreEStim for Management of Neuropathic Pain and Spasticity
Published on: January 10, 2013
Altered locomotor muscle metaboreflex control of ventilation in patients with COPD
Liliane C Aranda1,2, Indyanara C Ribeiro1,2, Tiago O Freitas1,2
1Pulmonary Function and Clinical Exercise Physiology Unit (SEFICE), Division of Respiratory Medicine, Department of Medicine, Federal University of São Paulo (UNIFESP), São Paulo, Brazil.

Abstract:
We investigated the locomotor muscle metaboreflex control of ventilation, circulation, and dyspnea in patients with chronic obstructive pulmonary disease (COPD). Ten patients [forced expiratory volume in 1 second (FEV1; means ± SD) = 43 ± 17% predicted] and nine age- and sex-matched controls underwent 1) cycling exercise followed by postexercise circulatory occlusion (PECO) to activate the metaboreflex or free circulatory flow to inactivate it, 2) cold pressor test to interpret whether any altered reflex response was specific to the metaboreflex arc, and 3) muscle biopsy to explore the metaboreflex arc afferent side. We measured airflow, dyspnea, heart rate, arterial pressure, muscle blood flow, and vascular conductance during reflexes activation. In addition, we measured fiber types, glutathione redox balance, and metaboreceptor-related mRNAs in the vastus lateralis. Metaboreflex activation increased ventilation versus free flow in patients (∼15%, P < 0.020) but not in controls (P > 0.450). In contrast, metaboreflex activation did not change dyspnea in patients (P = 1.000) but increased it in controls (∼100%, P < 0.001). Other metaboreflex-induced responses were similar between groups. Cold receptor activation increased ventilation similarly in both groups (P = 0.46). Patients had greater type II skeletal myocyte percentage (14%, P = 0.010), lower glutathione ratio (-34%, P = 0.015), and lower nerve growth factor (NGF) mRNA expression (-60%, P = 0.031) than controls. Therefore, COPD altered the locomotor muscle metaboreflex control of ventilation. It increased type II myocyte percentage and elicited redox imbalance, potentially producing more muscle metaboreceptor stimuli. Moreover, it decreased NGF expression, suggesting a downregulation of metabolically sensitive muscle afferents.NEW & NOTEWORTHY This study's integrative physiology approach provides evidence for a specific alteration in locomotor muscle metaboreflex control of ventilation in patients with COPD. Furthermore, molecular analyses of a skeletal muscle biopsy suggest that the amount of muscle metaboreceptor stimuli derived from type II skeletal myocytes and redox imbalance overcame a downregulation of metabolically sensitive muscle afferents.

Related Concept Videos
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:22
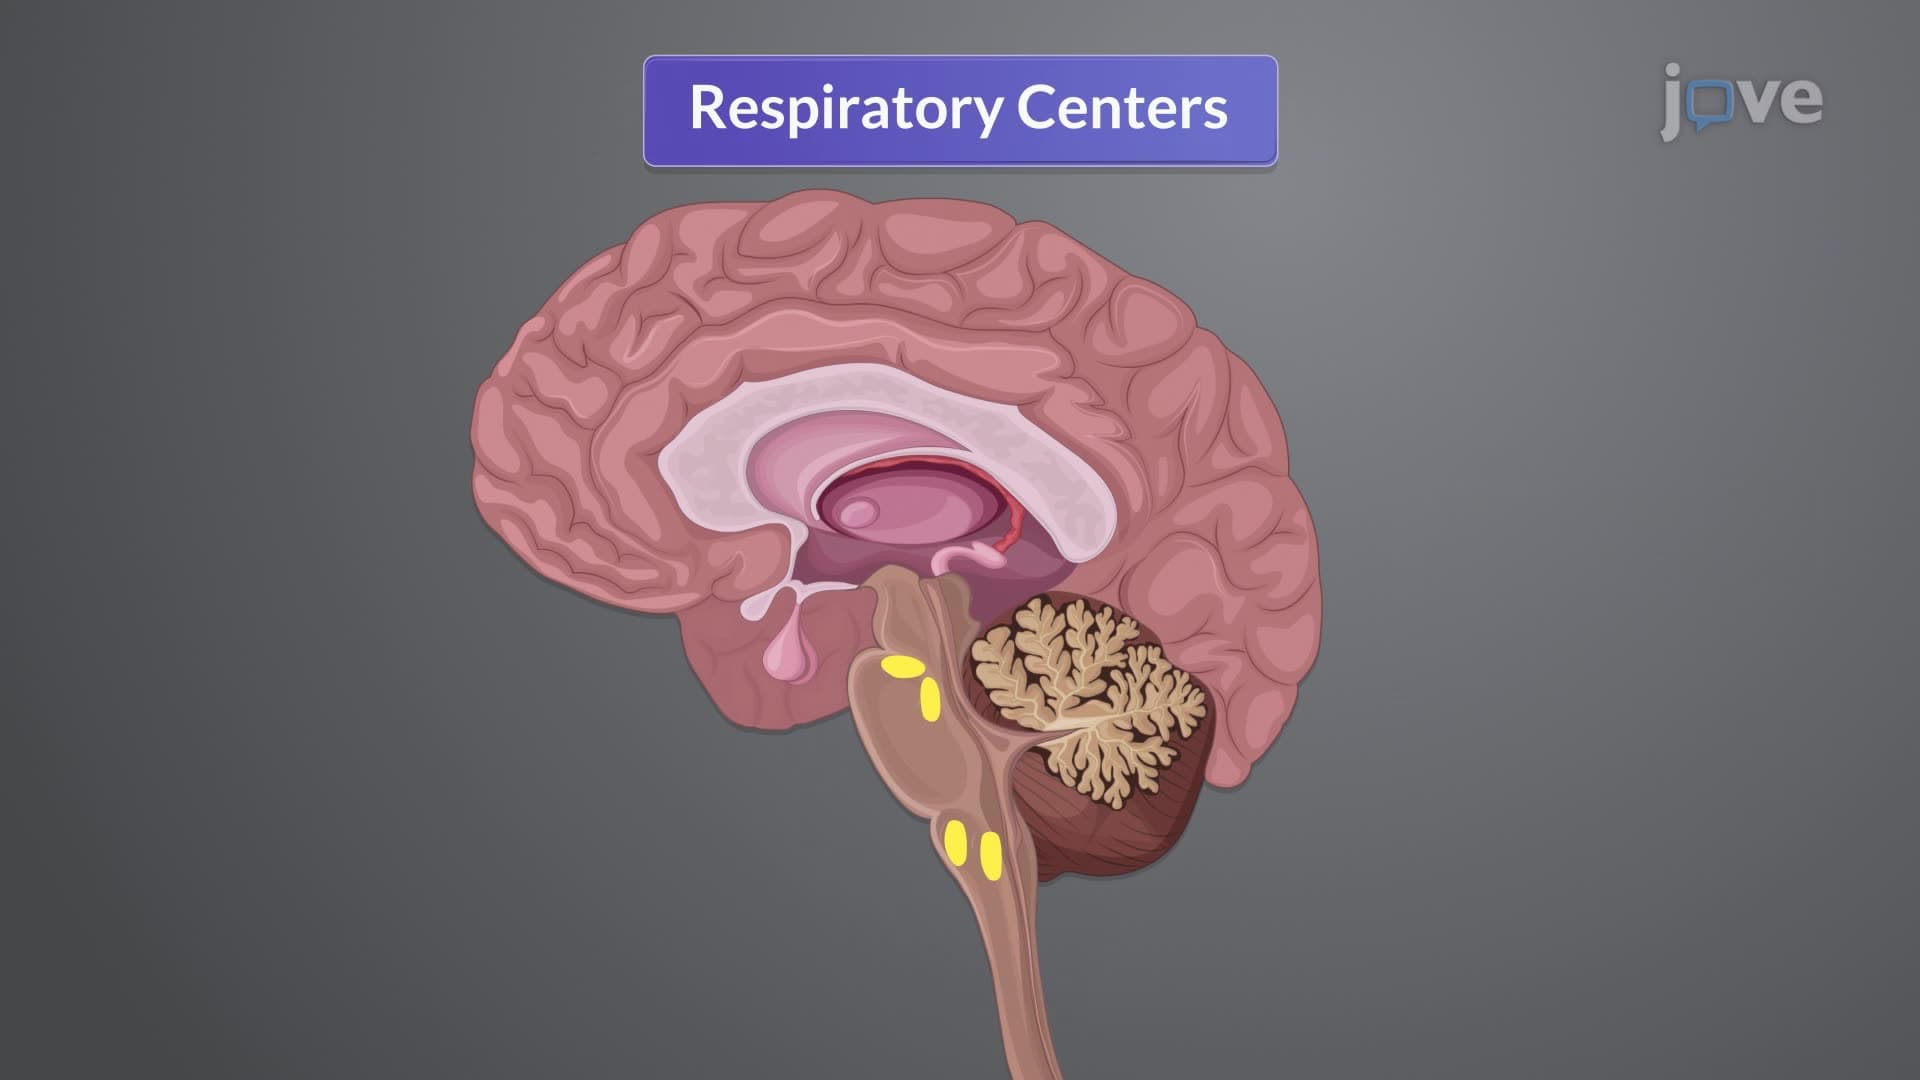
Physiology of Respiration II: Neurogenic Control of Respiration
Central Control
The brainstem is the primary site of central control, hosting respiratory centers:
 01:18
Neural Control of Respiration
Respiratory Centers in the Brainstem
Two primary areas comprise the respiratory center: the medullary respiratory center in the medulla oblongata and the pontine respiratory group in the pons. The...
 01:31
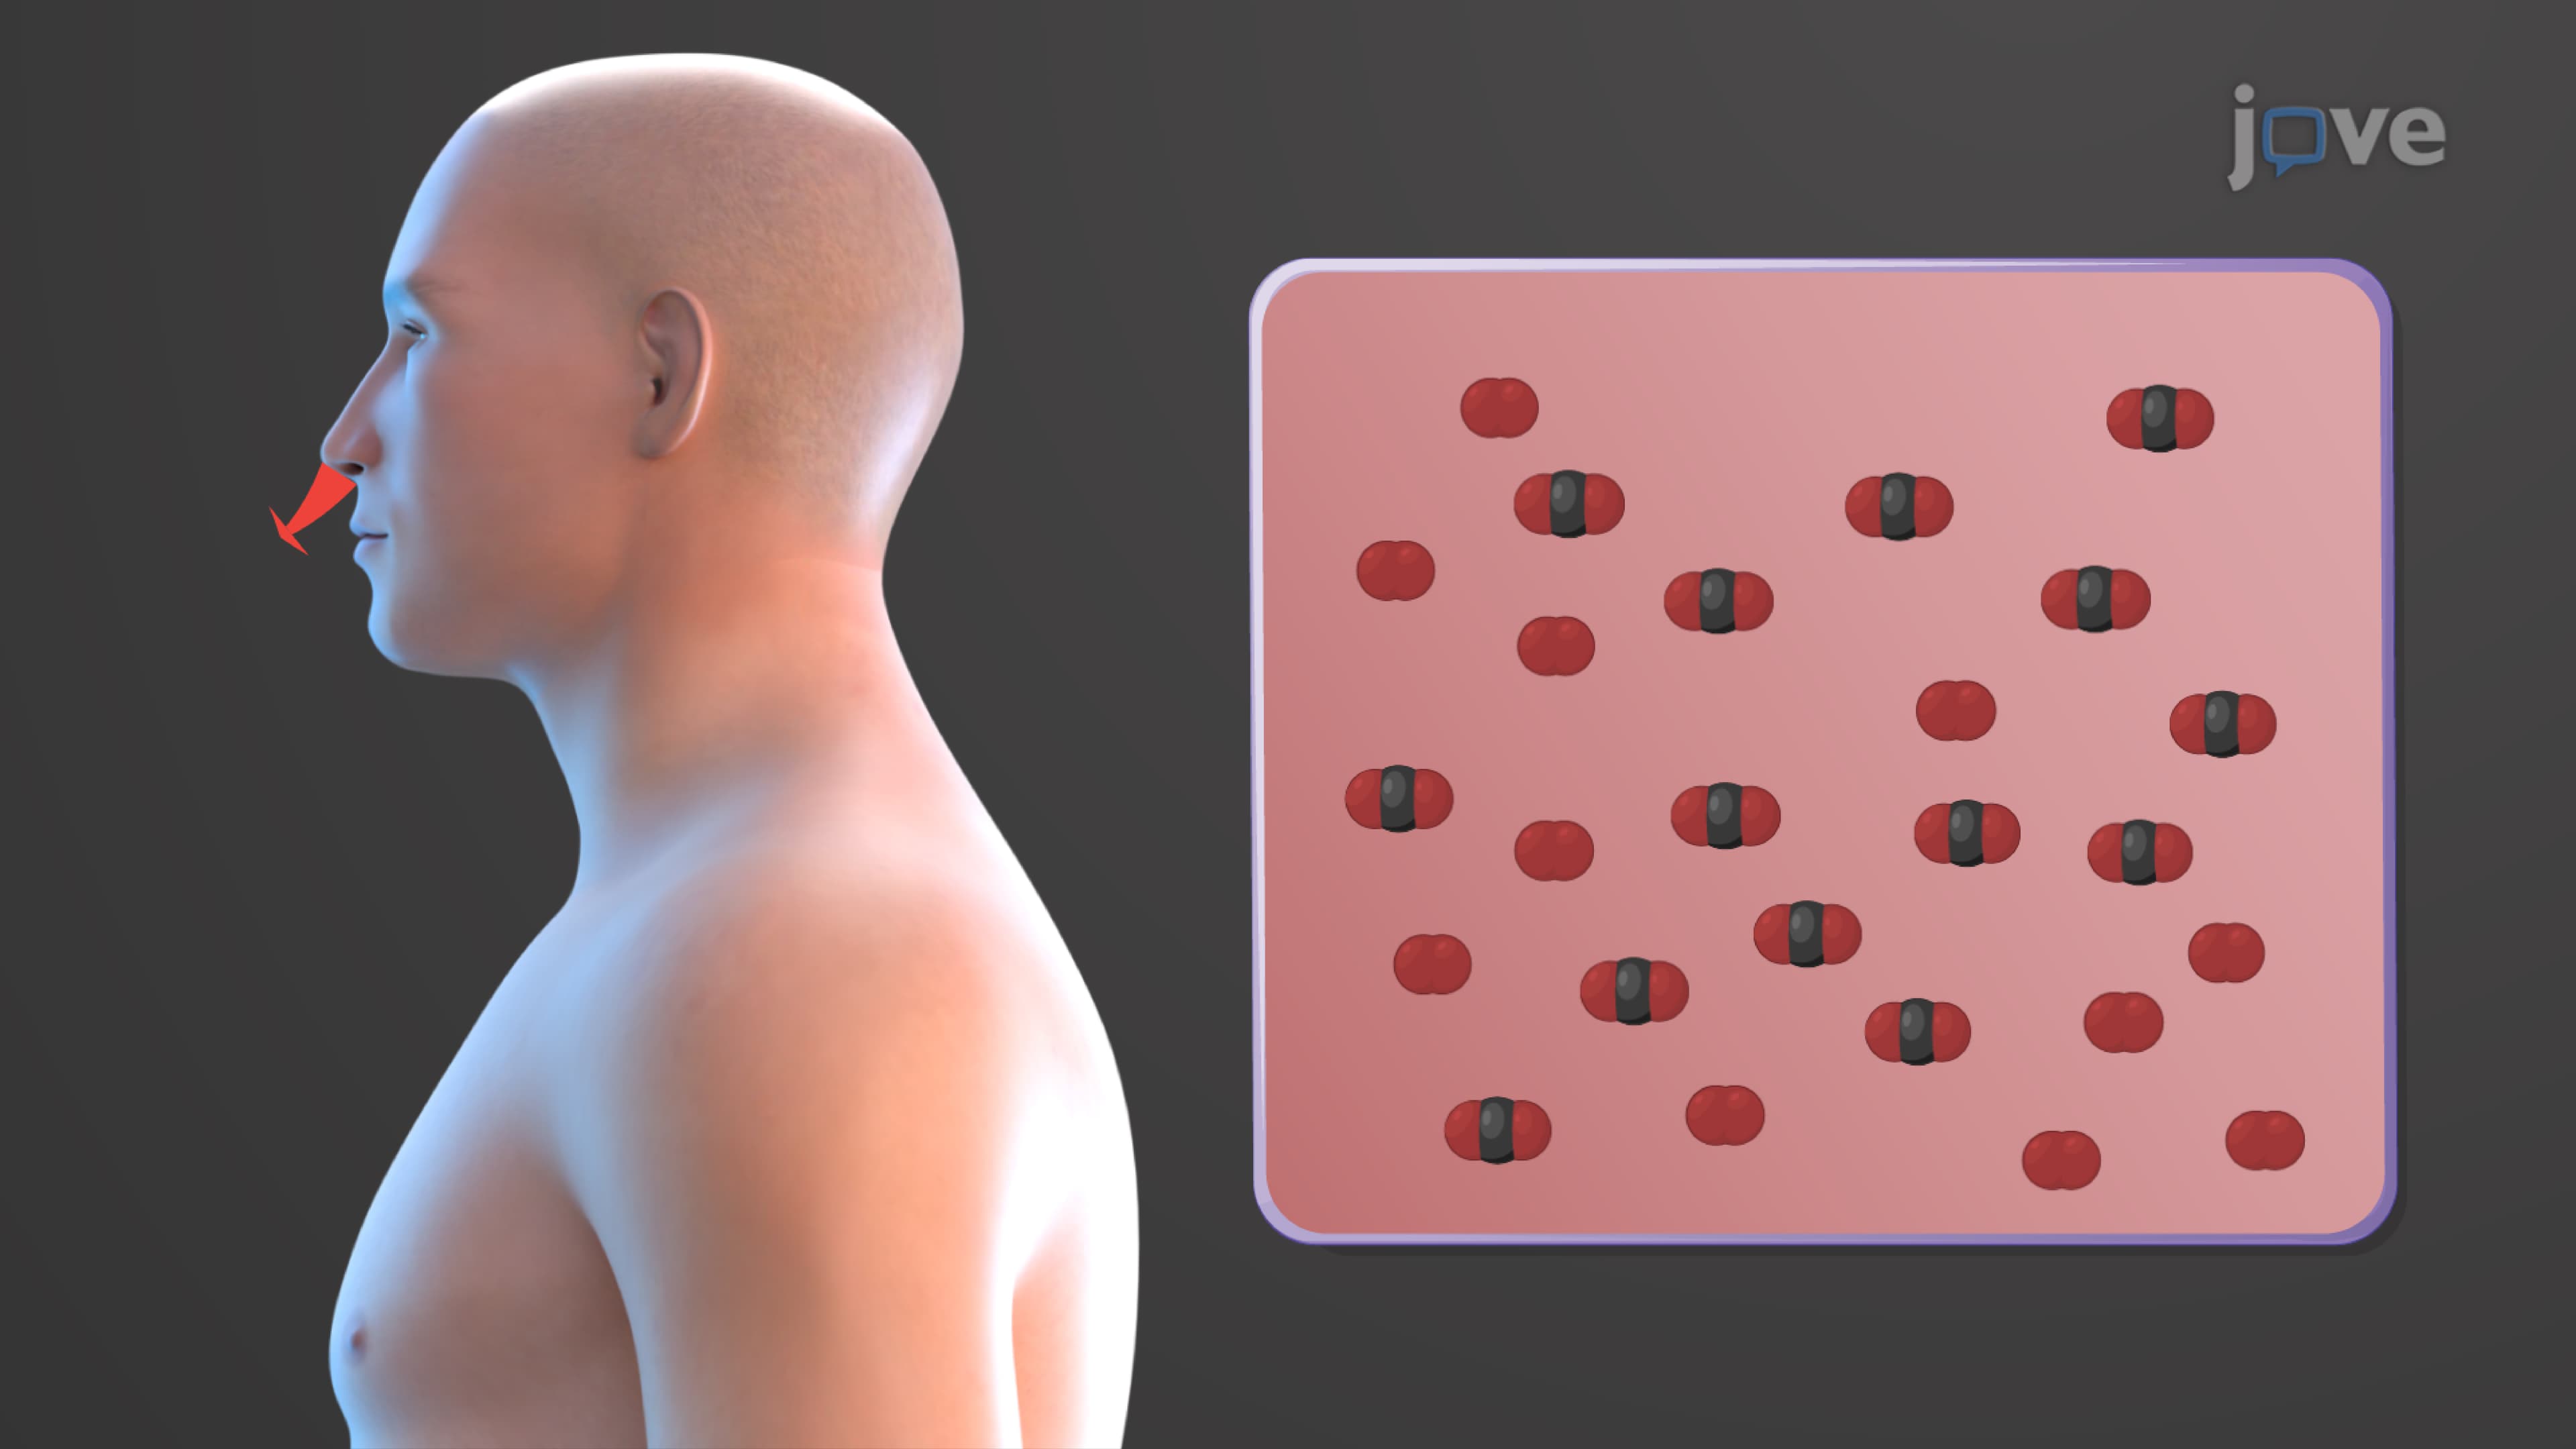
Chemical Factors Affecting Respiration Centers
CO2 has a potent influence on respiration and is strictly regulated....
 01:17
Other Factors Affecting Respiration Centers
However, the ability to hold one's breath voluntarily is not limitless. When the CO2 concentration in the blood reaches a critical...
 01:25
Hyperpnea and Hyperventilation