Related Experiment Video
Updated: Jul 6, 2025


VDJ-Seq: Deep Sequencing Analysis of Rearranged Immunoglobulin Heavy Chain Gene to Reveal Clonal Evolution Patterns of B Cell Lymphoma
Published on: December 28, 2015
A rare case of fluid overload-associated large B-cell lymphoma and antigen loss at relapse
Xue Yan1, Bin Chen2, Hongxia Jing1
1Department of Hematology, The Affiliated Jiangning Hospital With Nanjing Medical University, Hushan Road, Jiangning District, Nanjing, 211100, Jiangsu, China.

Abstract:
Fluid overload-associated large B-cell lymphoma (FO-LBCL) is a new addition to the list of large B-cell lymphomas in the 5th edition of the World Health Organization Classification of Haematolymphoid Tumours (WHO-HAEM5). This report presents an unusual case of FO-LBCL with partial B cell antigen loss at relapse and reviews the characteristics, treatment, and prognosis of these patients to enhance our understanding of this disease. Immunophenotyping was performed through immunohistochemistry and flow cytometry. Immunoglobulin gene rearrangements were analyzed using BIOMED-2 multiplex primers. MYC, BCL2, and BCL6 gene rearrangements were detected by fluorescent in situ hybridization (FISH). Cell-free DNA (cfDNA) from pleural effusion and peripheral blood was subjected to somatic mutation evaluation using next-generation sequencing (NGS). In 2020, the patient was initially diagnosed with tuberculous pleurisy and received anti-tuberculous drugs. Subsequent testing of the pleural effusion cell block revealed that the large cells to be positive for CD10, CD20, CD79a, PAX5, MUM1, Bcl-2, Bcl-6, and c-myc and negative for CD3, CD30, Cyclin D1, and HHV8. In situ hybridization for Epstein-Barr virus (EBV)-associated mRNA (EBER-ISH) was negative. Additionally, a clonal rearrangement of immunoglobulin heavy locus (IGH) FR2-JH was detected; the results of MYC, BCL2, and BCL6 gene rearrangements were all negative. Following pleural drainage treatment, the patient achieved symptom remission and was diagnosed with large B-cell lymphoma (HHV8-unrelated PEL-like lymphoma). In 2022, the patient was readmitted due to the recurrence of pleural effusion. The pleural effusion cell block revealed a distinct immunophenotype compared to previous findings, positivity for PAX5 and negativity for CD20, CD10, CD3, CD5, CD30, CD38, CD138, CD79a, MUM1, Bcl-2, Bcl-6, Cyclin D1, c-myc, ALK, and HHV8. Identical IGH FR2-JH clonal rearrangement suggested the recurrence of the original clone. CfDNA analysis showed mutations in CD79B, MYD88, CCND3, and DTX1. The patient was ultimately diagnosed with FO-LBCL based on the WHO-HAEM5 classification. Diagnosis of FO-LBCL should be differentiated from primary effusion lymphoma (PEL). The features of this case align with the description of "FO-LBCL" in WHO-HAEM5 and "HHV8 and EBV-negative primary effusion-based lymphoma" in International Consensus Classification (ICC). FO-LBCL patients generally have a more favorable prognosis compared to PEL. In this case, the patient exhibited a favorable prognosis for over 22 months without additional treatment apart from pleural drainage.

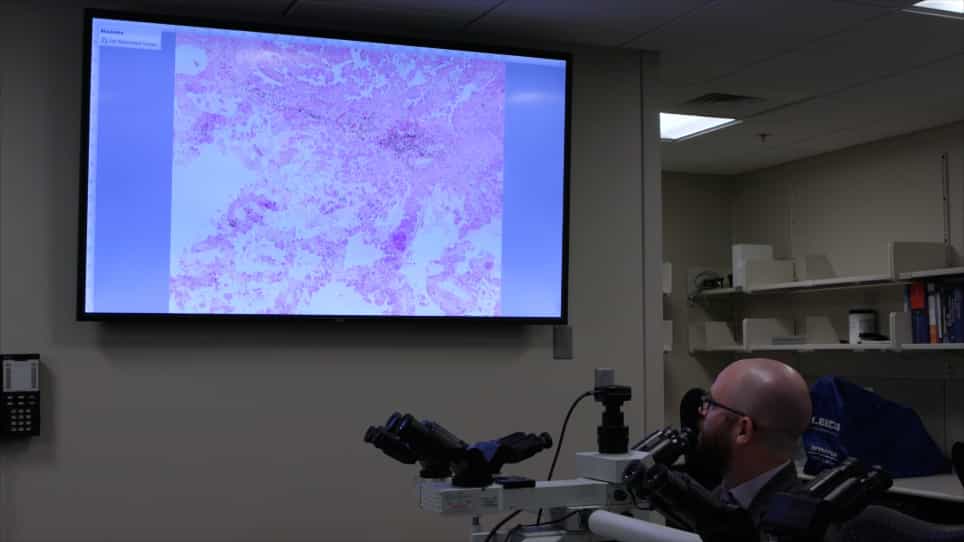
Related Concept Videos
 01:24
B Cell Activation and Differentiation
When naive B cells encounter a specific antigen that can bind to the B cell receptor (BCR) on their surface, they undergo sensitization to respond to the antigen's presence. Sensitization begins with...
 01:23
Cells of the Adaptive Immune Response
 01:20
Special Features of Adaptive Immunity
The primary cell types involved in adaptive immunity are T cells and B cells. Each type has a unique role in defending the body against pathogens. T cells are responsible for cell-mediated immunity. They identify and eliminate infected cells directly,...