Related Experiment Video
Updated: Jul 6, 2025
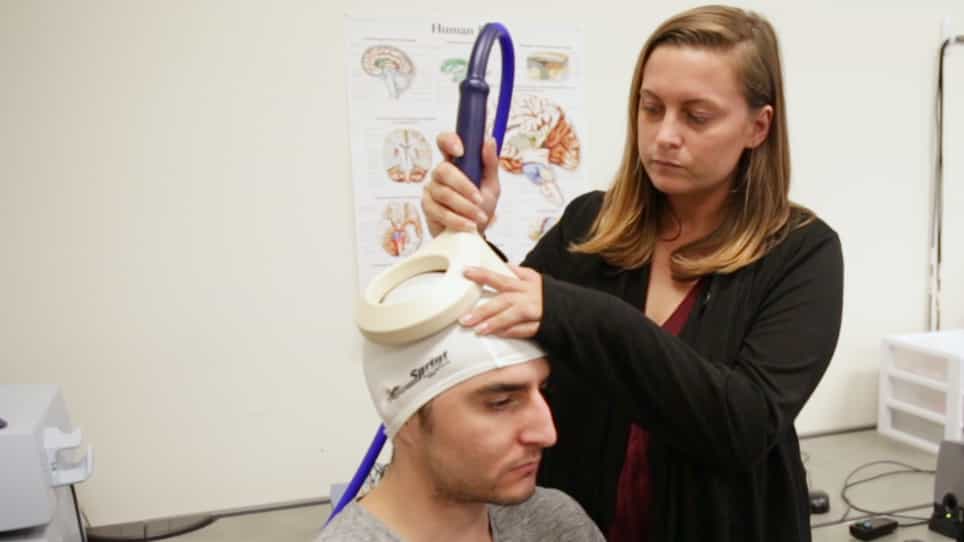

Continuous Theta Burst Stimulation of the Posterior Medial Frontal Cortex to Experimentally Reduce Ideological Threat Responses
Published on: September 28, 2018
A pilot, randomized clinical trial: Left dorsolateral prefrontal cortex intermittent theta burst stimulation improves
Claudia B Padula1,2, Daniel M McCalley1,2, Lea-Tereza Tenekedjieva1,2
1Sierra Pacific Mental Illness Research Education and Clinical Center (MIRECC), Veterans Affairs Palo Alto Healthcare System, Palo Alto, California, USA.

Background:
Transcranial magnetic stimulation (TMS) offers a promising treatment avenue to modulate brain function in alcohol use disorder (AUD). To the best of our knowledge, this pilot study is the first randomized, double-blind, sham-controlled trial to deliver intermittent theta burst stimulation to the left dorsolateral prefrontal cortex (DLPFC) among US veterans with AUD. We hypothesized that 20 sessions of real TMS are tolerable and feasible. As a secondary line of inquiry, we hypothesized that, relative to sham TMS, individuals receiving real TMS would experience greater reductions in 6-month relapse rates, anhedonia, and alcohol cue-reactivity.
Methods:
Veterans (n = 17, one woman) were enrolled in a double-blind, sham-controlled trial (2-3 sessions/day; 7-10 days; 600 pulses/session; 20 sessions). Pre- and posttreatment assessments included responses to self-report questionnaires and functional magnetic resonance imaging measures of alcohol cue-reactivity. Alcohol consumption was assessed for 6 months. Linear mixed-effects models were constructed to predict posttreatment craving, mood, and cue-reactivity.
Results:
Individuals who received active iTBS (n = 8) were less likely to relapse within 3 months after treatment than the sham-treated group (n = 9) (OR = 12.0). Greater reductions in anhedonia were observed following active iTBS (Cohen's d = -0.59), relative to sham (d = -0.25). Alcohol cue-reactivity was reduced following active iTBS and increased following sham within the left insula (d = -0.19 vs. 0.51), left thalamus (d = -0.28 vs. 0.77), right insula (d = 0.18 vs. 0.52), and right thalamus (d = -0.06 vs. 0.62).
Conclusions:
Relative to sham, we demonstrate that 20 sessions of real left DLPFC iTBS reduced the likelihood of relapse for at least 3 months. The potential utility of this approach is underscored by observed decreases in anhedonia and alcohol cue-reactivity-strong predictors of relapse among veterans. These initial data offer a valuable set of effect sizes to inform future clinical trials in this patient population.
More Related Videos
 08:54
Randomized, Triple-Blind, and Parallel-Controlled Trial of Transcranial Direct Current Stimulation for Cognitive Rehabilitation after Stroke
Published on: June 6, 2025
 08:20
Simultaneous Application of Transcranial Direct Current Stimulation during Virtual Reality Exposure
Published on: January 18, 2021