Related Experiment Video
Updated: Jul 5, 2025


Improved Renal Denervation Mitigated Hypertension Induced by Angiotensin II Infusion
Published on: May 26, 2022
Projected Impact of Nonpharmacologic Management of Stage 1 Hypertension Among Lower-Risk US Adults
Kendra D Sims1,2, Pengxiao Carol Wei1, Joanne M Penko1
1Department of Epidemiology and Biostatistics, University of California San Francisco, San Francisco, California.

Insights
Implementing lifestyle changes for stage 1 hypertension can prevent cardiovascular disease (CVD) events and reduce healthcare costs. Widespread adoption of nonpharmacologic therapies is crucial for substantial public health benefits.
Area of Science:
- Cardiovascular Medicine
- Public Health
- Health Economics
Background:
- The 2017 ACC/AHA guidelines reclassified 31 million US adults with stage 1 hypertension, recommending behavioral changes for low-risk individuals.
- The potential impact of evidence-based lifestyle interventions on cardiovascular disease (CVD) reduction and healthcare costs remains unquantified.
Approach:
- A simulation using the CVD Policy Model assessed 10-year CVD outcomes and costs in US adults aged 35-64 with low-risk stage 1 systolic hypertension (SBP 130-139 mmHg).
- Interventions focused on systolic blood pressure (SBP) control through behavior modification, utilizing data from NHANES and published meta-analyses.
- The model evaluated the impact of healthcare utilization and adherence to nonpharmacologic therapies on CVD event prevention.
Key Points:
- Controlling SBP to <130 mmHg in the target population (8.8 million adults) could prevent 26,100 CVD events, 2,900 deaths, and save $1.6 billion over 10 years.
- The DASH diet could prevent 16,000 CVD events in men and 12,000 in women annually; other nonpharmacologic interventions could avert 3,700-19,500 events.
- Only 61% of the target population regularly utilized healthcare for recommended counseling, limiting intervention effectiveness.
Conclusions:
- Substantial cardiovascular health benefits and cost savings from nonpharmacologic therapy require policies promoting widespread adoption and sustained adherence.
- Future research should quantify population-level impacts of improving food systems and local infrastructure on health behavior change.
Background:
The 2017 American College of Cardiology (ACC)/American Heart Association (AHA) guidelines newly classified 31 million US adults as having stage 1 hypertension. The ACC/AHA guidelines recommend behavioral change without pharmacology for the low-risk portion of this group. However, the nationwide reduction in cardiovascular disease (CVD) and associated healthcare expenditures achievable by evidence-based dietary improvements, sustained weight loss, adequate physical activity, and alcohol moderation remain unquantified. We estimated the effect of systolic BP (SBP) control and behavioral changes on 10-year CVD outcomes and costs.
Methods:
We used the CVD Policy Model to simulate CVD events, mortality, and healthcare costs among US adults aged 35-64. We simulated interventions on a target population, identified from the 2015-2018 National Health and Nutrition Examination Survey, with low-risk stage 1 systolic hypertension: defined as untreated SBP 130-139 mmHg and diastolic BP <90 mmHg; no history of CVD, diabetes, or chronic kidney disease; and low 10-year risk of CVD. We used published meta-analyses and trials to estimate the effects of behavior modification on SBP. We assessed the extent to which intermittent healthcare utilization or partial uptake of nonpharmacologic therapy would decrease CVD events prevented.
Results:
Controlling SBP to <130 mmHg among the estimated 8.8 million U.S. adults (51% women) in the target population could prevent 26,100 CVD events, avoid 2,900 deaths, and save $1.6 billion in healthcare costs over 10 years. The Dietary Approaches to Stop Hypertension (DASH) diet could prevent 16,000 CVD events among men and 12,000 among women over a decade. Other nonpharmacologic interventions could avert between 3,700 and 19,500 CVD events. However, only 5.5 million (61%) of the target population regularly utilized healthcare where recommended clinician counseling could occur.
Conclusions:
As only two-thirds of U.S. adults with Stage 1 hypertension regularly receive medical care, substantial benefits to cardiovascular health and associated costs may only stem from policies that promote widespread adoption and sustained adherence of nonpharmacologic therapy. Future work should quantify the population-level costs, benefits, and efficacy of improving the food system and local infrastructure on health behavior change.


Related Concept Videos
 01:18
Hypertension and Regulation of Blood Pressure
 01:28
Factors affecting Blood pressure
Physiological Factors:
 01:30
Alterations in Blood Pressure
Hypertension (High blood pressure)
Hypertension occurs when blood pressure readings consistently exceed the normal range. It is diagnosed when systolic blood pressure (the top number, indicating pressure while the heart...
 01:25
Errors occurring during blood pressure monitoring
Several factors...
 01:25
Antihypertensive Drugs: Direct Renin Inhibitors
 01:30
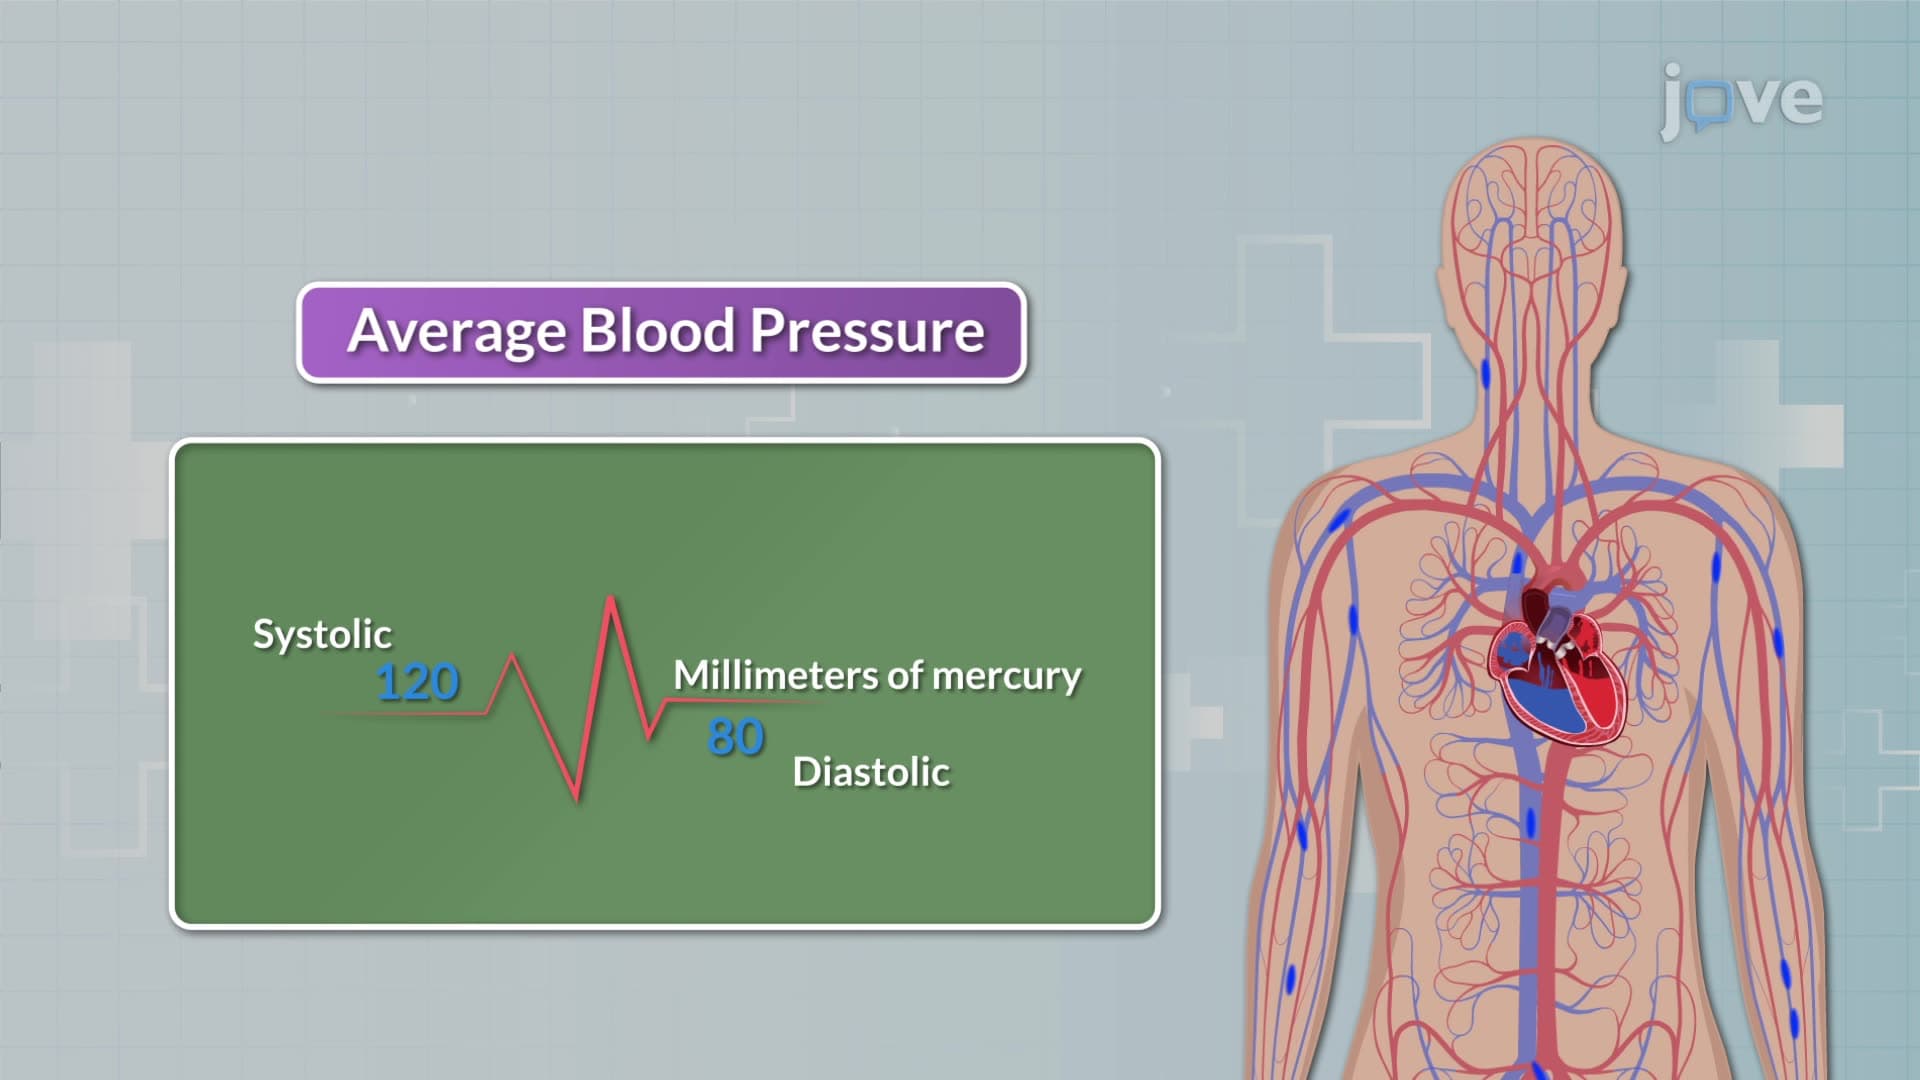
Blood Pressure
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the...