Related Experiment Video
Updated: Jul 5, 2025

Occlusion of the Great and Small Saphenous Vein Using Copolymeric Glue Based on N-Butyl Cyanoacrylate and Methacryloxy Sulfolane
Published on: December 9, 2022
Risk factors for low back pain after iliac vein stenting for non-thrombotic iliac vein lesions
Amrit Hingorani1, Enrico Ascher1, Jesse Chait2
1Division of Vascular Surgery, Department of Surgery, NYU Brooklyn and Total Vascular Care, Brooklyn, NY.

Objective:
Iliac vein stenting is an option being explored to treat chronic venous insufficiency. We have noted that our most common postoperative complication is low back pain after stent placement, which is occasionally quite severe. We wanted to investigate risk factors that are involved in this phenomenon and identify potentially modifiable factors.
Methods:
Patients who failed 3 months of conservative therapy had iliac vein interrogation performed. We limited the scope of this database to non-thrombotic iliac vein lesions treated in the office in which Wallstents were placed. Data were collected from September 2012 to August 2020 for 2308 consecutive outpatients who underwent 3747 procedures. Before August 2016, patients received pre-procedure oral valium (n = 2679) and thereafter, patients received intravenous (IV) sedation (n = 1068). A pain score, on a Likert scale ranging from 0 to 10, was assessed within 1 hour postoperatively. We analyzed the medications administered and correlated them with pain scores.
Results:
The average of all the pain scores was 0.86 (range, 0-10; standard deviation [SD], 2.00). Age had a slight inverse effect on pain scores (r = -0.12; P < .00001). Presenting signs (based upon CEAP) (P = .11) and body mass index (P = .88) did not have a significant effect on pain scores. Average pain score for females (0.96) was slightly higher than for males (0.70), with P < .0001. Average pain score for procedures on the right side (0.67) was lower than for procedures on the left side (1.01), with P < .0001. Average pain score for patients who received IV sedation (mean, 0.68; SD, 1.58) was lower than that for those who did not (mean, 0.93; SD, 2.15), with P = .0004. When using a single agent, propofol was associated with the lowest pain scores (P < .0001). Toradol displayed a dose-dependent effect on pain score (P < .0001). The best combination of agents for pain control was propofol and toradol together.
Conclusions:
Overall, the vast majority of pain scores were low. Factors that were associated with lower pain scores were older age, male sex, procedures on the right side, and IV sedation, in particular with the use of propofol. These data may help us better target patients anticipated to have high pain scores and suggest the preferential use of propofol and toradol.
Related Concept Videos
 01:15
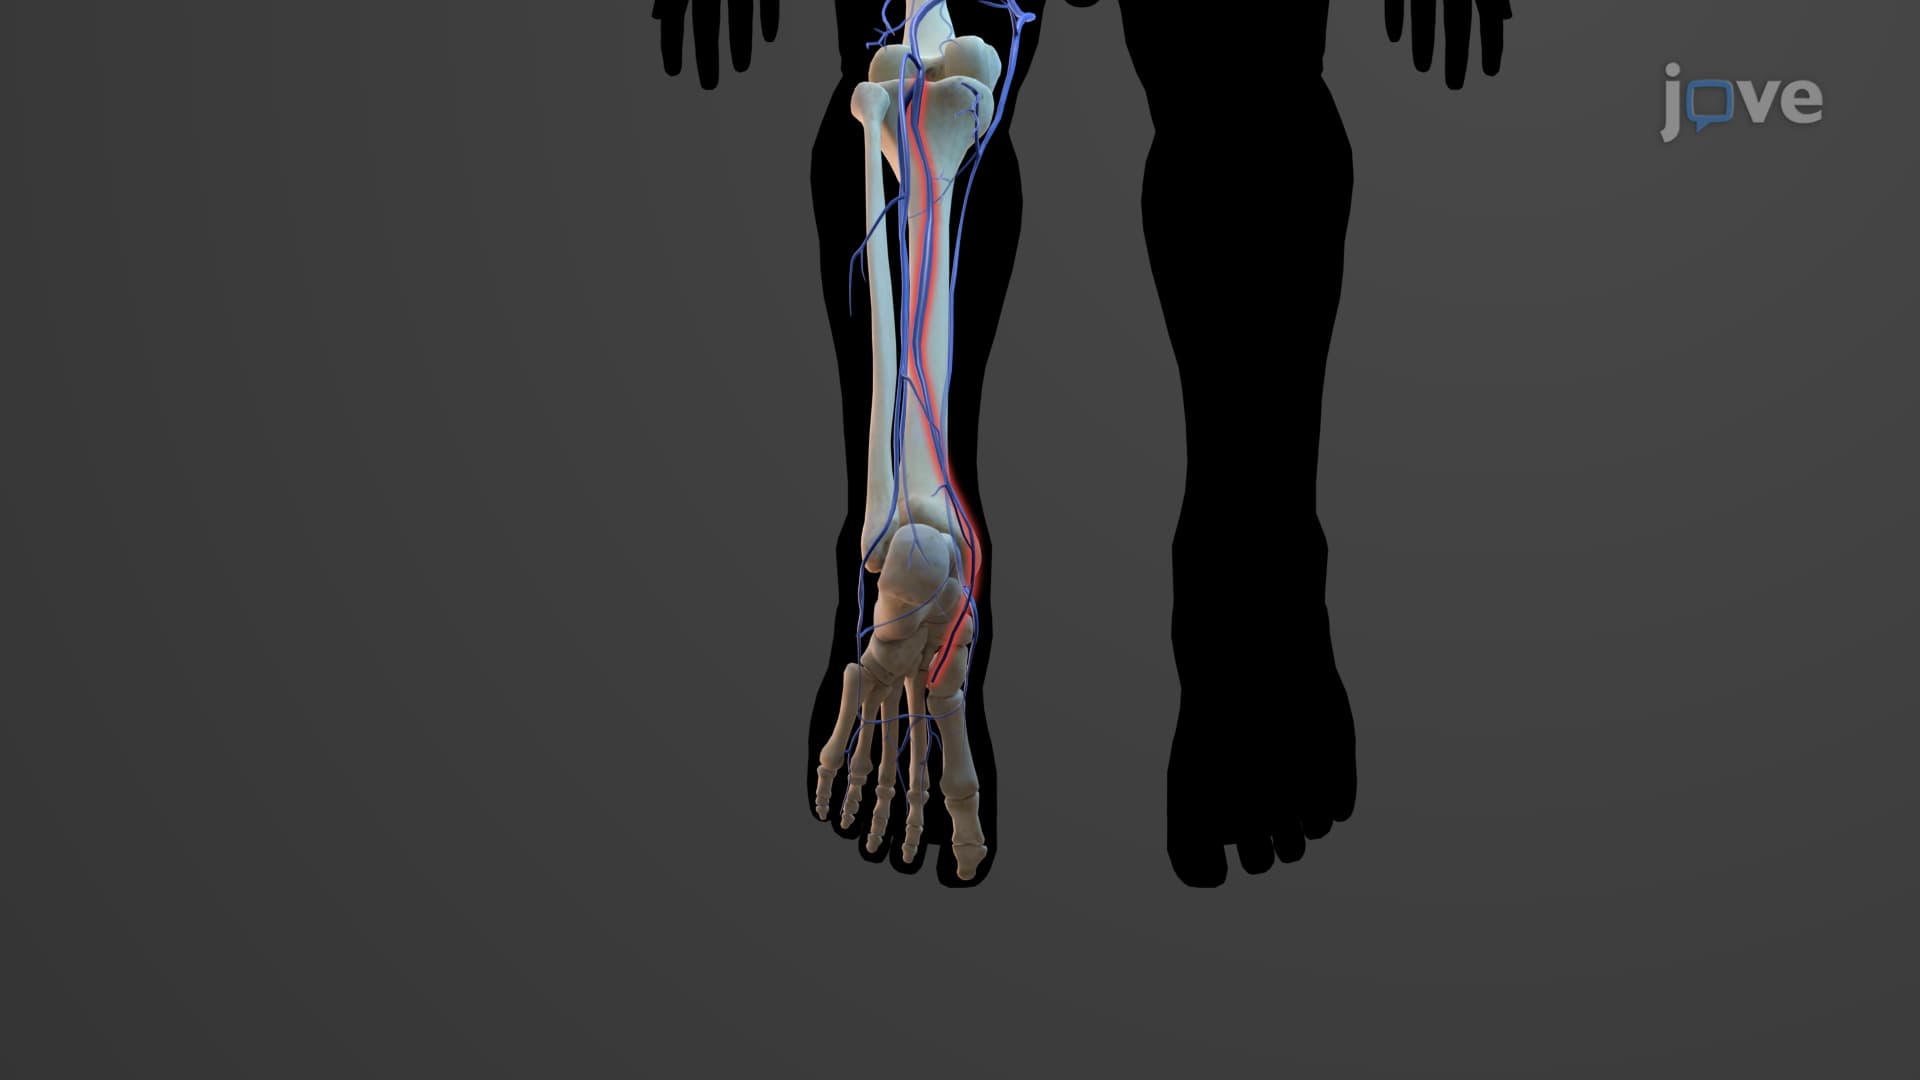
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the...
 01:18
Veins of the Abdomen and Pelvis
The inferior vena cava is fed by numerous smaller veins. The lumbar veins, for instance, drain the posterior abdominal wall, emptying both directly into the inferior vena cava and into the...
 01:19
Abdominal Regions and Quadrants
The simpler quadrants approach, which is more commonly used in medicine, subdivides the cavity with one horizontal and one vertical line that intersects at the patient's umbilicus (navel). The four...
 01:24
Esophageal Varices-I: Introduction