Related Experiment Video
Updated: Jul 5, 2025
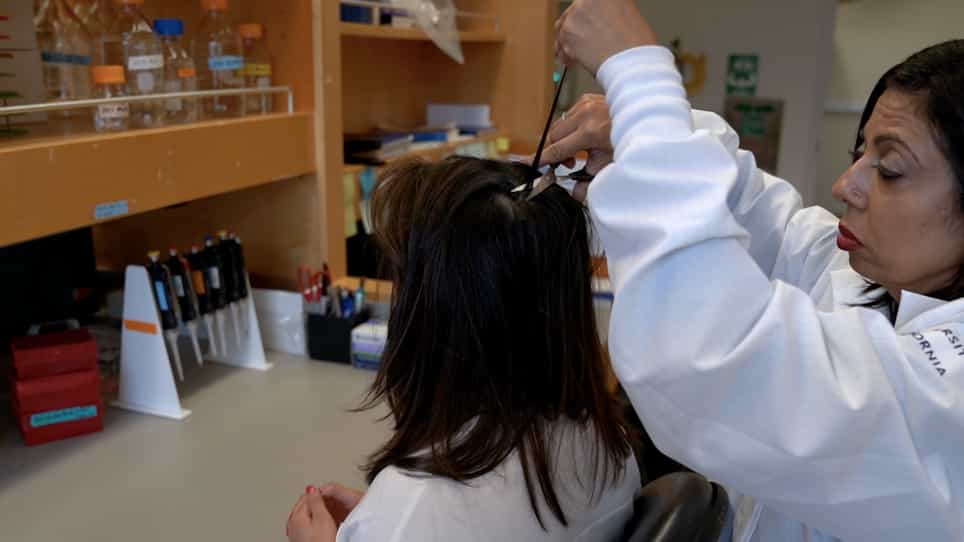

Validated LC-MS/MS Panel for Quantifying 11 Drug-Resistant TB Medications in Small Hair Samples
Published on: May 19, 2020
Prediction Models for Adverse Drug Reactions During Tuberculosis Treatment in Brazil
Felipe Ridolfi1,2, Gustavo Amorim3, Lauren S Peetluk4,5
1Division of Infectious Diseases, Department of Medicine, Vanderbilt University Medical Center, Nashville, Tennessee, USA.

Background:
Tuberculosis (TB) treatment-related adverse drug reactions (TB-ADRs) can negatively affect adherence and treatment success rates.
Methods:
We developed prediction models for TB-ADRs, considering participants with drug-susceptible pulmonary TB who initiated standard TB therapy. TB-ADRs were determined by the physician attending the participant, assessing causality to TB drugs, the affected organ system, and grade. Potential baseline predictors of TB-ADR included concomitant medication (CM) use, human immunodeficiency virus (HIV) status, glycated hemoglobin (HbA1c), age, body mass index (BMI), sex, substance use, and TB drug metabolism variables (NAT2 acetylator profiles). The models were developed through bootstrapped backward selection. Cox regression was used to evaluate TB-ADR risk.
Results:
There were 156 TB-ADRs among 102 of the 945 (11%) participants included. Most TB-ADRs were hepatic (n = 82 [53%]), of moderate severity (grade 2; n = 121 [78%]), and occurred in NAT2 slow acetylators (n = 62 [61%]). The main prediction model included CM use, HbA1c, alcohol use, HIV seropositivity, BMI, and age, with robust performance (c-statistic = 0.79 [95% confidence interval {CI}, .74-.83) and fit (optimism-corrected slope and intercept of -0.09 and 0.94, respectively). An alternative model replacing BMI with NAT2 had similar performance. HIV seropositivity (hazard ratio [HR], 2.68 [95% CI, 1.75-4.09]) and CM use (HR, 5.26 [95% CI, 2.63-10.52]) increased TB-ADR risk.
Conclusions:
The models, with clinical variables and with NAT2, were highly predictive of TB-ADRs.


Related Concept Videos
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:19
Pharmacovigilance
This process, termed pharmacovigilance, aims to detect, evaluate, and minimize harmful effects related to medication use. The data collection for pharmacovigilance depends on spontaneous reporting systems, where healthcare professionals or patients voluntarily report suspected ADRs.
In some cases, there...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:26
Pharmacokinetic Models: Comparison and Selection Criterion
Physiological models take a detailed approach by considering specific molecular processes. They can predict drug distribution, metabolism, and elimination changes, providing a comprehensive understanding of how drugs interact with the body.