Related Experiment Video
Updated: Jul 5, 2025
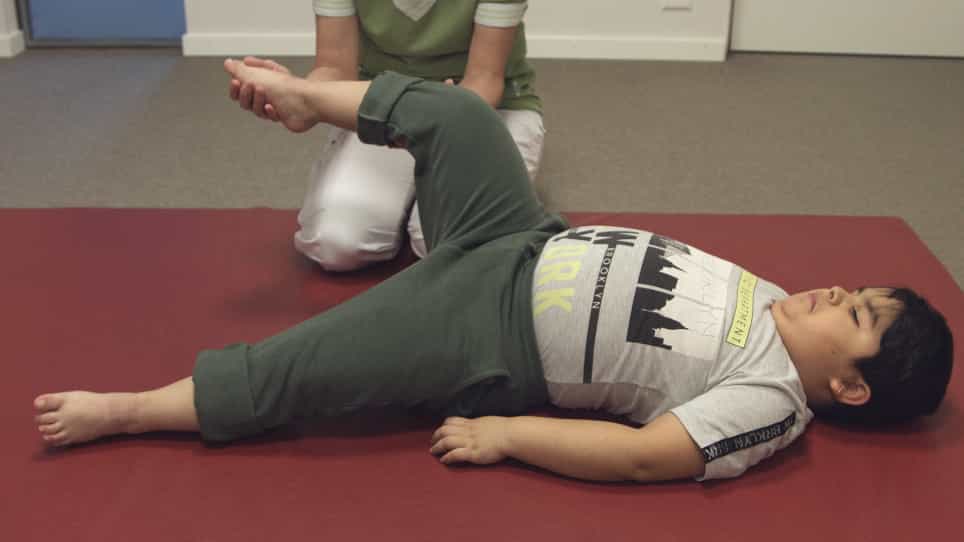

Measurements of Motor Function and Other Clinical Outcome Parameters in Ambulant Children with Duchenne Muscular Dystrophy
Published on: January 12, 2019
Novel implementation of cardiac magnetic resonance first-pass perfusion imaging for semi-quantitatively evaluating
Linjun Xie1, Xiaotang Cai2, Yingkun Guo1
1Department of Radiology, Key Laboratory of Obstetric & Gynecologic and Pediatric Diseases and Birth Defects of Ministry of Education, West China Second University Hospital, Sichuan University, Chengdu, Sichuan 610041, China.

Insights
Children with Duchenne muscular dystrophy (DMD) may experience myocardial microcirculation dysfunction, detectable before late gadolinium enhancement (LGE) using cardiac magnetic resonance (CMR) perfusion imaging. This dysfunction correlates with coronary artery supply and injury extent.
Area of Science:
- Cardiology
- Pediatric Cardiology
- Cardiovascular Imaging
Background:
- Duchenne muscular dystrophy (DMD) is a genetic disorder affecting muscle tissue, including the heart.
- Cardiac involvement is a major cause of morbidity and mortality in DMD patients.
- Early detection of cardiac dysfunction is crucial for managing DMD.
Purpose of the Study:
- To assess myocardial microcirculation dysfunction in pediatric patients with DMD using cardiac magnetic resonance (CMR) first-pass perfusion imaging.
- To investigate if microvascular dysfunction precedes late gadolinium enhancement (LGE) in DMD.
- To explore the correlation between myocardial microcirculation parameters and cardiac function/LGE extent.
Main Methods:
- Enrolled 67 children with DMD and 15 controls undergoing contrast-enhanced CMR first-pass perfusion imaging.
- Acquired CMR first-pass perfusion and late gadolinium enhancement (LGE) sequences.
- Analyzed global, regional, and coronary artery distribution area perfusion indexes (PI), upslope, maximum signal intensity (MaxSI), time to maximum signal intensity (TTM), and baseline SI.
Main Results:
- Patients with LGE+ showed significantly lower global and apical-ventricular MaxSI compared to controls.
- LGE+ group segments (LAD, LCX, RCA) had lower upslope and MaxSI than controls.
- LGE- group LAD segments had lower MaxSI, and LCX segments had lower PI and upslope than controls.
- Upslope, MaxSI, and TTM correlated with conventional cardiac function and LGE extent.
Conclusions:
- Pediatric patients with DMD may exhibit microvascular dysfunction, potentially appearing before LGE.
- Myocardial microcirculation dysfunction in DMD correlates with coronary artery blood supply and LGE extent.
- Analyzing perfusion parameters by coronary artery distribution area can detect early-stage myocardial microvascular dysfunction in DMD patients, even before LGE.
Objectives:
The current study aimed to assess myocardial microcirculation dysfunction via cardiac magnetic resonance (CMR) first-pass perfusion imaging in children with Duchenne muscular dystrophy (DMD).
Methods:
In total, 67 children with DMD and 15 controls who underwent contrast-enhanced CMR first-pass perfusion imaging were enrolled in this study. CMR first-pass perfusion and late gadolinium enhancement (LGE) sequences were acquired. Further, the global, regional, and coronary artery distribution area perfusion indexes (PI), upslope (%BL), maximum signal intensity (MaxSI), time to maximum signal intensity (TTM), and baseline SI were analysed. The perfusion parameters of the LGE positive (+), LGE negative (-), and control groups were compared. Pearson correlation analysis was performed to assess the association between myocardial microcirculation and conventional cardiac function and LGE parameters.
Results:
The LGE+ group had a significantly lower global and apical-ventricular MaxSI than the control group (all P < .05). The left anterior descending arterial (LAD), left circumflex coronary arterial (LCX), and right coronary arterial (RCA) segments of the LGE+ group had a lower upslope and MaxSI than those of the control group (all P < .05). The LAD segments of the LGE- group had a lower MaxSI than those of the control group (41.10 ± 11.08 vs 46.36 ± 13.04; P < .001). The LCX segments of the LGE- group had a lower PI and upslope than those of the control group (11.05 ± 2.84 vs 12.46 ± 2.82; P = .001; 59.31 ± 26.76 vs 68.57 ± 29.99; P = .002). Based on the correlation analysis, the upslope, MaxSI, and TTM were correlated with conventional cardiac function and LGE extent.
Conclusions:
Paediatric patients with DMD may present with microvascular dysfunction. This condition may appear before LGE and may be correlated with coronary artery blood supply and LGE extent.
Advances In Knowledge:
First-pass perfusion parameters may reveal the status of myocardial microcirculation and reflect the degree of myocardial injury at an earlier time in DMD patients. Perfusion parameters should be analysed not only via global or base, middle, and apical segments but also according to coronary artery distribution area, which may detect myocardial microvascular dysfunction at an earlier stage, in DMD patients with LGE-.
More Related Videos
 08:13
In Vivo Quantitative Assessment of Myocardial Structure, Function, Perfusion and Viability Using Cardiac Micro-computed Tomography
Published on: February 16, 2016
 05:07
Author Spotlight: Improved Localization and Monitoring of Coronary Flow Reserve Using Modified PLAX View in Mice
Published on: August 25, 2023
