Related Experiment Video
Updated: Jun 27, 2026

Performing Behavioral Tasks in Subjects with Intracranial Electrodes
Published on: October 2, 2014
The value of additional electrodes when stereo-electroencephalography is inconclusive
Adeel Ilyas1,2,3, Laura Vilella3,4, Carlos E Restrepo1,2,3
1Department of Neurological Surgery, University of Alabama at Birmingham, Birmingham, Alabama, USA.

Objective:
Stereo-electroencephalography (SEEG) is the preferred method for intracranial localization of the seizure-onset zone (SOZ) in drug-resistant focal epilepsy. Occasionally SEEG evaluation fails to confirm the pre-implantation hypothesis. This leads to a decision tree regarding whether the addition of SEEG electrodes (two-step SEEG - 2sSEEG) or placement of subdural electrodes (SDEs) after SEEG (SEEG2SDE) would help. There is a dearth of literature encompassing this scenario, and here we aimed to characterize outcomes following unplanned two-step intracranial EEG (iEEG).
Methods:
All 225 adult SEEG cases over 8 years at our institution were reviewed to extract patient data and outcomes following a two-step evaluation. Three raters independently quantified benefits of additional intracranial electrodes. The relationship between two-step iEEG benefit and clinical outcome was then analyzed.
Results:
Fourteen patients underwent 2sSEEG and nine underwent SEEG2SDE. In the former cohort, the second SEEG procedure was performed for these reasons-precise localization of the SOZ (36%); defining margins of eloquent cortex (21%); and broadening coverage in the setting of non-localizable seizure onsets (43% of cases). Sixty-four percent of 2sSEEG cases were consistently deemed beneficial (Light's κ = 0.80). 2sSEEG performed for the first two indications was much more beneficial than when onsets were not localizable (100% vs 17%, p = .02). In the SEEG2SDE cohort, SDEs identified the SOZ and enabled delineation of margins relative to eloquent cortex in all cases.
Significance:
The two-step iEEG is useful if the initial evaluation is broadly concordant with the original electroclinical hypothesis, where it can clarify onset zones or delineate safe surgical margins; however, it provides minimal benefit when the implantation hypothesis is erroneous, and we recommend that 2sSEEG not be generally utilized in such cases. SDE implantation after SEEG minimizes the need for SDEs and is helpful in delineating surgical boundaries relative to ictal-onset zones and eloquent cortex.
More Related Videos
 05:54
Stereo-Electro-Encephalo-Graphy SEEG With Robotic Assistance in the Presurgical Evaluation of Medical Refractory Epilepsy: A Technical Note
Published on: June 13, 2016
 04:50
Operative Technique and Nuances for the Stereoelectroencephalographic SEEG Methodology Utilizing a Robotic Stereotactic Guidance System
Published on: June 9, 2023
Related Concept Videos
 01:13
Finding Electric Potential From Electric Field
 01:15
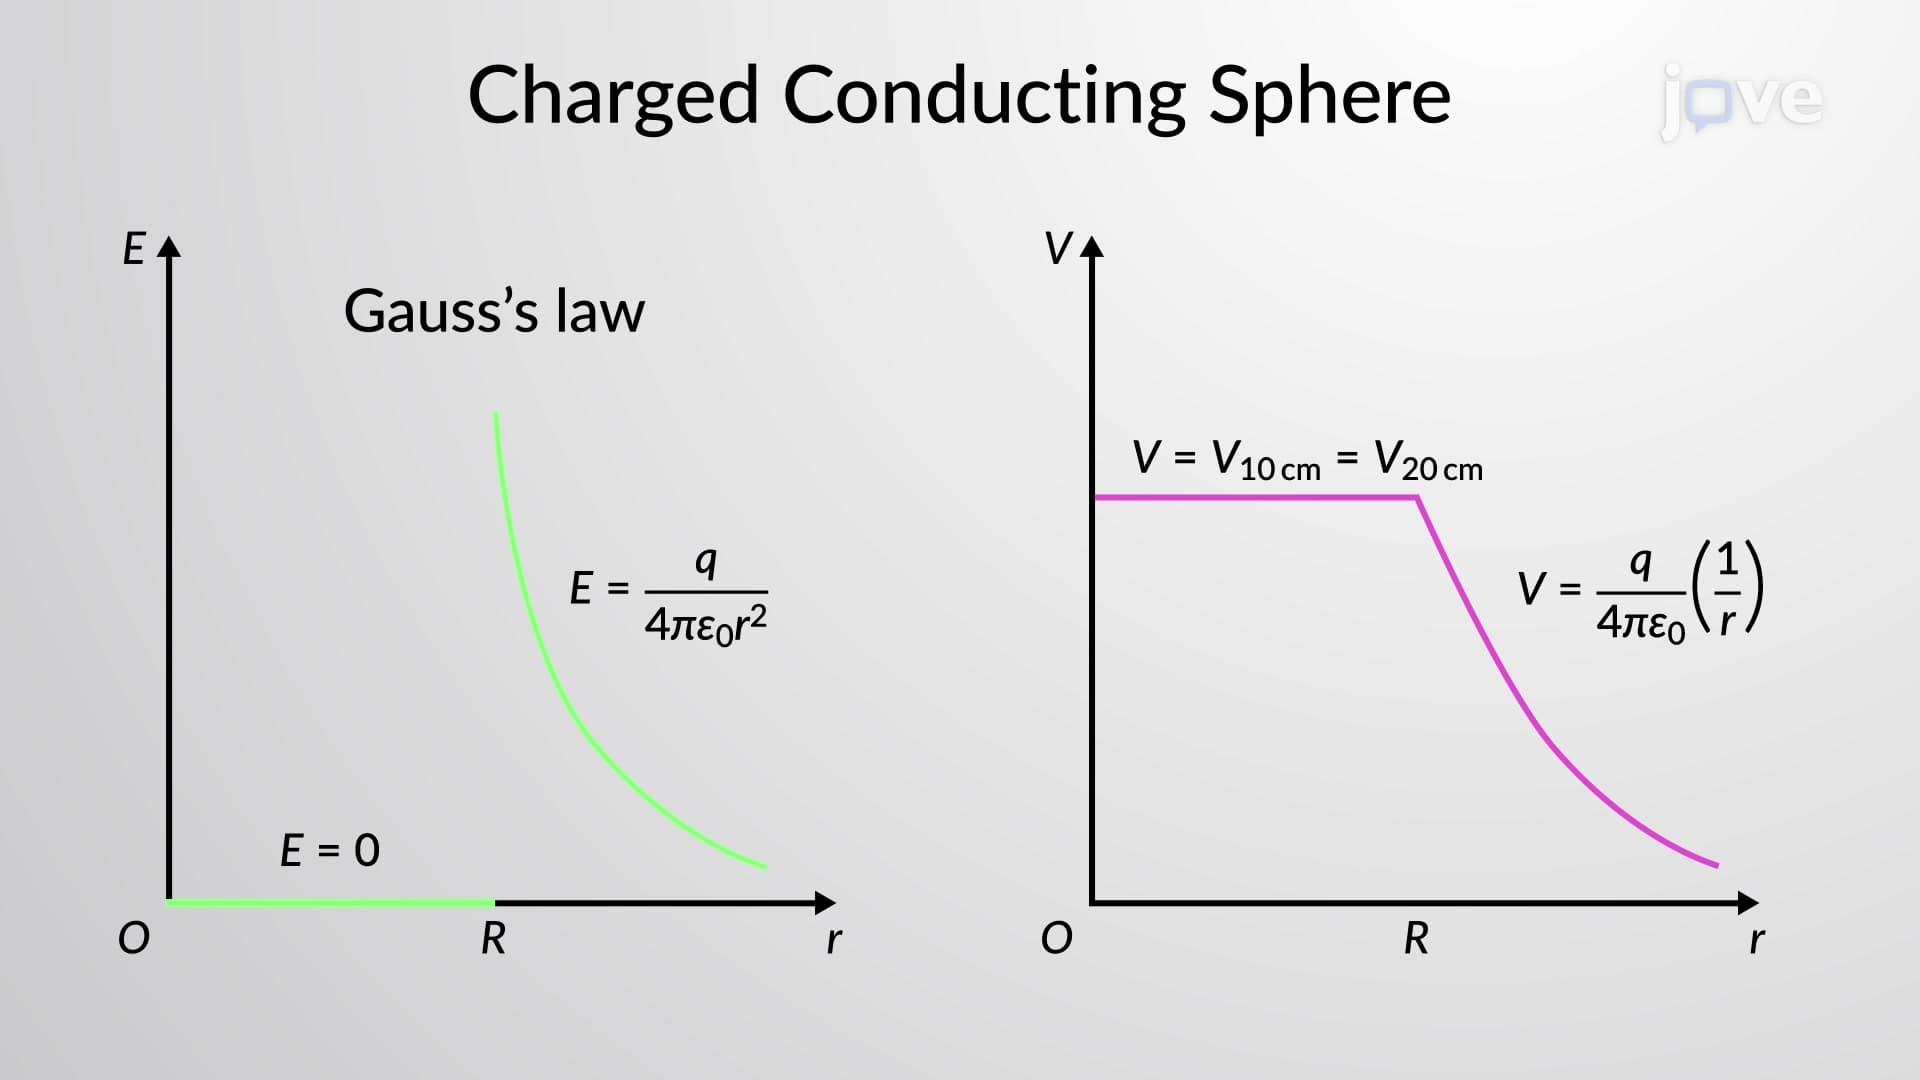
Calculations of Electric Potential I
The ring is divided into infinitesimal small arcs such that point M is equidistant from all the arcs. Here, the cylindrical coordinate system is used to calculate the electric potential at point M. A general element of the arc between angles θ and θ + dθ is of the length Rdθ and has a charge of λRdθ.
 01:27
Calculations of Electric Potential II
Consider a...
 01:12
Determining Electric Field From Electric Potential
In general, regardless of whether the electric field is uniform, it points in the direction of decreasing potential because the force on a positive...
 01:29
Potential Due to a Polarized Object
 01:30
The Electrical Double Layer