Related Experiment Video
Updated: Jul 5, 2025
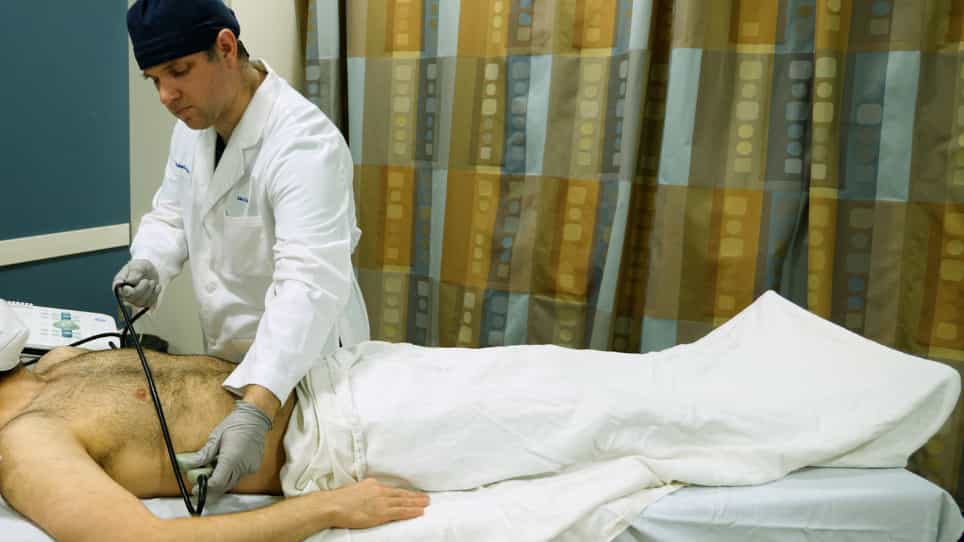

Focused Assessment with Sonography for Trauma FAST Exam: Image Acquisition
Published on: September 22, 2023
Validation of the predictive model for operative intervention after blunt abdominal trauma in children with equivocal
Abdulraouf Lamoshi1,2, Raymond Lay3, Derek Wakeman3
1Cohen Children's Medical Center, New Hyde Park, NY, USA. raofdr@gmail.com.

Insights
This study validated a predictive model for pediatric blunt abdominal trauma (BAT) surgery. Key factors like free fluid and solid organ injury accurately identify children needing surgical intervention.
Area of Science:
- Pediatric Surgery
- Trauma Management
- Radiology
Background:
- A preliminary predictive model for pediatric blunt abdominal trauma (BAT) surgery was previously developed.
- This study aimed to validate the model's predictive factors across multiple institutions.
Purpose of the Study:
- To validate a clinical and radiologic predictive model for surgical intervention in pediatric BAT patients.
- To identify key factors associated with the need for surgery in children with BAT.
Main Methods:
- Retrospective chart review of pediatric patients (under 18) with BAT from five trauma centers (2011-2020).
- Exclusion of patients with pneumoperitoneum or hemodynamic instability.
- Statistical analysis using Fisher's exact test and logistic regression to assess risk factors: abdominal wall bruising (AWB), abdominal pain/tenderness (APT), thoracolumbar fracture (TLF), free fluid (FF), and solid organ injury (SOI).
Main Results:
- 726 pediatric BAT patients were included; 8.8% required surgery.
- TLF, APT, FF, and SOI were significantly associated with surgical need (p<0.01).
- The predictive model achieved an AUC of 0.80. For motor vehicle collisions (MVC), FF, SOI, and TLF were significant predictors (AUC 0.87).
Conclusions:
- A validated clinical and radiologic prediction rule accurately identifies pediatric BAT patients requiring surgery.
- Free fluid (FF), solid organ injury (SOI), and thoracolumbar fracture (TLF) are the most critical factors predicting surgical intervention.
Background:
We recently developed a preliminary predictive model identifying clinical and radiologic factors associated with the need for surgery following blunt abdominal trauma (BAT) in children. Our aim in this study was to further validate the factors in this predictive model in a multi-institutional study.
Methods:
A retrospective chart review of pediatric patients from five pediatric trauma centers who experienced BAT between 2011 and 2020 was performed. Patients under 18 years of age who had BAT and computed tomography (CT) abdomen imaging were included. Children with evidence of pneumoperitoneum, and hemodynamic instability were excluded. Fisher's exact test was used for statistical analysis of the association between the following risk factors and need for laparotomy: abdominal wall bruising (AWB), abdominal pain/tenderness (APT), thoracolumbar fracture (TLF), presence of free fluid (FF), presence of solid organ injury (SOI). A predictive logistic regression model was then estimated employing these factors.
Findings:
Seven hundred thirty-four patients were identified in this multi-institutional dataset with BAT and abdominal CT imaging, and 726 were included. Of those, 59 underwent surgical intervention (8.8%). Univariate analysis of association between the studied factors and need for surgical management showed that the presence of TLF (p < 0.01), APT (p < 0.01), FF (p < 0.01), and SOI (p < 0.01) were significantly associated. A predictive model was created using the 5 factors resulting in an area under the curve (AUC) of 0.80. For the motor vehicle collisions (MVC) group, only FF, SOI, and TLF are significantly associated with the need for surgical intervention. The AUC for the MVC group was 0.87.
Conclusions:
A clinical and radiologic prediction rule was validated using a large multi-institutional dataset of pediatric BAT patients, demonstrating a high degree of accuracy in identifying children who underwent surgery. FF, SOI, and TLF are the most important factors associated with the need for surgical intervention.
Level Of Evidence:
Level III.
Related Concept Videos
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:18
Assessment of the Abdomen II: Percussion
Percussion
Percussion is an essential...
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...