Related Experiment Video
Updated: Jul 4, 2025
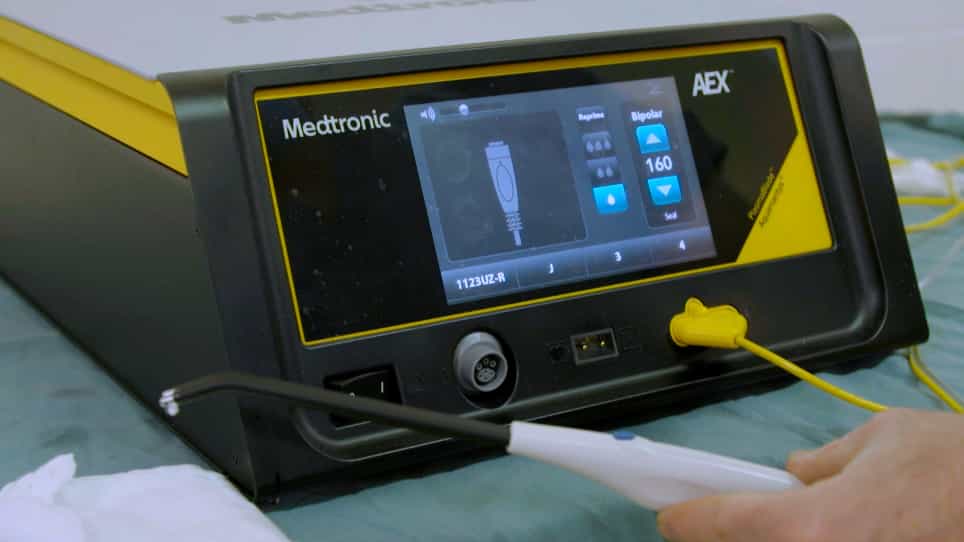
A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Use of a statewide solid organ injury procotcol to optimize triage, treatment, and transfer for pediatric abdominal
Robert A Swendiman1, Katie W Russell, Kezlyn Larsen
1From the Division of Pediatric Surgery, Department of Surgery (R.A.S., K.W.R., K.L., S.J.F.), University of Utah School of Medicine, Salt Lake City, UT; and Utah Department of Health (M.E.), Utah Pediatric Trauma Network, Salt Lake City, UT.

Background:
The Utah Pediatric Trauma Network (UPTN) is a non-competitive collaboration of all 51 hospitals in the state of Utah with the purpose of improving pediatric trauma care. Created in 2019, UPTN has implemented evidence-based guidelines based on hospital resources and capabilities with quarterly review of data collected in a network-specific database. A blunt solid organ injury (SOI) protocol was developed to optimize treatment of these injuries statewide. The purpose of this study was to review the effectiveness of the SOI guideline.
Methods:
The UPTN REDCap® database was retrospectively reviewed from 2021 through 2022. We compared admissions from the Level 1 pediatric trauma center (PED1) to non-pediatric hospitals (non-PED1) of children with low-grade (I-II) and high-grade (III-V) SOIs.
Results:
In 2 years, 172 patients were treated for blunt SOI, with or without concomitant injuries. There were 48 (28%) low-grade and 124 (72%) high-grade SOIs. 33 (69%) patients were triaged with low-grade SOI injuries at a non-PED1 center, and 17 (35%) were transferred to the PED1 hospital. Most had multiple injuries, but 7 (44%) were isolated, and none required a transfusion or any procedure/operation at either hospital. Of the 124 patients with high-grade injuries, 41 (33%) primarily presented to the PED1 center, and 44 (35%) were transferred there. Of these, 2 required a splenectomy and none required angiography. Thirty-nine children were treated at non-PED1 centers without transfer, and 4 required splenectomy and 6 underwent angiography/embolization procedures. No patient with an isolated SOI died.
Conclusion:
Implementation of SOI guidelines across UPTN successfully allowed non-pediatric hospitals to safely admit children with low-grade isolated SOI, keeping families closer to home, while standardizing pediatric triage for blunt abdominal trauma in the state.
Level Of Evidence:
Therapeutic/Care Management; Level IV.


