Surgical treatment for severe pediatric tracheobronchomalacia: the 20-year experience of a single center
Related Experiment Video
Updated: Jul 4, 2025

Manufacture of a Multi-Purpose Low-Cost Animal Bench-Model for Teaching Tracheostomy
Published on: May 18, 2019
Caroline Gargioni Barreto1, Marcelo Costamilan Rombaldi1, Felipe Colombo de Holanda1
1Hospital de Clínicas de Porto Alegre, Departamento de Cirurgia Pediátrica, Porto Alegre, RS, Brazil.

Objective:
In children with tracheobronchomalacia, surgical management should be reserved for the most severe cases and be specific to the type and location of tracheobronchomalacia. The goal of this study is to describe the presentation and outcomes of children with severe tracheobronchomalacia undergoing surgery.
Methods:
Retrospective case series of 20 children operated for severe tracheobronchomalacia at a tertiary hospital from 2003 to 2023. Data were collected on symptoms age at diagnosis, associated comorbidities, previous surgery, age at surgery, operative approach, time of follow-up, and outcome. Surgical success was defined as symptom improvement.
Results:
The most frequent symptoms of severe tracheobronchomalacia were stridor (50 %), cyanosis (50 %), and recurrent respiratory infections (45 %). All patients had one or more underlying conditions, most commonly esophageal atresia (40 %) and prematurity (35 %). Bronchoscopy were performed in all patients. Based on etiology, patients underwent the following procedures: anterior aortopexy (n = 15/75 %), posterior tracheopexy (n = 4/20 %), and/or posterior descending aortopexy (n = 4/20 %). Three patients underwent anterior aortopexy and posterior tracheopexy procedures. After a median follow-up of 12 months, 16 patients (80 %) had improvement in respiratory symptoms. Decannulation was achieved in three (37.5 %) out of eight patients with previous tracheotomy. The presence of dying spells at diagnosis was associated with surgical failure.
Conclusions:
Isolated or combined surgical procedures improved respiratory symptoms in 80 % of children with severe tracheobronchomalacia. The choice of procedure should be individualized and guided by etiology: anterior aortopexy for anterior compression, posterior tracheopexy for membranous intrusion, and posterior descending aortopexy for left bronchus obstruction.
More Related Videos
Related Concept Videos
 01:22
Trachea
Anatomical Features:
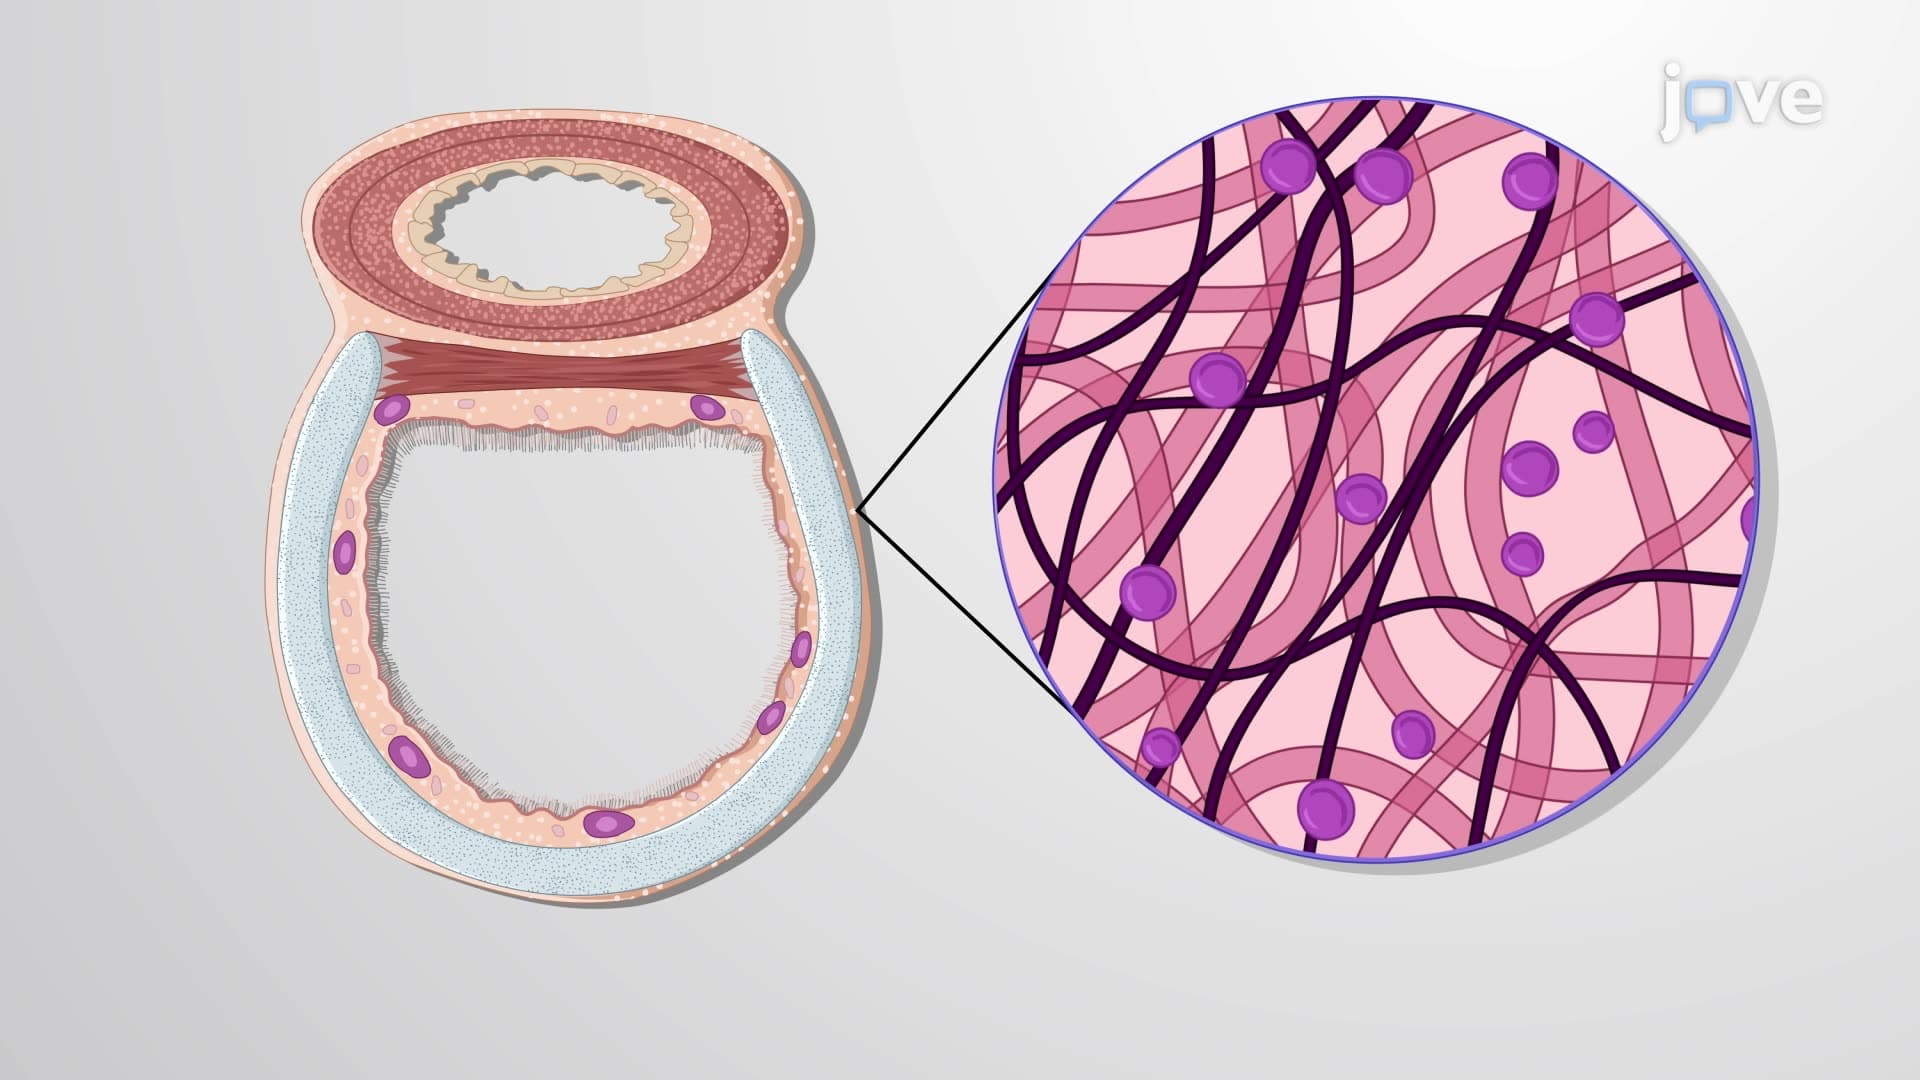
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
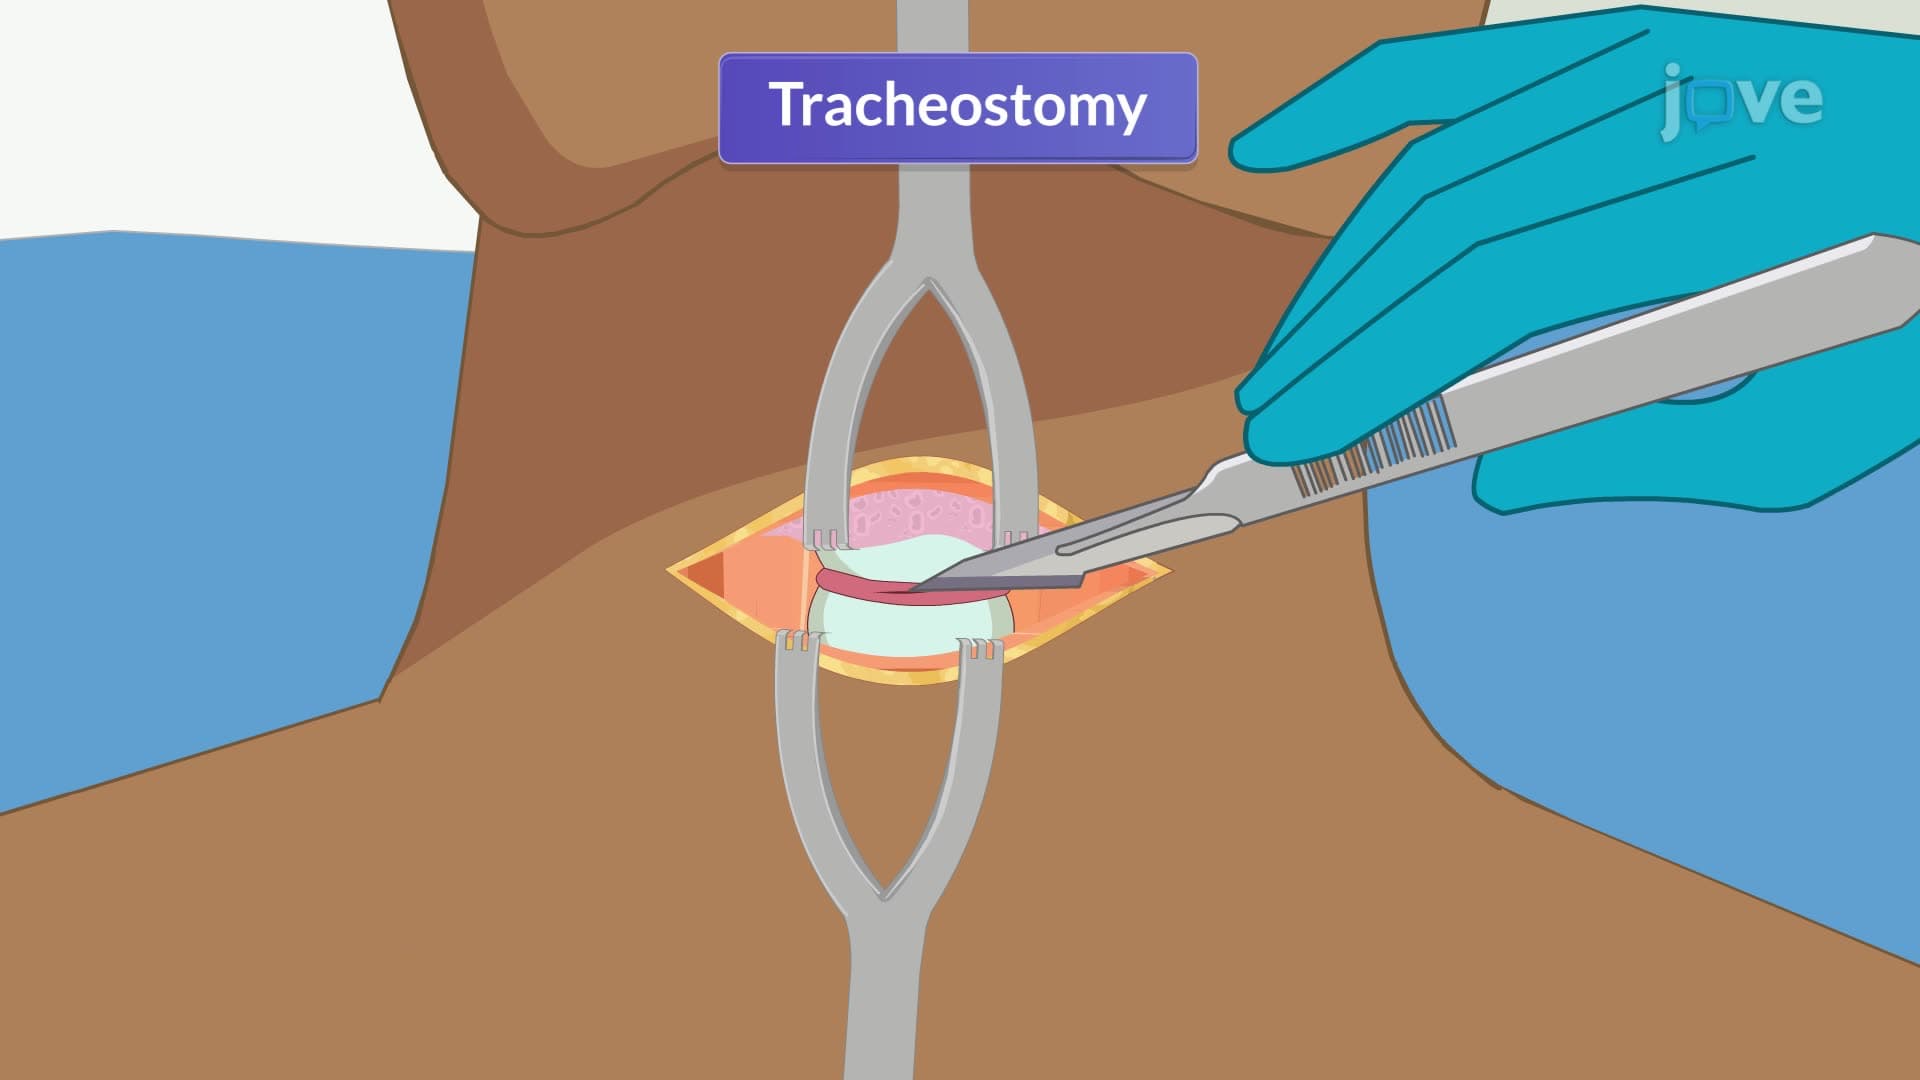
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes:
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...