Related Experiment Video
Updated: Jul 4, 2025


Real-Time Cardiac Mapping with a Noninvasive Imageless Electrocardiographic Imaging System
Published on: April 11, 2025
Local VA index for the differential diagnosis of supraventricular tachycardia
Benjamin Bouyer1, Nicolas Derval1, Thomas Pambrun1
1Hôpital Cardiologique du Haut Lévêque, CHU Bordeaux, Pessac, France; IHU LIRYC (L'Institut de Rythmologie et Modélisation Cardiaque), Université de Bordeaux, Pessac, France.

Background:
Differentiating between atypical atrioventricular nodal reentrant tachycardia (AVNRT) and orthodromic reciprocating tachycardia utilizing a septal accessory pathway is a complex challenge.
Objective:
The purpose of this study was to describe the "local VA index," a straightforward method based on signals from the coronary sinus catheter, to distinguish between these arrhythmias during tachycardia and entrainment. The ventriculoatrial (VA) interval on the coronary sinus catheter is measured during tachycardia and entrainment, at the site of earliest atrial activity. The difference between these 2 situations defines the "local VA index." We also propose a mechanism to clarify the limitations of historical pacing maneuvers, such as postpacing interval minus tachycardia cycle length (PPI-TCL) and stimulus-atrial interval minus ventriculoatrial interval (SA-VA), by examining nodal decrement and intraventricular conduction delay.
Methods:
In a retrospective study of 75 patients referred for supraventricular tachycardia evaluation, 37 were diagnosed with atrioventricular reentrant tachycardia (AVRT) with orthodromic reciprocating tachycardia, and 38 with AVNRT (27 typical, 11 atypical).
Results:
In comparison to AVRT patients, AVNRT patients exhibited longer PPI-TCL (176 ± 47 ms vs 113 ± 42 ms; P <.01) and SA-VA (138 ± 47 ms vs 64 ± 28 ms; P <.01). The AVRT group had mean local VA index of -1 ± 13 ms, whereas the AVNRT group had a significantly longer index of 91 ± 46 ms (P <.01). An optimal threshold for differentiation was a local VA index of 40 ms. Importantly, there was no significant correlation between pacing cycle length and nodal decrement as well as intraventricular delay related to pathway location. This interindividual variability might explain misleading interpretations of PPI-TCL and SA-VA.
Conclusion:
This novel approach is advantageous because of its simplicity and effectiveness, requiring only 2 diagnostic catheters. A local VA interval difference <40 ms provides a clear distinction for AVRT.
More Related Videos
 06:57
Ablation of Ischemic Ventricular Tachycardia Using a Multipolar Catheter and 3-dimensional Mapping System for High-density Electro-anatomical Reconstruction
Published on: January 31, 2019
 05:43
Author Spotlight: Improving Lesion Contiguity in Pulmonary Vein Isolation via Proactive Esophageal Cooling
Published on: April 19, 2024
Related Concept Videos
 01:28
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow...
 01:16
ECG Interpretation of Arrhythmias I: Sinus Arrhythmias
Types of Arrhythmias
Sinus Node Arrhythmias
Sinus Bradycardia: Originating from the sinoatrial (SA) node, sinus bradycardia involves slower impulses, resulting in a heart rate of less than 60 beats per minute (bpm). Causes include sleep, vagal stimulation, beta-blockers, hypothyroidism,...
 01:25
Assessment of apical radial pulse
The A-R pulse assessment involves simultaneous evaluation of the apical and radial pulses. When the apical and radial pulse rates vary, this assessment helps identify a pulse deficit.
Pre-Procedural Preparation
 01:17
Assessment of apical pulse
Assessing the apical pulse is a critical nursing procedure, particularly indicated for:
 01:28
Mechanism of Cardiac Arrhythmias
 01:25
Cardiovascular System Abnormal Findings II: Auscultation
Abnormal Heart Sounds
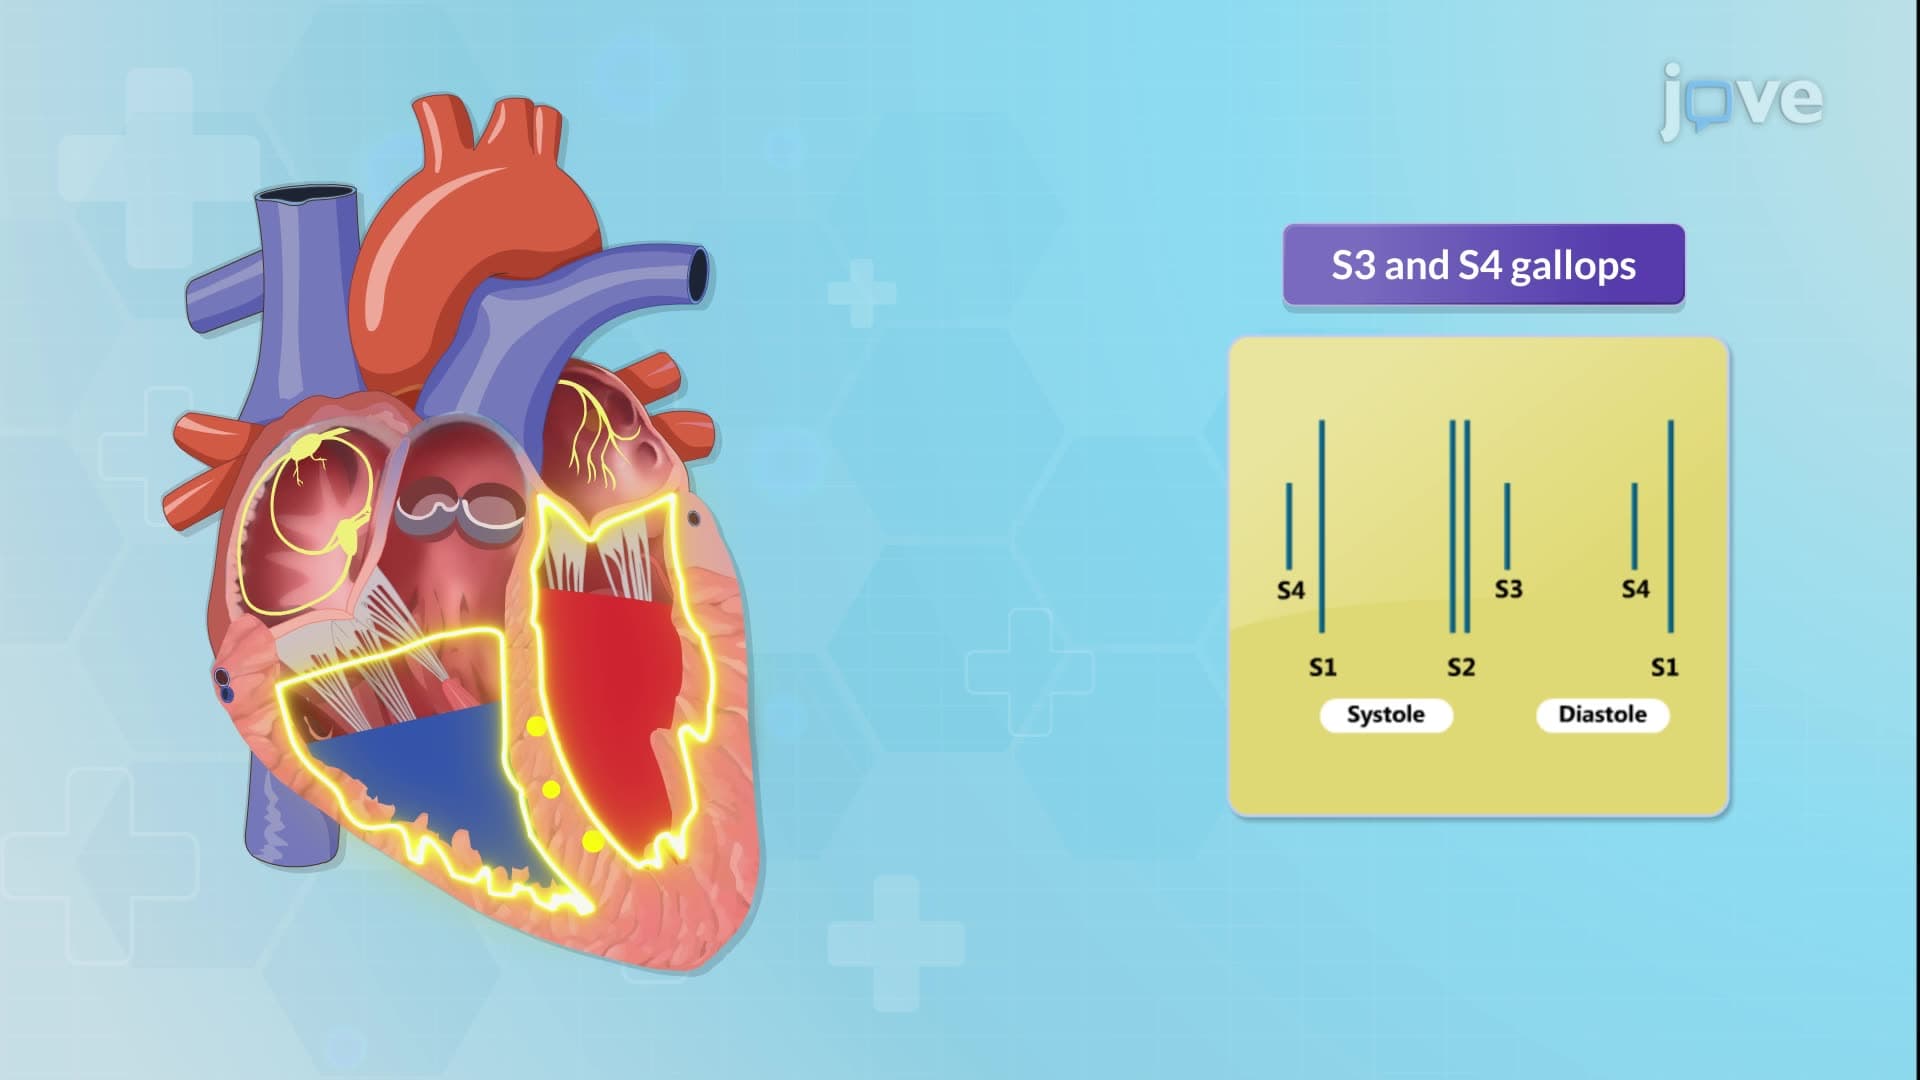
Gallops: