Related Experiment Video
Updated: Aug 15, 2026
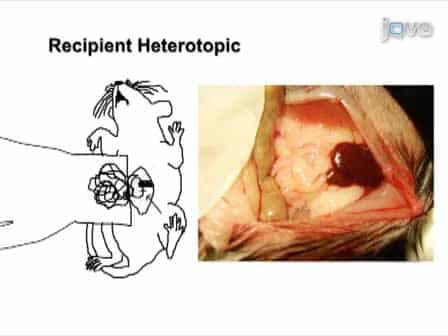

Heterotopic and Orthotopic Tracheal Transplantation in Mice used as Models to Study the Development of Obliterative Airway Disease
Published on: January 20, 2010
Surgery for tracheal and laryngotracheal stenosis: a historical case series
Marco Mammana1, Vincenzo Verzeletti1, Matteo Baldi1
1Thoracic Surgery Unit, Department of Cardiac, Thoracic, Vascular Sciences and Public Health, University of Padua, Padua, Italy.

Objectives:
Benign (laryngo-)tracheal stenosis is a relatively rare pathology and its surgical treatment is performed only at few specialized centres. This study aims to investigate outcomes after (laryngo-)tracheal resection-anastomosis, to explore potential risk factors for postoperative complications and to assess whether, over a 33-year period, there were major changes in surgical indications, techniques or outcomes.
Methods:
Retrospective, single-centre review of all consecutive patients who underwent tracheal or laryngo-tracheal resection/anastomosis for benign pathologies from 1990 to 2023.
Results:
Overall, 211 patients underwent tracheal (149 patients, 70.6%) and laryngo-tracheal (62 patients, 29.4%) resection-anastomosis. Of these, 195 patients (93.8%) were affected by iatrogenic stenosis, while 13 (6.2%) suffered from idiopathic stenosis. The median length of stenosis was 25 mm (interquartile range 1-3, 20-30). The overall morbidity rate was 27.5%, while major morbidity occurred in 10.5% of cases. One patient (0.5%) died in the postoperative period. Glottic oedema (17 patients, 8.1%), granulations (12 patients, 5.7%) and restenosis (10 patients, 4.7%) were the main complications. The only independent risk factor for postoperative complications was the length of the resected airway (P = 0.019). In the latest half of the study period, an older median age was observed, and no patient with idiopathic tracheal stenosis underwent surgery. Postoperative outcomes were comparable between surgical eras.
Conclusions:
Surgical treatment of (laryngo-)tracheal stenosis is challenging and should be performed by specialized centres. In our experience, morbidity and mortality rates were satisfactory, and in most cases, patients could breathe without tracheostomy. The length of the stenosis was the most significant risk factor for postoperative complications.


Related Concept Videos
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes:
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:26
Tracheostomy Suctioning I: Pre-Procedural Steps
Equipment Required
First, gather all necessary equipment: a sterile suction catheter, a sterile disposable container, sterile gloves, a towel or...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...