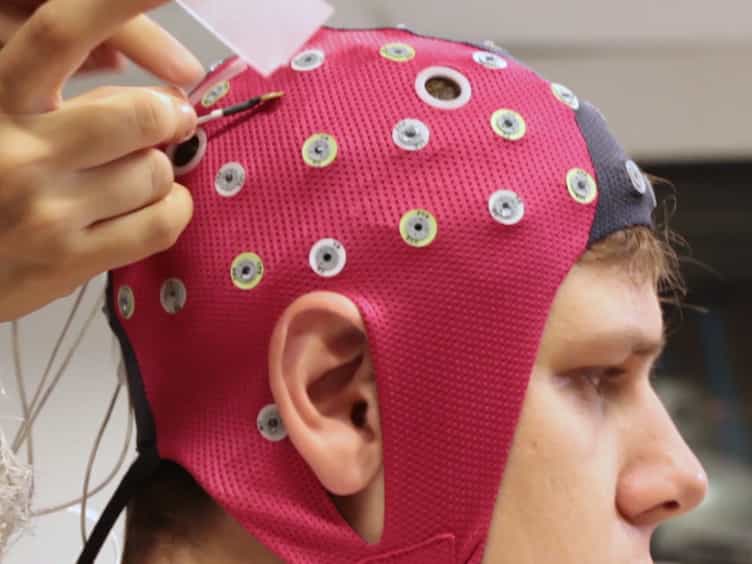

Electroencephalogram Biomarkers from Anesthesia Induction to Identify Vulnerable Patients at Risk for Postoperative
Marie Pollak1, Sophie Leroy1, Vera Röhr2
1Department of Anesthesiology and Operative Intensive Care Medicine, Charité University Medicine Berlin, Berlin, Germany.

Background:
Postoperative delirium is a common complication in elderly patients undergoing anesthesia. Even though it is increasingly recognized as an important health issue, the early detection of patients at risk for postoperative delirium remains a challenge. This study aims to identify predictors of postoperative delirium by analyzing frontal electroencephalogram at propofol-induced loss of consciousness.
Methods:
This prospective, observational single-center study included patients older than 70 yr undergoing general anesthesia for a planned surgery. Frontal electroencephalogram was recorded on the day before surgery (baseline) and during anesthesia induction (1, 2, and 15 min after loss of consciousness). Postoperative patients were screened for postoperative delirium twice daily for 5 days. Spectral analysis was performed using the multitaper method. The electroencephalogram spectrum was decomposed in periodic and aperiodic (correlates to asynchronous spectrum wide activity) components. The aperiodic component is characterized by its offset (y intercept) and exponent (the slope of the curve). Computed electroencephalogram parameters were compared between patients who developed postoperative delirium and those who did not. Significant electroencephalogram parameters were included in a binary logistic regression analysis to predict vulnerability for postoperative delirium.
Results:
Of 151 patients, 50 (33%) developed postoperative delirium. At 1 min after loss of consciousness, postoperative delirium patients demonstrated decreased alpha (postoperative delirium: 0.3 μV2 [0.21 to 0.71], no postoperative delirium: 0.55 μV2 [0.36 to 0.74]; P = 0.019] and beta band power [postoperative delirium: 0.27 μV2 [0.12 to 0.38], no postoperative delirium: 0.38 μV2 [0.25 to 0.48]; P = 0.003) and lower spectral edge frequency (postoperative delirium: 10.45 Hz [5.65 to 15.04], no postoperative delirium: 14.56 Hz [9.51 to 16.65]; P = 0.01). At 15 min after loss of consciousness, postoperative delirium patients displayed a decreased aperiodic offset (postoperative delirium: 0.42 μV2 (0.11 to 0.69), no postoperative delirium: 0.62 μV2 [0.37 to 0.79]; P = 0.004). The logistic regression model predicting postoperative delirium vulnerability demonstrated an area under the curve of 0.73 (0.69 to 0.75).
Conclusions:
The findings suggest that electroencephalogram markers obtained during loss of consciousness at anesthesia induction may serve as electroencephalogram-based biomarkers to identify at an early time patients at risk of developing postoperative delirium.
More Related Videos
 08:23
Adaptation of Microelectrode Array Technology for the Study of Anesthesia-induced Neurotoxicity in the Intact Piglet Brain
Published on: May 12, 2018
 10:23
Equipment Setup and Artifact Removal for Simultaneous Electroencephalogram and Functional Magnetic Resonance Imaging for Clinical Review in Epilepsy
Published on: June 23, 2023
Related Concept Videos
 01:27
CNS Depressants: Alcohol and Nicotine
 01:29
Hepatic Encephalopathy