The Relationship of Spinal Anesthesia Dosing Based on Thecal Sac Area to Anesthetic Failure in Lumbar Surgery
Related Experiment Video
Updated: Jul 4, 2025
Author Spotlight: Enhancing Success of Ultrasound-Guided Neuraxial Anesthesia in Cases with Difficult Anatomy
Published on: January 31, 2025
Jainith Patel1, Helen Karimi1, Michelle Olmos1
1Department of Neurosurgery, Tufts Medical Center, Tufts University School of Medicine, Boston , Massachusetts , USA.

Background And Objectives:
Greater thecal sac volumes are associated with an increased risk of spinal anesthesia (SA) failure. The thecal sac cross-sectional area accurately predicts thecal sac volume. The thecal sac area may be used to adjust the dose and prevent anesthetic failure. We aim to assess the rate of SA failure in a prospective cohort of lumbar surgery patients who receive an individualized dose of bupivacaine based on preoperative measurement of their thecal sac area.
Methods:
A total of 80 patients prospectively received lumbar spine surgery under SA at a single academic center (2022-2023). Before surgery, the cross-sectional area of the thecal sac was measured at the planned level of SA injection using T2-weighted MRI. Patients with an area <175 mm 2 , equal to or between 175 and 225 mm 2 , and >225 mm 2 received an SA injection of 15, 20, or 25 mg of 0.5% isobaric bupivacaine, respectively. Instances of anesthetic failure and adverse outcomes were noted. Incidence of SA failure was compared with a retrospectively obtained control cohort of 250 patients (2019-2022) who received the standard 15 mg of bupivacaine.
Results:
No patients in the individualized dose cohort experienced failure of SA compared with 14 patients (5.6%) who experienced failure in the control cohort ( P = .0259). The average thecal sac area was 187.49 mm 2 , and a total 28 patients received 15 mg of bupivacaine, 42 patients received 20 mg of bupivacaine, and 10 patients received 25 mg of bupivacaine. None of the patients experienced any adverse outcomes associated with SA. Patients in the individualized dose cohort and control cohort were comparable and had a similar distribution of lumbar procedures and comorbidities.
Conclusion:
Adjusting the dose of SA according to thecal sac area significantly reduces the rate of SA failure in patients undergoing lumbar spine surgery.
More Related Videos
 04:33
Spinal Hernia Repair and Cauda Equina Repositioning After Lumbar Decompression under Three-Dimensional Microscopy: A Case Report and Literature Review
Published on: November 8, 2024
 05:17
Author Spotlight: Scope of LE-ULBD as a Safe, Effective, and Minimally Invasive Approach to Treat Lumbar Spinal Stenosis
Published on: February 9, 2024
Related Concept Videos
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:29
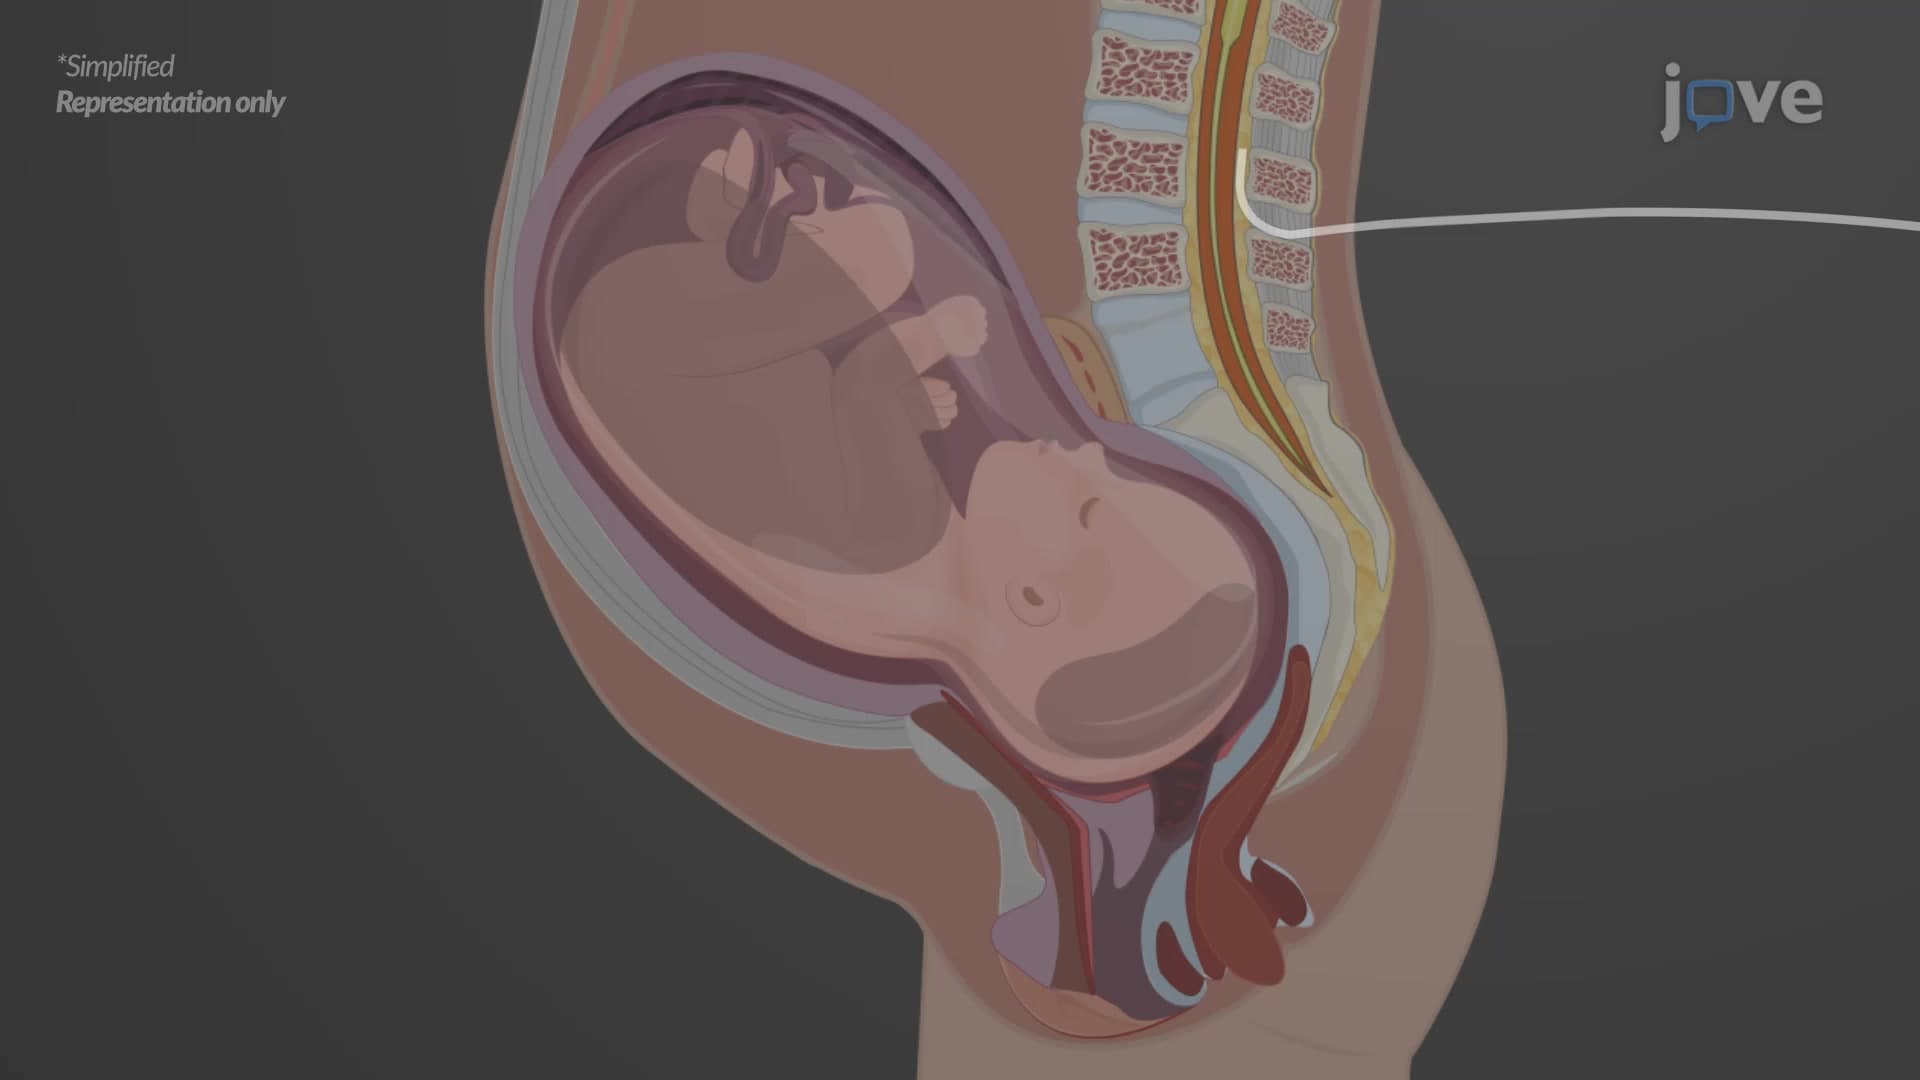
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:24
General Anesthesia: Overview
General anesthesia induces unconsciousness in the whole body, while the others target specific areas or sensations. It is administered to minimize adverse effects, maintain...
 01:16
Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia
One of the advantages of...
 01:22
Stages of General Anesthesia
 01:13
Local Anesthetics: Pharmacokinetics