Related Experiment Video
Updated: Oct 21, 2026

Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
Pharmacokinetics of methimazole in normal subjects and hyperthyroid patients

Abstract:
Serum and urinary concentrations of methimazole (MMI) were measured by high-performance liquid chromatography (HPLC) with an electrochemical detector (ECD) in 10 normal subjects and 43 hyperthyroid patients after intravenous and oral administration of the drug. The pharmacokinetic parameters of MMI were estimated in 5 normal subjects and 15 hyperthyroid patients according to a two-compartment model after intravenous injection of a 10 mg dose. The mean half-life of the distribution phase (T1/2 alpha) was 2.7 +/- 1.0 h (mean +/- SD) and 3.1 +/- 1.4 h and that of the slower-phase (T1/2 beta) was 20.7 +/- 9.6 h and 18.5 +/- 12.9 h in normal subjects and hyperthyroid patients, respectively. There were no significant differences between pharmacokinetic parameters of normal subjects and those of hyperthyroid patients. No correlations between free T4 index (FT4I) and pharmacokinetic parameters were observed. Maximum serum MMI concentrations (Cmax) (213 +/- 84 and 299 +/- 92 ng/ml) were attained 1.8 +/- 1.4 h and 2.3 +/- 0.8 h after a single dose of 10 mg in 5 normal subjects and in 15 hyperthyroid patients, respectively. In hyperthyroid patients the time taken to reach the peak concentration (Tmax) after a single dose of 10 mg was similar to that after a single 15 mg and 30 mg dose. The pharmacokinetic parameters, except Cmax and the area under the curve (AUC), were not affected by the administered dose and those, except Cmax, were not affected by the thyroid function. All urine was collected at intervals of 3 h for the first 12 h and then at 24 h and 48 h after intravenous and oral administration of MMI. In all subjects, MMI rapidly appeared in the urine and the rate of excretion was highest in the first 3 h. The cumulative urinary excretion of MMI was 5.5-8.5% of administered doses in normal subjects and hyperthyroid patients. These findings in the present study are compatible with the assumption that the extent of absorption of MMI is high, if not complete, and hyperthyroidism does not affect the kinetics of MMI, and that interindividual variation is observed in the time taken to reach the peak concentration after oral administration.
More Related Videos


Related Concept Videos
 01:20
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:14
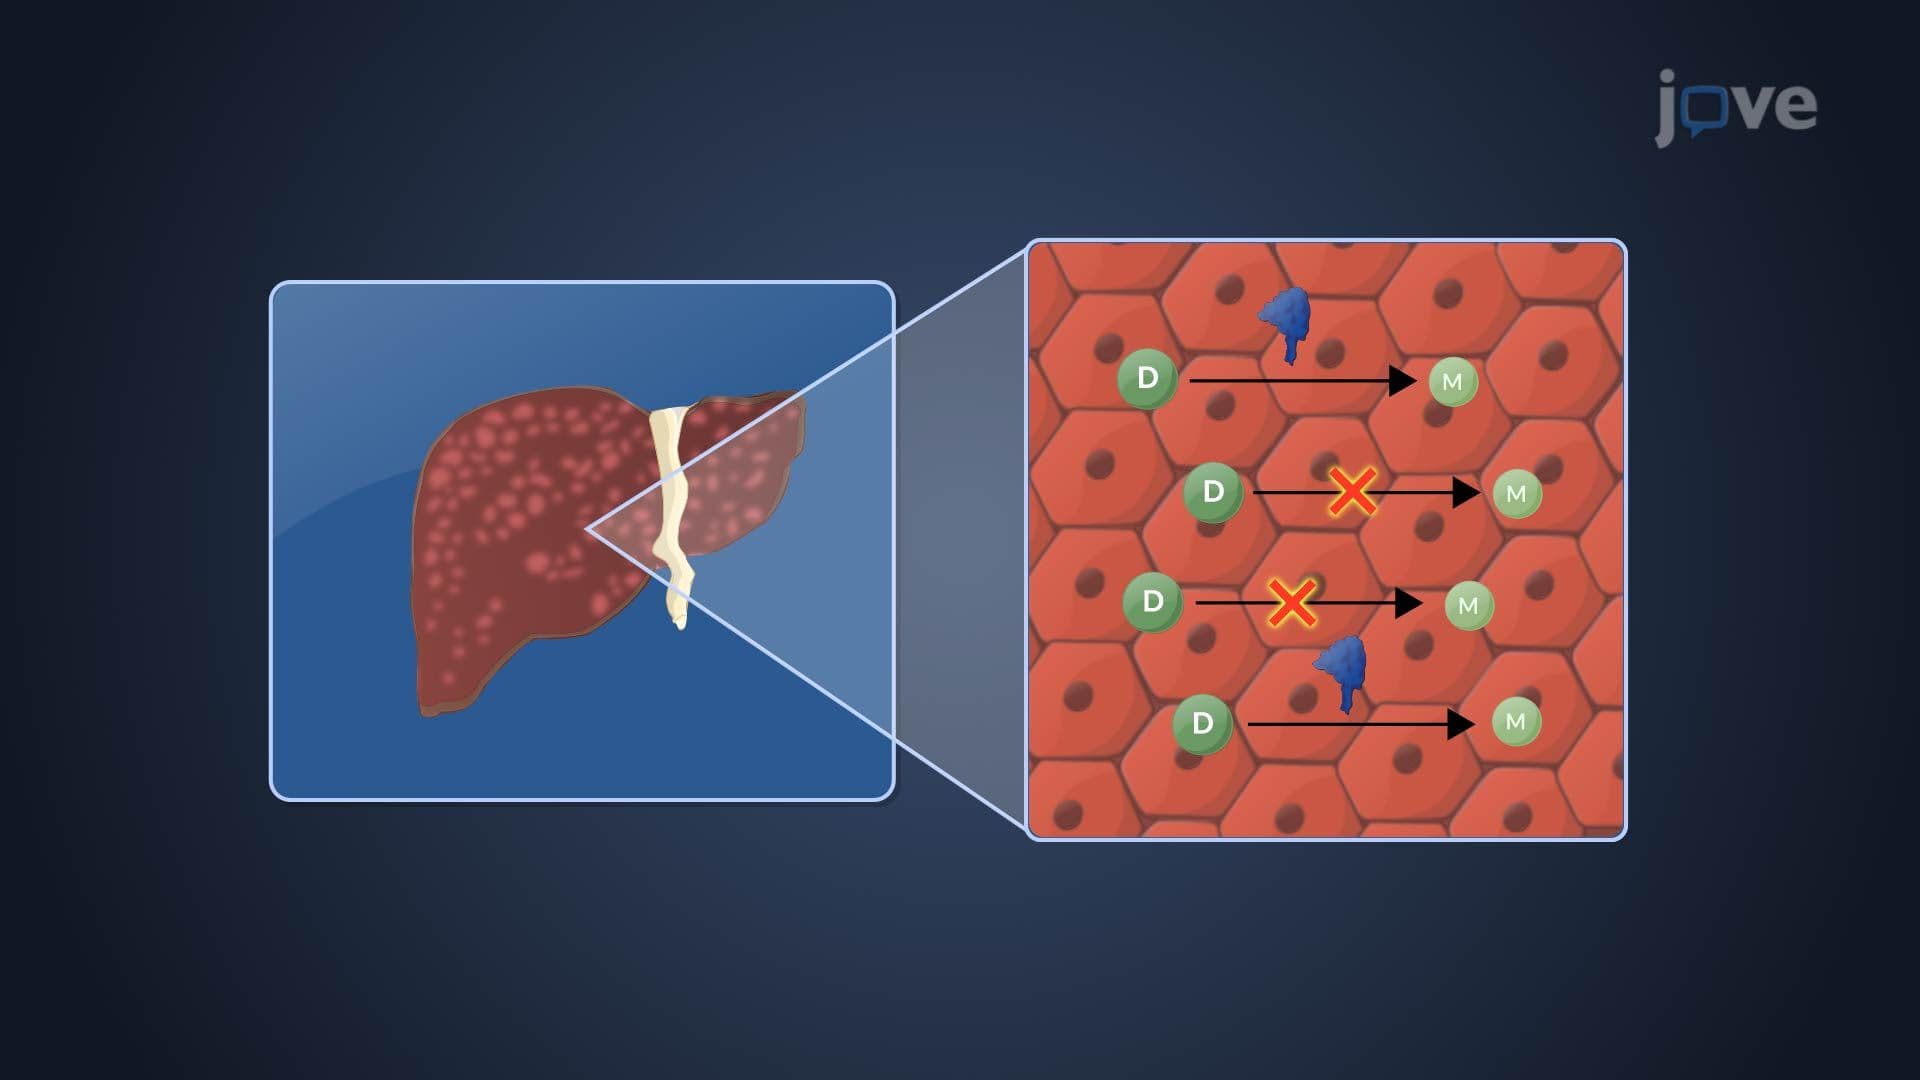
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug
 01:25
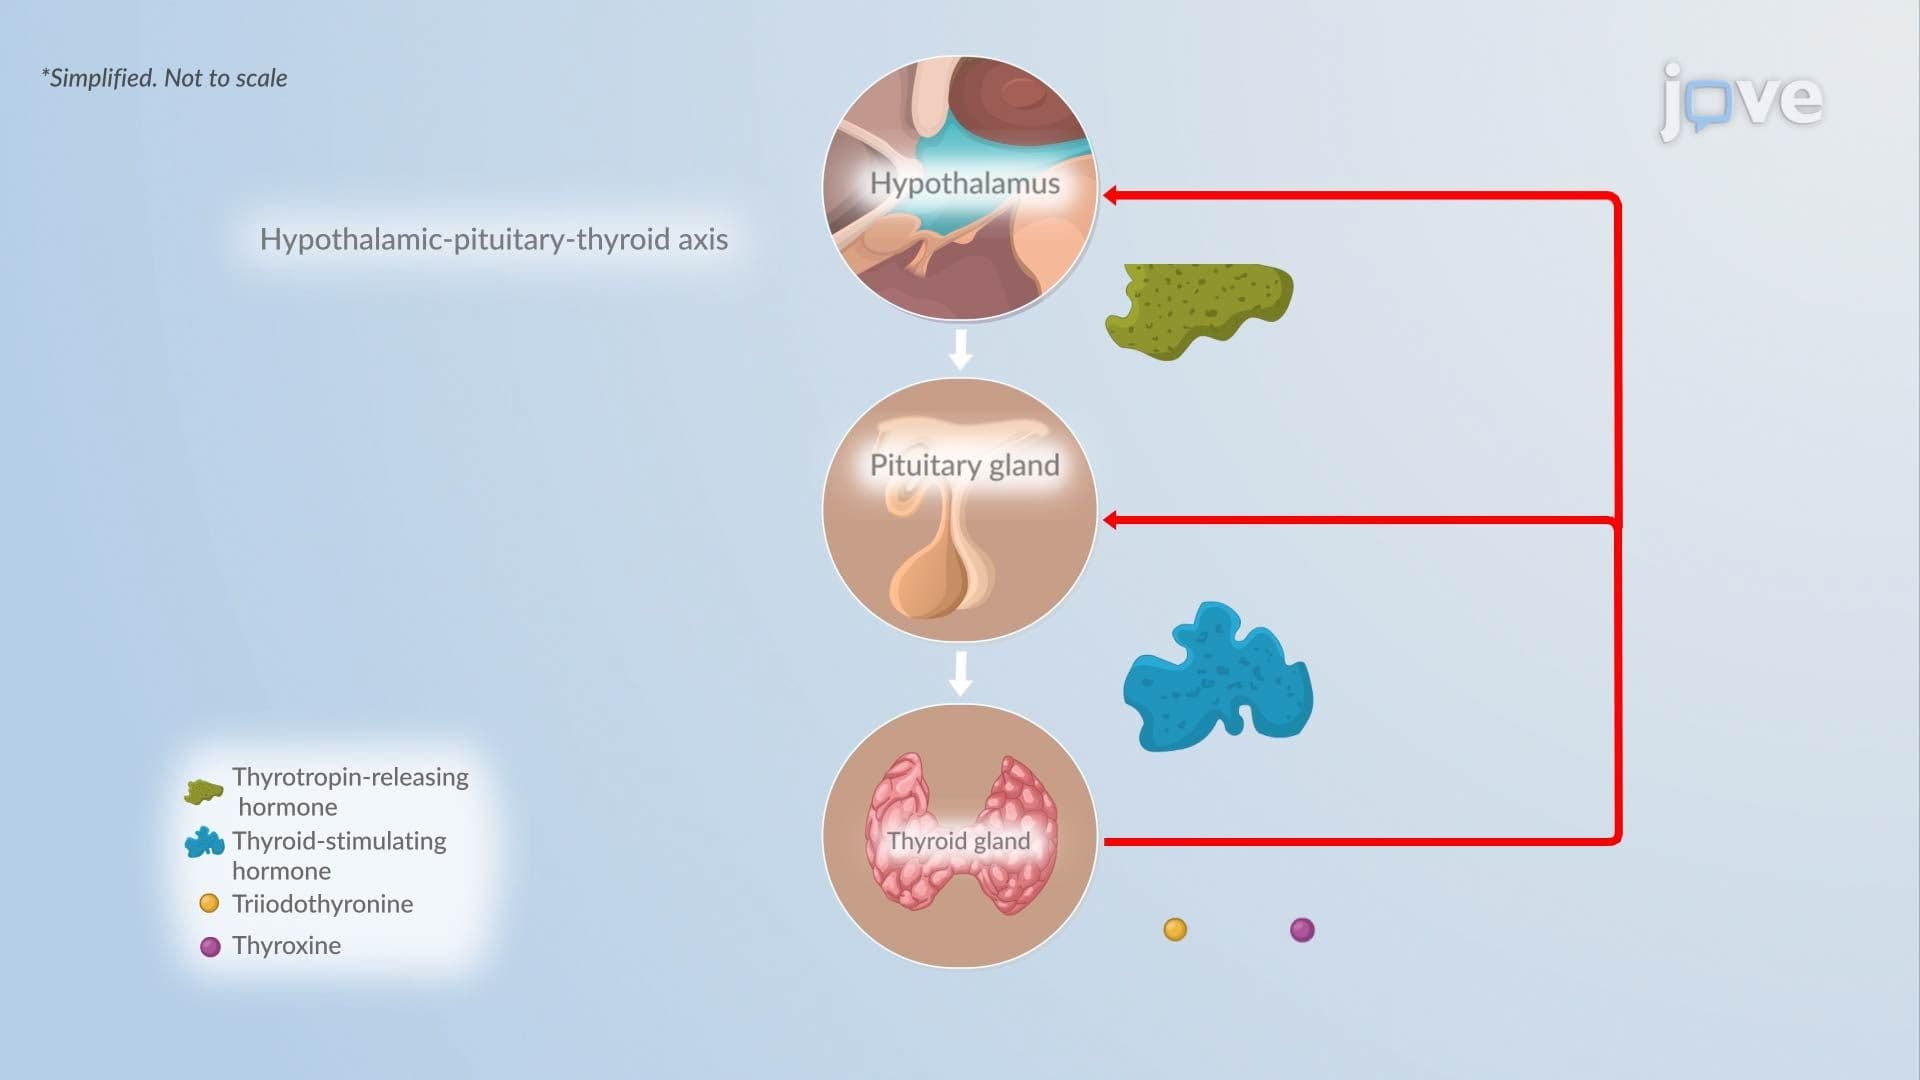
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:24
Graves Disease II: Pathophysiology