Related Experiment Video
Updated: Jul 4, 2025
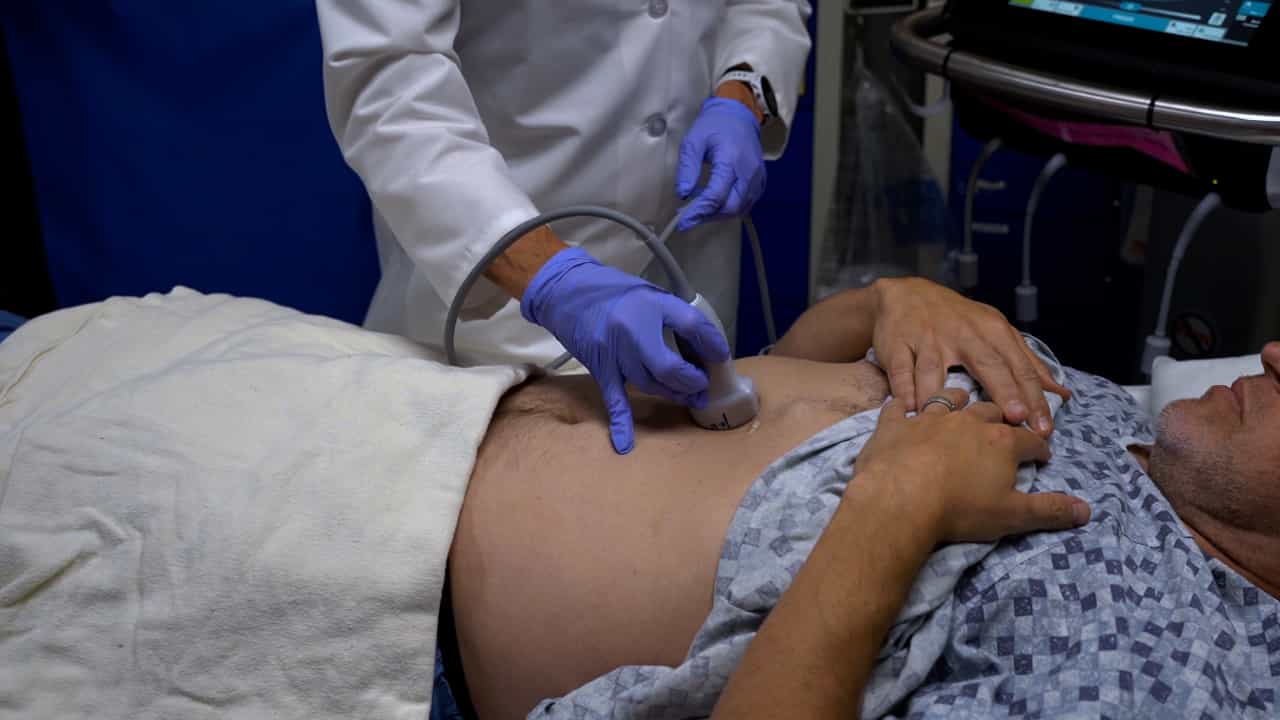
Author Spotlight: Point-of-Care Ultrasound for Gastric Content Assessment and Risk Stratification in Perioperative Care
Published on: September 22, 2023
The risk factors for silent aspiration: A retrospective case series and literature review
Barbara Jamróz1, Maria Sobol2, Joanna Chmielewska-Walczak3
1Clinical Department of Otolaryngology, National Medical Institute of the Interior and Administration, Warsaw, Poland.

Aim:
Evidence shows that 20%-30% of patients who aspirate do so silently. Research to date has not demonstrated clear evidence to indicate which patients are at higher risk of silent aspiration. Our aim was to use univariate logistic regression analysis of retrospective case review to determine potential patterns of silent aspiration.
Materials And Methods:
We conducted a retrospective analysis of 455 fiberoptic endoscopic evaluation of swallowing (FEES) reports. The patients were divided into four groups: G1 - neurological diseases (n = 93), G2 - head and neck surgery (n = 200), G3 - gastroenterological diseases (n = 94) and G4 - other patients (n = 68). Data included the occurrence or absence of saliva penetration or aspiration, of silent fluid/solid food penetration or aspiration, type of penetration or aspiration, occurrence of cranial nerve paresis, radiotherapy and tracheostomy. Univariate logistic regression was used to evaluate independent risk factors of silent aspiration in the study population. Three models with different independent variables were considered.
Results:
There is a statistically significant difference in the frequency of occurrence of silent penetration and aspiration within the groups (p < 0.001), with intraglutative being most frequent. Fluid and food penetration and aspiration correlated with saliva penetration and aspiration in all groups (p < 0.001). Cranial nerve paresis (IX and X), radiotherapy and tracheostomy correlate with saliva penetration and aspiration (p = 0.020 for cranial nerve paresis; p = 0.004 for radiotherapy; p < 0.001 for tracheostomy). One hundred and fifteen patients (45.81%) in the subgroup of patients with intraglutative aspiration had cranial nerve paresis (IX, X or IX-X).
Conclusions:
Patients who should be prioritised or considered to be at a higher need of instrumental swallowing evaluation are those with IX and X cranial nerve paresis, tracheostomy and those who have had radiotherapy, with saliva swallowing problems, especially after paraganglioma, thyroid and parathyroid glands and middle and posterior fossa tumour surgery.
What This Paper Adds:
What is already known on the subject Clinical signs of penetration or aspiration include coughing, throat clearing and voice changes, while silent penetration or aspiration patients aspirate without demonstrating any clinical symptoms. The most common consequences of silent aspiration include aspiration pneumonia, recurrent lower respiratory tract infections and respiratory failure. Additionally, malnutrition and dehydration can be indicators of silent aspiration. Patients may unknowingly reduce their oral intake and lose weight. Retrospective studies have shown that 20%-30% of patients aspirate silently (e.g. patients after stroke, acquired brain injury, head and neck cancer treatment, prolonged intubation). Clinical examination of swallowing can miss up to 50% of cases of silent aspiration. What this paper adds to existing knowledge Currently, silent aspiration is often discussed in neurological literature, but its applications to head and neck surgery are limited. In this study, we identify head and neck surgery patients who should be prioritised or considered to be in higher need of instrumental swallowing evaluation due to a higher risk of silent aspiration. What are the potential or actual clinical implications of this work? Post-treatment structural changes can result in lower cranial nerve paresis (IX, X, XII) and face injury, in which vagus and glossopharyngeal nerves are injured. After tracheostomy and radiotherapy, patients with problems swallowing saliva need careful clinical examination, particularly cranial nerve examination.
More Related Videos
 04:32
Murine Oropharyngeal Aspiration Model of Ventilator-associated and Hospital-acquired Bacterial Pneumonia
Published on: June 28, 2018
 07:54
Drug-Induced Sleep Endoscopy DISE with Target Controlled Infusion TCI and Bispectral Analysis in Obstructive Sleep Apnea
Published on: December 6, 2016
Related Concept Videos
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:20
Sputum Studies II: Culture and Sensitivity
Sputum culture and sensitivity is a medical procedure used to diagnose bacterial infections in the respiratory tract and select the most appropriate antibiotics for treatment. This process involves analyzing sputum samples of thick and opaque secretions produced in the lungs and airways. These samples are collected from patients and then sent to the laboratory for analysis.
The test can identify various pathogens responsible for respiratory infections, including Streptococcus,...
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:29
Suctioning the Nasopharyngeal Airway
Equipment Required