Related Experiment Video
Updated: Jul 4, 2025
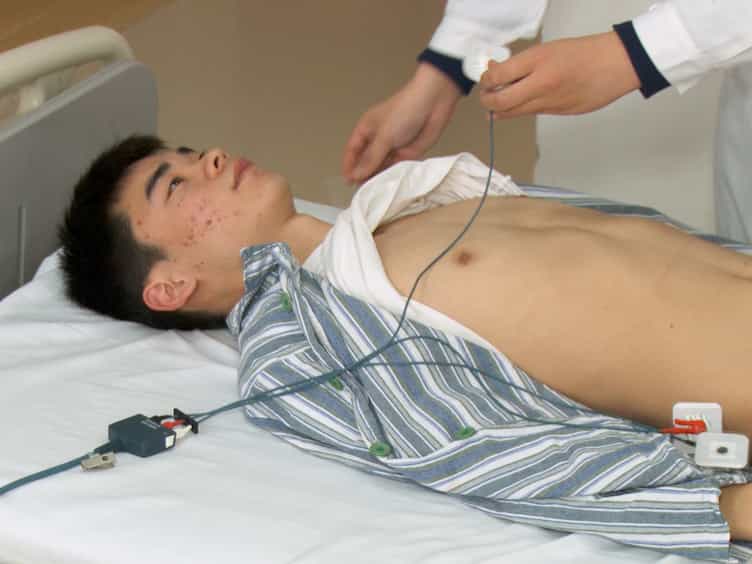

Measuring the Carotid to Femoral Pulse Wave Velocity Cf-PWV to Evaluate Arterial Stiffness
Published on: May 3, 2018
Ethnicity-specific blood pressure thresholds based on cardiovascular and renal complications: a prospective study in
Donghan Su1, Huanhuan Yang1, Zekun Chen1
1Vanke School of Public Health, Tsinghua University, Beijing, China.

Insights
New blood pressure thresholds are needed for ethnic minority groups in the UK. Ethnicity-specific systolic blood pressure (SBP) cutoffs can improve hypertension management and reduce cardiovascular and renal complications.
Area of Science:
- Cardiovascular research
- Renal medicine
- Public health
Background:
- Current hypertension guidelines may not accurately assess cardiovascular and renal risks in UK's non-White populations.
- There is a need to question the appropriateness of existing hypertension thresholds for diverse ethnic groups.
Purpose of the Study:
- To establish ethnicity-specific systolic blood pressure (SBP) cutoffs for ethnic minority populations in the UK.
- To assess the efficacy of these ethnicity-specific cutoffs in predicting adverse cardiovascular and renal outcomes.
Main Methods:
- Analysis of UK Biobank data from 444,418 participants across White, South Asian, Black Caribbean, and Black African populations.
- Poisson regression models used to determine ethnicity-specific SBP thresholds for composite outcomes (atherosclerotic cardiovascular disease, heart failure, chronic kidney disease).
- Models adjusted for clinical, sociodemographic, and behavioral factors; performance assessed using population-attributable fraction (PAF).
Main Results:
- South Asians showed the highest predicted incidence rate of composite outcomes at any given SBP.
- Ethnicity-specific SBP thresholds for equivalent risk to White individuals at 140 mm Hg were 123 mm Hg for South Asians, 156 mm Hg for Black Caribbeans, and 165 mm Hg for Black Africans.
- Ethnicity-specific thresholds improved prediction and increased PAF for composite outcomes in South Asians and Black Africans compared to guideline thresholds.
Conclusions:
- Guideline-recommended blood pressure thresholds may inaccurately estimate risks for Black and South Asian populations.
- Implementing ethnicity-specific SBP thresholds can enhance risk prediction and optimize hypertension management.
- This approach aims to reduce ethnic disparities in cardiorenal complications.
Background:
The appropriateness of hypertension thresholds for triggering action to prevent cardiovascular and renal complications among non-White populations in the UK is subject to question. Our objective was to establish ethnicity-specific systolic blood pressure (SBP) cutoffs for ethnic minority populations and assess the efficacy of these ethnicity-specific cutoffs in predicting adverse outcomes.
Methods:
We analyzed data from UK Biobank, which included 444,418 participants from White, South Asian, Black Caribbean, and Black African populations with no history of cardiorenal complications. We fitted Poisson regression models with continuous SBP and ethnic groups, using Whites as the referent category, for the composite outcome of atherosclerotic cardiovascular disease, heart failure, and chronic kidney disease. We determined ethnicity-specific thresholds equivalent to the risks observed in Whites at SBP levels of 120, 130, and 140 mm Hg. We adjusted models for clinical characteristics, sociodemographic factors, and behavioral factors. The performance of ethnicity-specific thresholds for predicting adverse outcomes and associated population-attributable fraction (PAF) was assessed in ethnic minority groups.
Results:
After a median follow-up of 12.5 years (interquartile range, 11.7-13.2), 32,662 (7.4%) participants had incident composite outcomes. At any given SBP, the predicted incidence rate of the composite outcome was the highest for South Asians, followed by White, Black Caribbean, and Black African. For an equivalent risk of outcomes observed in the White population at an SBP level of 140 mm Hg, the SBP threshold was lower for South Asians (123 mm Hg) and higher for Black Caribbean (156 mm Hg) and Black African (165 mm Hg). Furthermore, hypertension defined by ethnicity-specific thresholds was a stronger predictor and resulted in a larger PAF for composite outcomes in South Asians (21.5% [95% CI, 2.4,36.9] vs. 11.3% [95% CI, 2.6,19.1]) and Black Africans (7.1% [95% CI, 0.2,14.0] vs. 5.7 [95% CI, -16.2,23.5]) compared to hypertension defined by guideline-recommended thresholds.
Conclusions:
Guideline-recommended blood pressure thresholds may overestimate risks for the Black population and underestimate risks for South Asians. Using ethnicity-specific SBP thresholds may improve risk estimation and optimize hypertension management toward the goal of eliminating ethnic disparities in cardiorenal complications.

Related Concept Videos
 01:18
Hypertension and Regulation of Blood Pressure
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:25
Errors occurring during blood pressure monitoring
Several factors...
 01:19
Blood Studies for Cardiovascular System II: CRP, Hcy, and Cardiac Natriuretic Peptide Markers
These markers indicate stress or strain on the heart muscle:
Natriuretic Peptides (BNP)
Cardiac myocytes produce these hormones in response to ventricular stretching...
 01:28
Factors affecting Blood pressure
Physiological Factors:
 01:15
Assessment of blood pressure in brachial artery(one-step method)
Prepare for the Procedure: