Related Experiment Video
Updated: Jul 4, 2025

Evaluation of Respiratory Muscle Activation Using Respiratory Motor Control Assessment RMCA in Individuals with Chronic Spinal Cord Injury
Published on: July 19, 2013
Respiratory function and respiratory muscle strength in adolescent idiopathic scoliosis
İrem Çetinkaya1, Tuğba Kuru Çolak2, Seda Saka3
1Department of Physiotherapy and Rehabilitation, Faculty of Health Sciences, Haliç University, 5. Levent Mahallesi, 15 Temmuz Şehitler Caddesi, No: 14/12, 34060, Eyüpsultan, Istanbul, Turkey. iremkaranki@gmail.com.

Purpose:
It was aimed to analyze the relationship of the respiratory functions, respiratory muscle strength, magnitude of the curvature, angle of trunk rotation (ATR) and brace-wearing duration in patients with adolescent idiopathic scoliosis (AIS).
Methods:
Sixty patients with AIS (43 females), with maximum Cobb angles between 20° and 66° were included in the study. ATR values were measured with a scoliometer. Respiratory function parameters (forced vital capacity [FVC], forced expiratory volume in one second [FEV1], FEV1/FVC ratio, peak expiratory flow [PEF]) and respiratory muscle strengths (maximum inspiratory pressure [MIP] and maximum expiratory pressure [MEP]) were measured by combined spirometry.
Results:
There was a negative significant correlation between maximum Cobb angle and ATR with respiratory function parameters except for PEF and FEV1/FVC (r = -0.258-0.441; p = <0.001-0.047). There was a moderate negative correlation between ATR with MIP (cmH2O) (r = -0.377; p = 0.003) and MEP (cmH2O) (r = -0.362; p = 0.005). On the other hand, no correlation was found between brace-wearing duration with respiratory functions, maximum Cobb angle and brace-wearing duration with respiratory muscle results.
Conclusion:
The results of this study showed that, respiratory functions were normal or mildly affected, and respiratory muscle strengths were weak in AIS. Increased Cobb angle and ATR negatively affected respiratory function; increased ATR was associated with decreased inspiratory and expiratory muscle strength. It is extremely important to carefully evaluate the respiratory system and to know the variables that affect respiratory functions and respiratory muscle strength in achieving optimum recovery in the holistic treatment of individuals with scoliosis.

Related Concept Videos
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:21
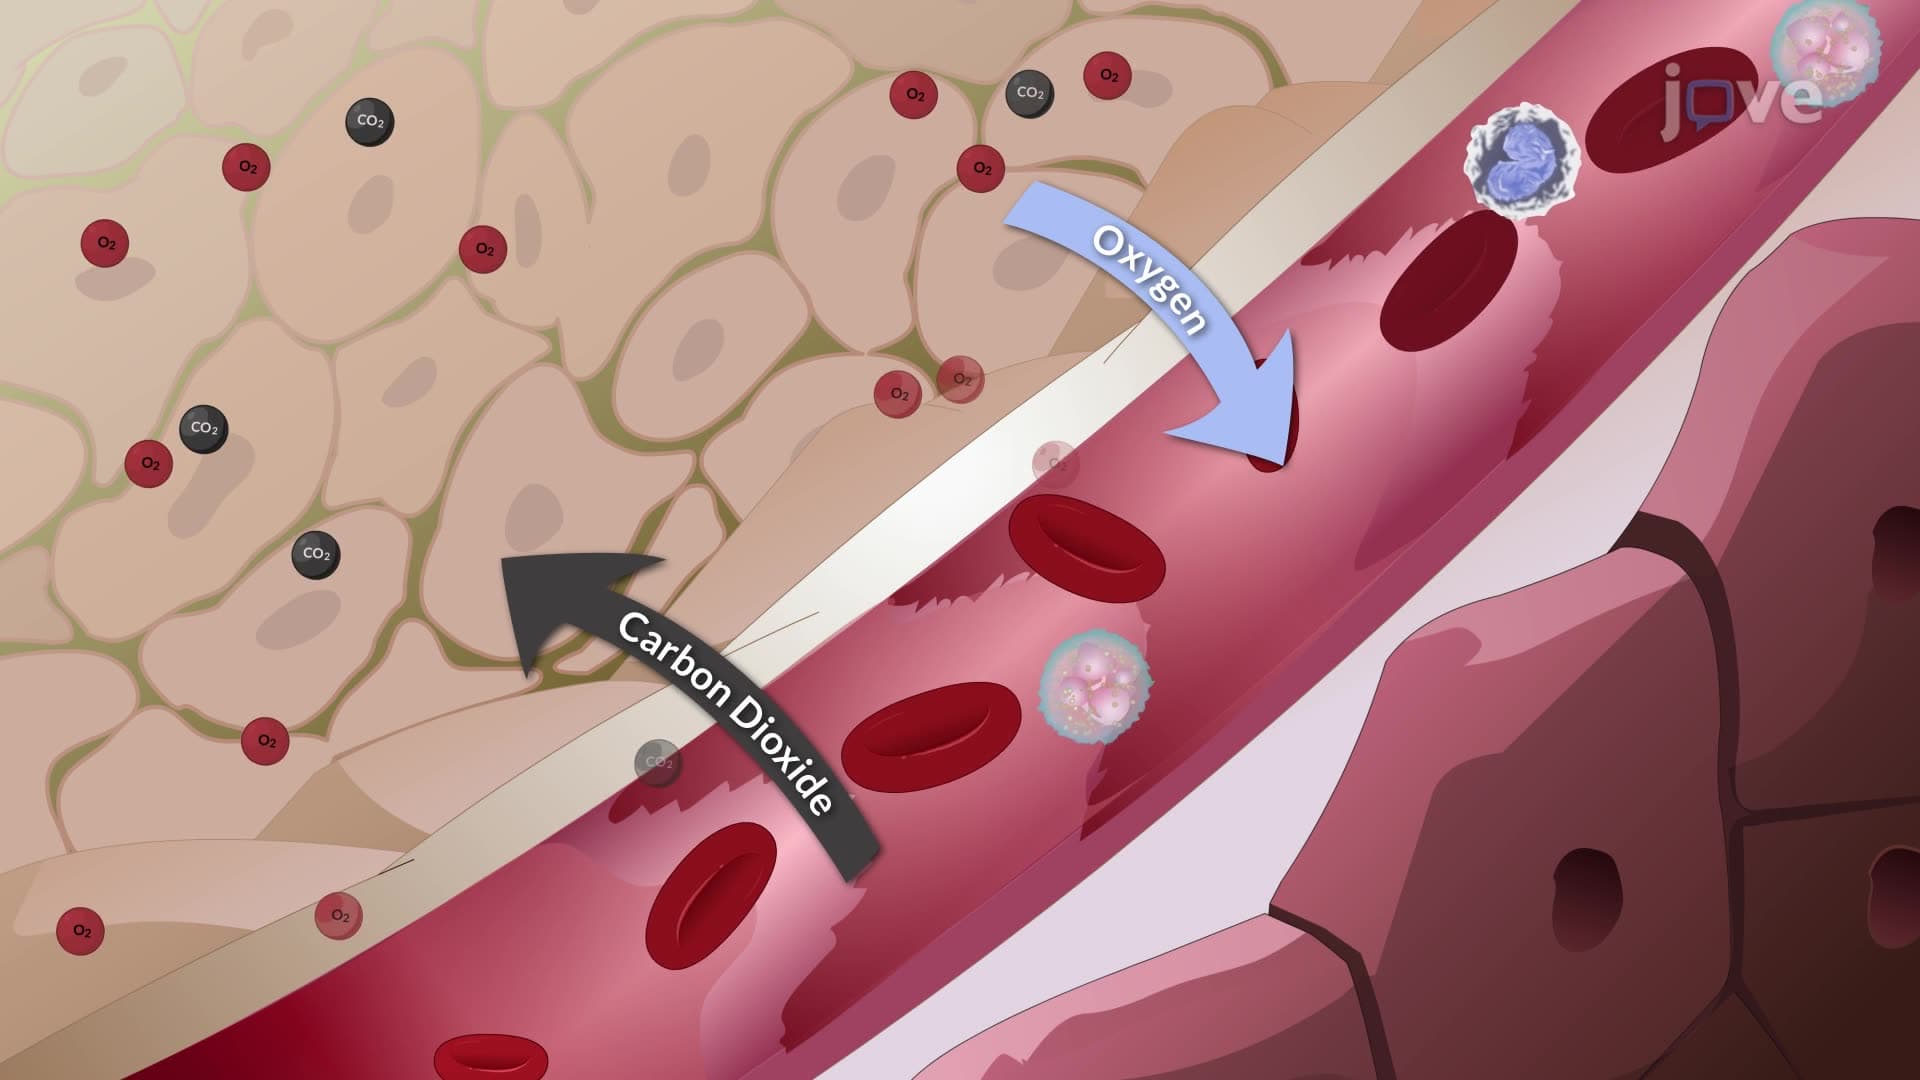
Mechanism of Breathing III: The Accessory Muscles
The respiratory system is a complex network that relies on primary respiratory muscles like the diaphragm, but also involves accessory muscles to enhance lung expansion and airflow during both inhalation and exhalation.
Enhancing Inhalation with Accessory Muscles:
Accessory muscles such as the sternocleidomastoid, scalene, intercostal, and abdominal muscles are crucial when additional respiratory effort is required, such as during deep...
 01:26
Respiratory Volumes and Capacities I
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...