Related Experiment Video
Updated: May 10, 2026
A Contusive Model of Unilateral Cervical Spinal Cord Injury Using the Infinite Horizon Impactor
Published on: July 24, 2012
Clinical characteristics of upper cervical spine injuries in children: a retrospective case series
Dayae Jeong1, Suzanne Beno1, James M Drake2
11Division of Pediatric Emergency Medicine and.

Insights
Pediatric upper cervical spine injuries (CSI) like atlanto-occipital and atlanto-axial joint injuries are severe, with complete dislocations having high mortality. Subluxations and fractures generally have better outcomes, highlighting the need for prompt diagnosis.
Area of Science:
- Pediatric Traumatology
- Orthopedic Surgery
- Radiology
Background:
- Pediatric cervical spine injuries (CSI) are a significant concern, especially in children under 8, due to unique anatomy.
- Diagnosis can be challenging due to varied presentations and limited research.
Purpose of the Study:
- To characterize the spectrum of upper pediatric CSI.
- To differentiate injury patterns and their clinical outcomes.
Main Methods:
- Retrospective case series of pediatric trauma patients (<16 years) diagnosed with upper CSI (occiput to C2) from 2000-2020.
- Inclusion criteria: bony or ligamentous injury on imaging/autopsy.
- Data collected via chart review and analyzed using descriptive statistics.
Main Results:
- 202 patients met inclusion criteria. Atlanto-occipital (AO) joint injuries occurred in 15% (complete dislocation: 93% mortality).
- Atlanto-axial (AA) joint injuries occurred in 5% (complete dislocation: high mortality).
- C1-C2 fractures (15%) and ligamentous injuries (64%) had varied presentations and generally better outcomes, especially when isolated.
Conclusions:
- AO and AA joint injuries are severe upper CSI subtypes with high mortality in complete dislocations.
- Subluxations and fractures present heterogeneously; outcomes depend on severity and associated injuries.
- Lateral cervical spine radiography is crucial during resuscitation for identifying CSI subtypes.
Objective:
Pediatric cervical spine injuries (CSI) can be devastating, and children < 8 years are particularly at risk for upper CSI given unique anatomical differences. Diagnosis of these injuries can be delayed due to variable clinical presentations and a paucity of existing literature. The authors aimed to characterize the spectrum of pediatric upper CSI.
Methods:
This was a retrospective, single-center case series of trauma patients aged < 16 years who were assessed at a level I pediatric trauma center and diagnosed with upper CSI between 2000 and 2020. Patients were included if they had evidence of bony or ligamentous injury from the occiput to C2 on imaging or autopsy. Data were obtained from manual chart review and analyzed using descriptive statistics.
Results:
In total, 502 patients were screened and 202 met inclusion criteria. Of these, 31 (15%) had atlanto-occipital (AO) joint distractions, 10 (5%) had atlanto-axial (AA) joint distractions, 31 (15%) had fractures of C1-2, and 130 (64%) had ligamentous injury without joint distraction. Of the patients with AO injury, 15 patients had complete dislocation. They presented as hemodynamically unstable with signs of herniation and 14 died (93%). In contrast, 16 had incomplete dislocation (subluxation). They usually had stable presentations and survived with good outcomes. Of the patients with AA injury, 2 had complete dislocation, presented with arrest and signs of herniation, and died. In contrast, 8 patients with subluxation mostly presented as clinically stable and all survived with little residual disability. The most common fractures of C1 were linear fractures of the lateral masses and of the anterior and posterior arches. The most common fractures of C2 were synchondrosis, hangman, and odontoid fractures. Overall, these patients had excellent outcomes. Ligamentous injuries frequently accompanied other brain or spine injuries. When these injuries were isolated, patients recovered well.
Conclusions:
Among upper CSI, AO and AA joint injuries emerged as particularly severe with high mortality rates. Both could be divided into complete dislocations or incomplete subluxations, with clear clinical differences and the former presenting with much more severe injuries. Lateral cervical spine radiography should be considered during resuscitation of unstable trauma patients to assess for these CSI subtypes. Fractures and ligamentous injuries were clinically heterogeneous, with presentations and outcomes depending on severity and associated injuries.
More Related Videos


Related Concept Videos
 01:16
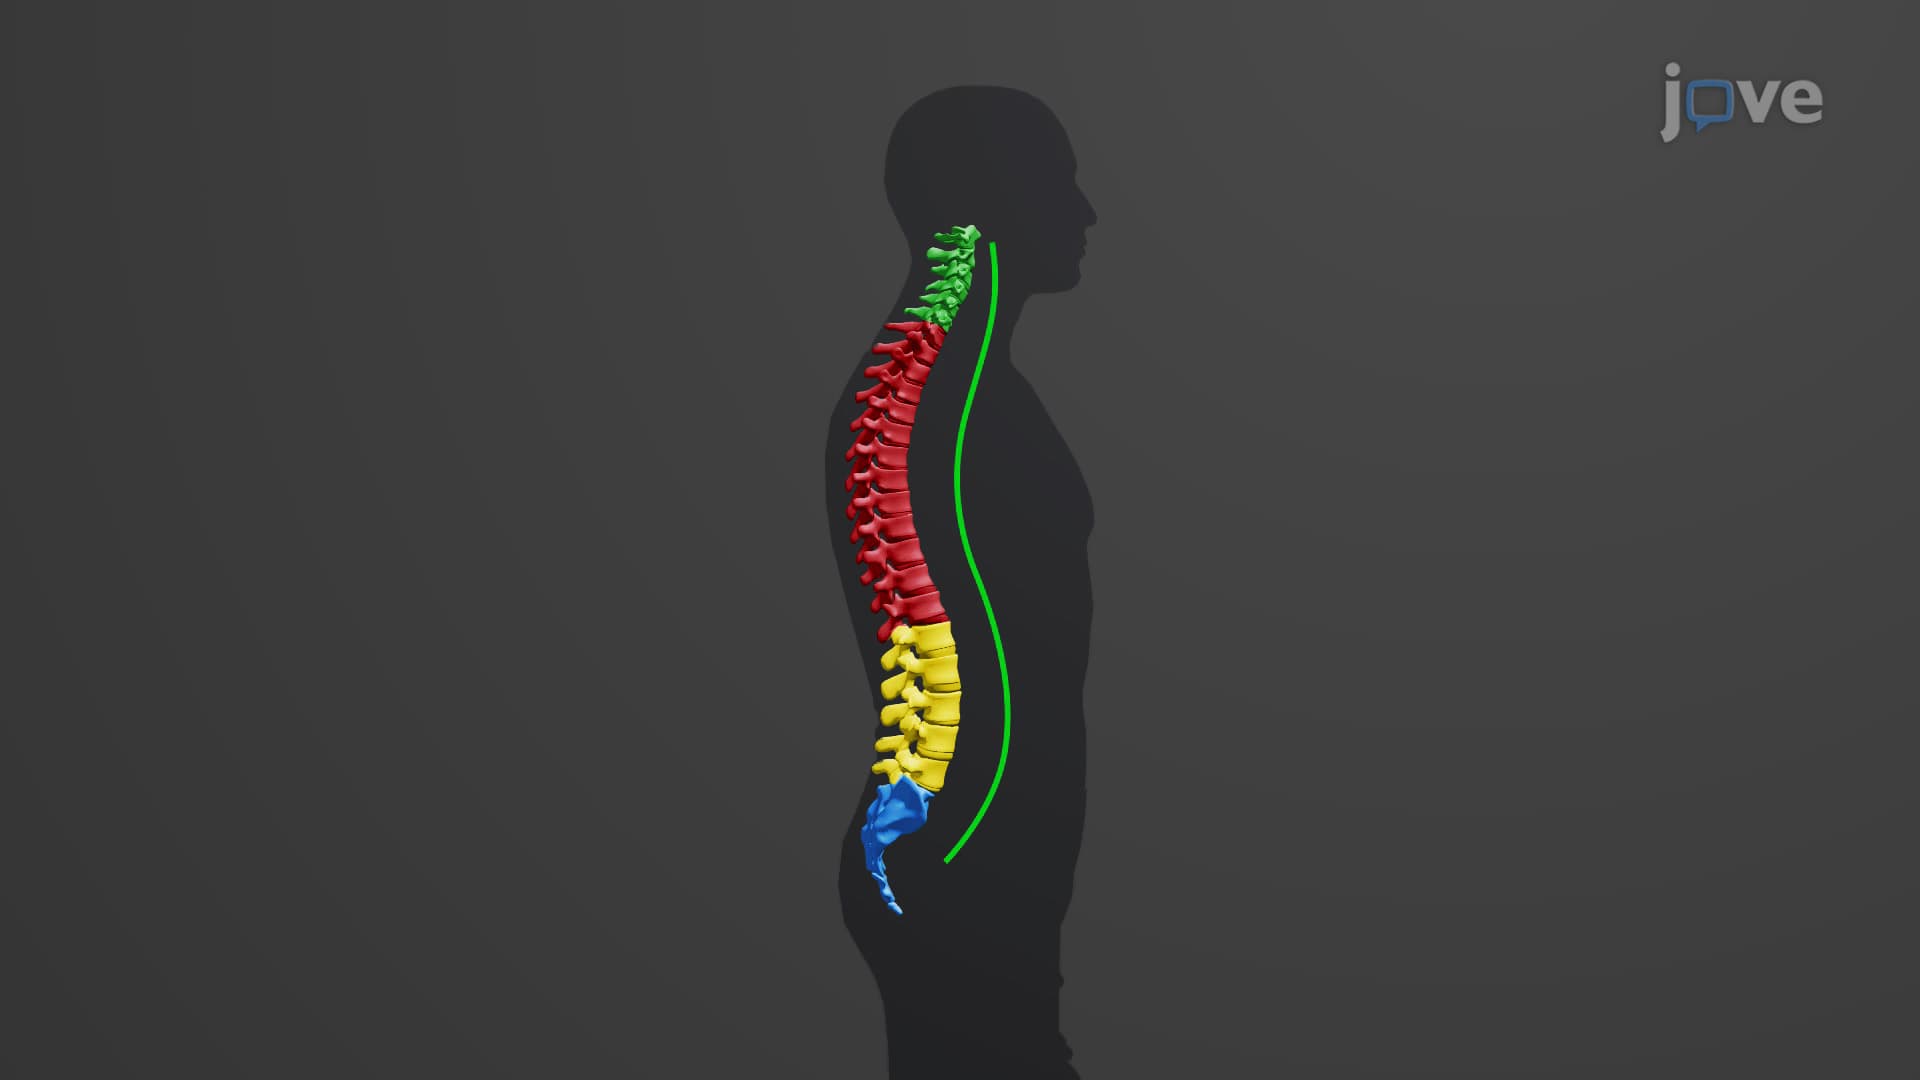
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:14
Spinal Cord Injury ll: Pathophysiology
 01:29
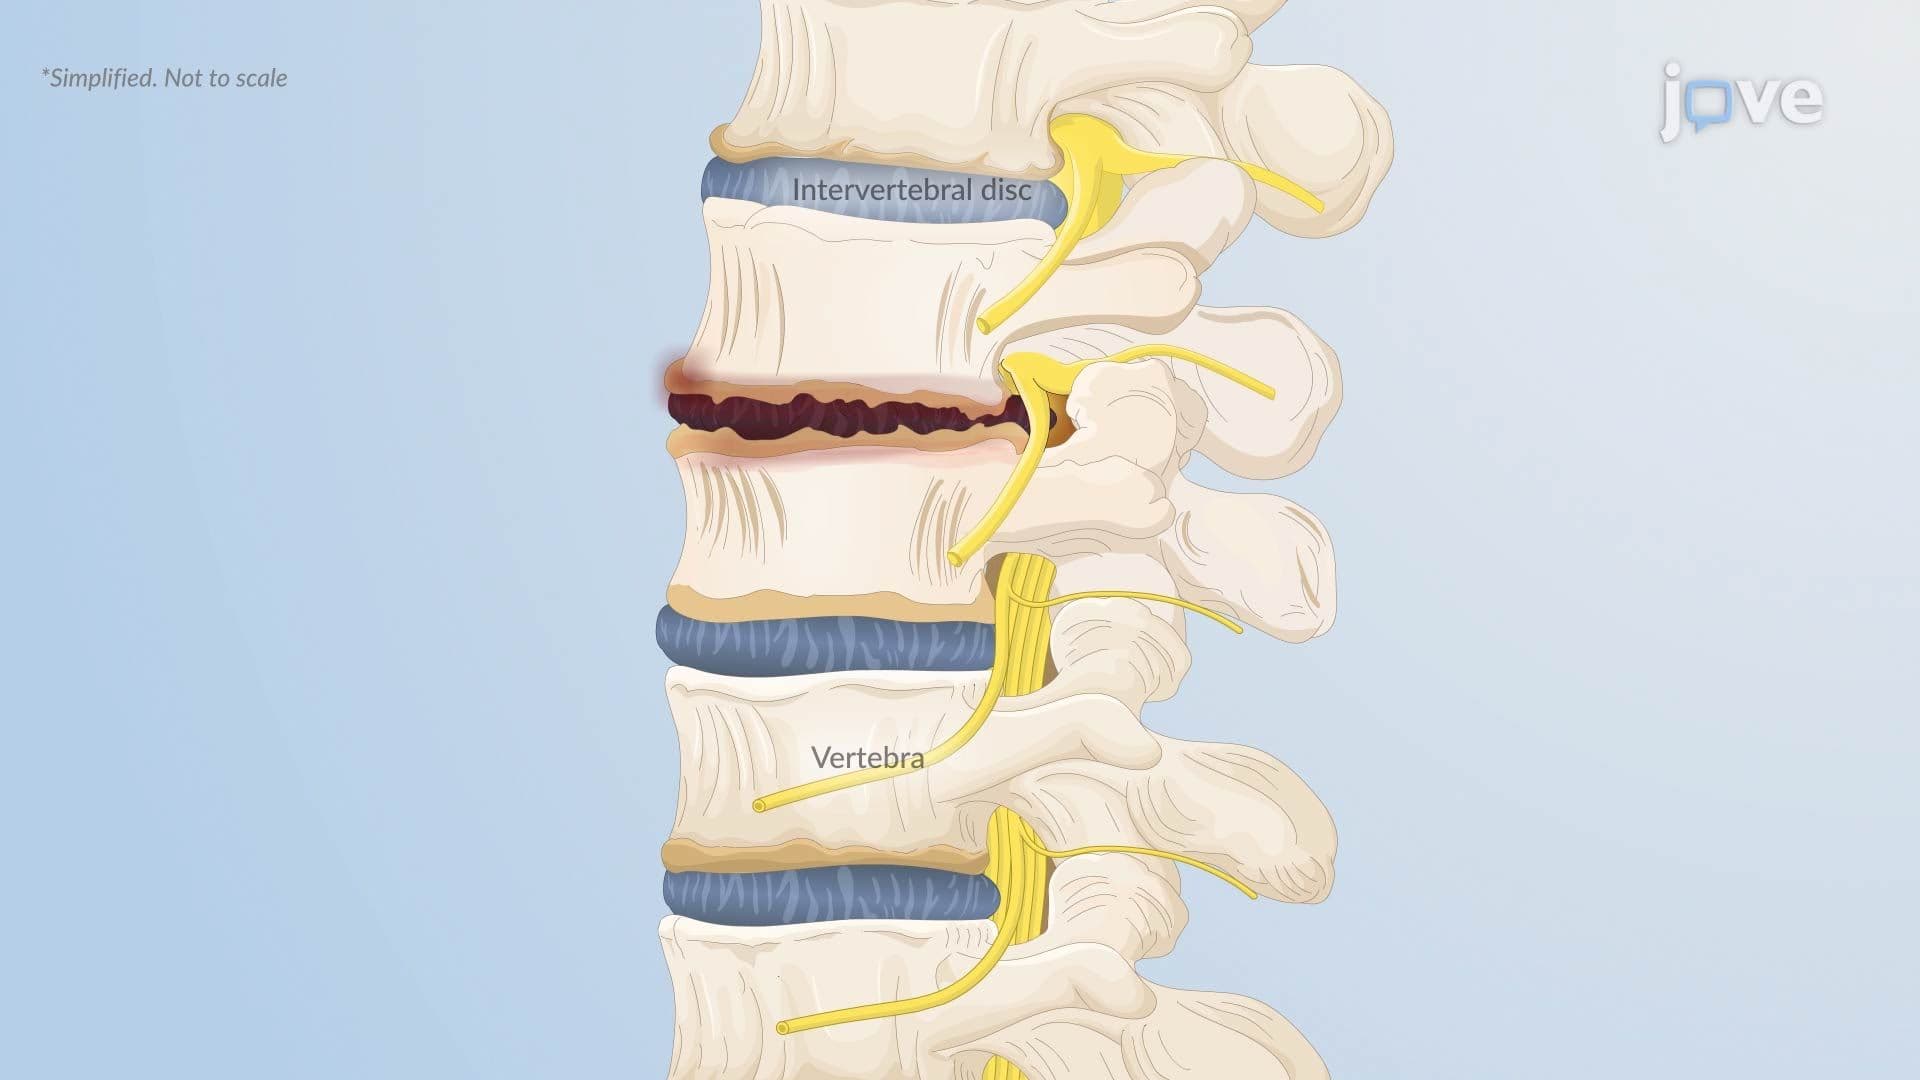
Herniated Intervertebral Disc l: Introduction
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology