Related Experiment Video
Updated: Jul 25, 2026

Cone Beam Intraoperative Computed Tomography-based Image Guidance for Minimally Invasive Transforaminal Interbody Fusion
Published on: August 6, 2019
Anterior Placement of Cages in Posterior Lumbar Interbody Fusion for Obtaining Good Lumbar Lordosis Formation
Daisuke Inoue1, Hideki Shigematsu2, Hiroaki Matsumori1
1Department of Orthopedic Surgery, Kashiba Asahigaoka Hospital, Kashiba, Japan.

Introduction:
Posterior lumbar interbody fusion (PLIF) is a common treatment for nerve root disease associated with lumbar foraminal stenosis or lumbar spondylolisthesis. At our institution, PLIF is usually performed with high-angle cages and posterior column osteotomy (PLIF with HAP). However, not all patients achieve sufficient segmental lumbar lordosis (SLL). This study determined whether the location of PLIF cages affect local lumbar lordosis formation.
Methods:
A total of 59 patients who underwent L4/5 PLIF with HAP at our hospital, using the same titanium control cage model, were enrolled in this cohort study. The mean ratio of the distance from the posterior edge of the cage to the posterior wall of the vertebral body/vertebral length (RDCV) immediately after surgery was 16.5%. The patients were divided into two groups according to RDCV <16.5% (group P) and ≥16.5% (group G). The preoperative and 6-month postoperative slip rate (%slip), SLL, local disk angle (LDA), ratio of disk height/vertebral height (RDV), 6-month postoperative RDCV, ratio of cage length/vertebral length (RCVL), and ratio of posterior disk height/anterior disk height at the fixed level (RPA) were evaluated via simple lumbar spine X-ray. The preoperative and 6-month postoperative Japanese Orthopedic Association (JOA) and low back pain visual analog scale (VAS) scores were also evaluated.
Results:
Groups G and P included 31 and 28 patients, respectively. The preoperative %slip, SLL, LDA, RDV, JOA score, and low back pain VAS score were not significantly different between the groups. In groups G and P, 6-month postoperative %slip, SLL, LDA, RDV, RDCV, RCVL, and RPA were 3.3% and 7.9%, 18.6° and 15.4°, 9.7° and 8.0°, 36.6% and 40.3%, 21.1% and 10.1%, 71.4% and 77.0%, and 56.1% and 67.7%, respectively. The 6-month postoperative SLL, LDA, RDV, RDCV, RCVL, and RPA significantly differed (p=0.03, 0.02, 0.02, <0.001, <0.001, and <0.001, respectively).
Conclusions:
Anterior PLIF cage placement relative to the vertebral body is necessary for good SLL in PLIF.
Related Concept Videos
 01:16
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
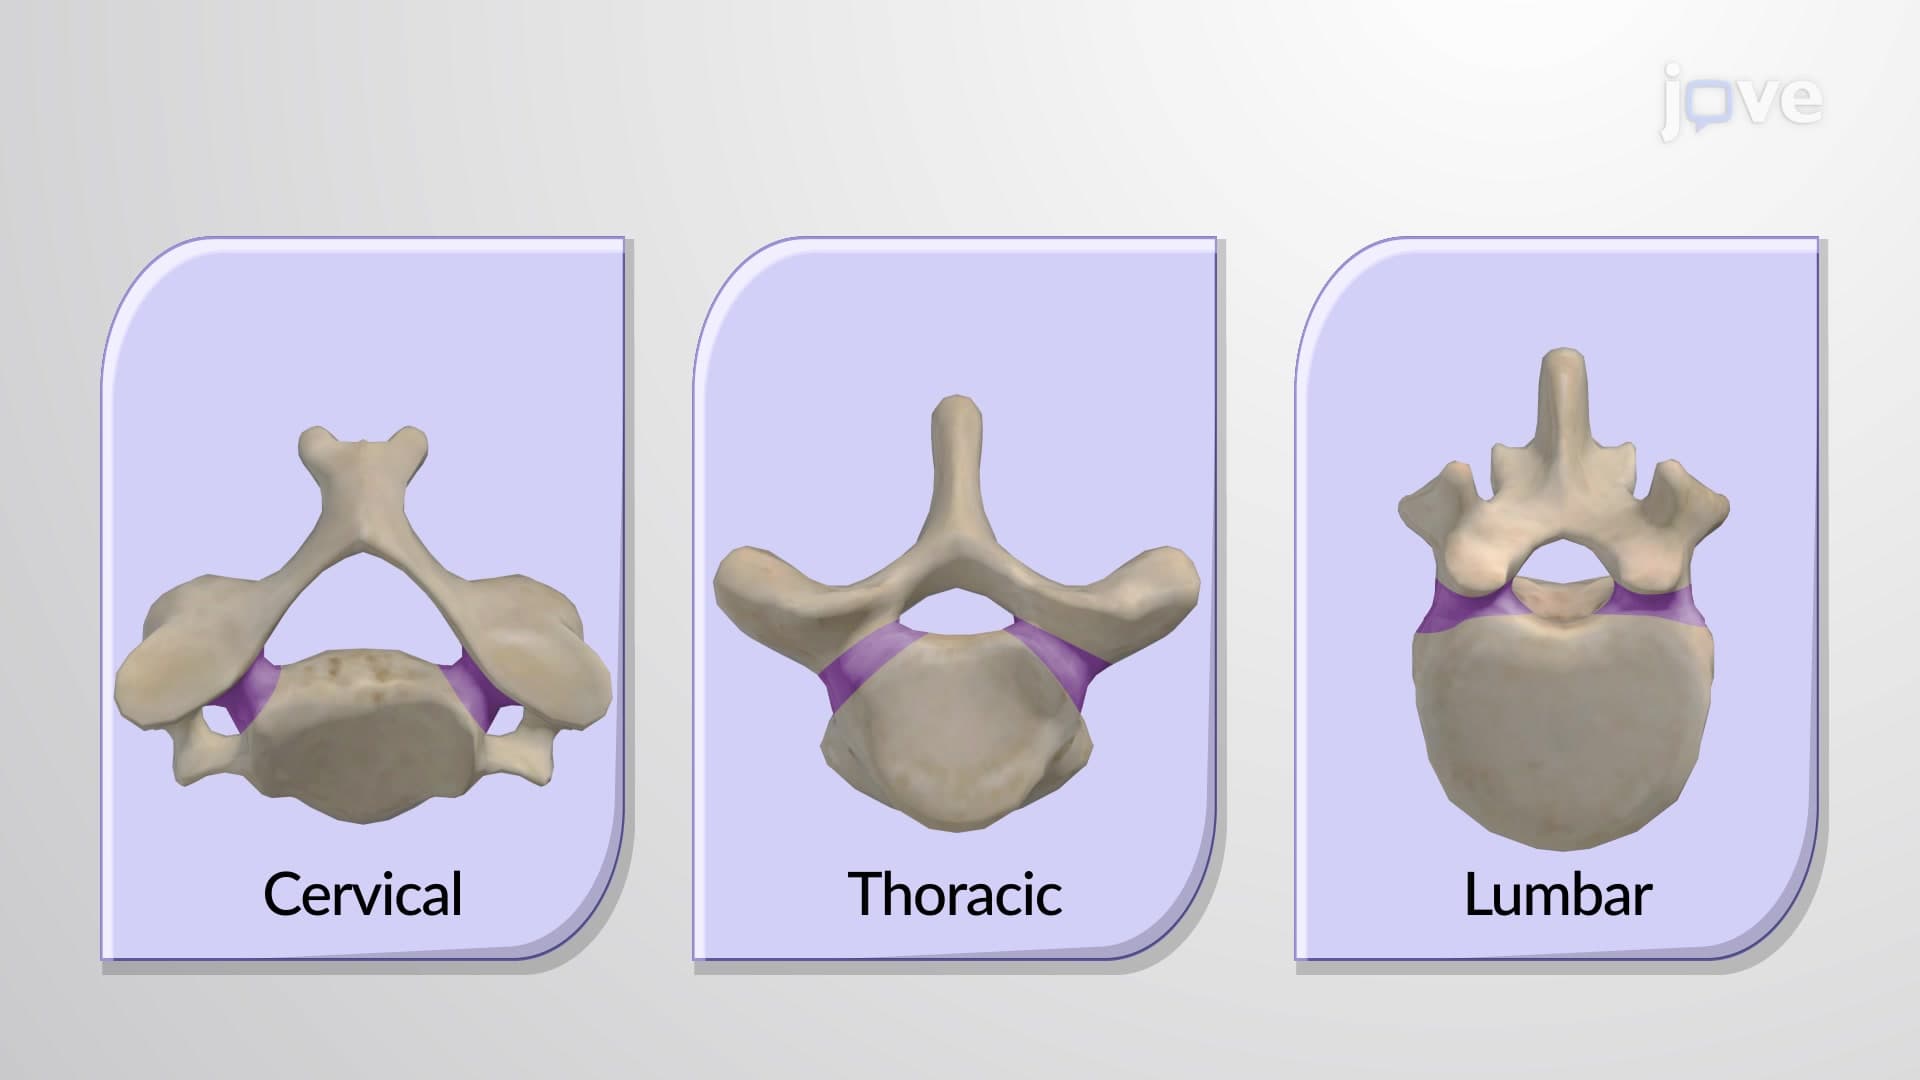 01:30
General Structure of a Vertebra
 01:16
Bones of the Lower Limb: Femur and Patella
 01:10
Bones of the Lower Limb: Tibia and Fibula
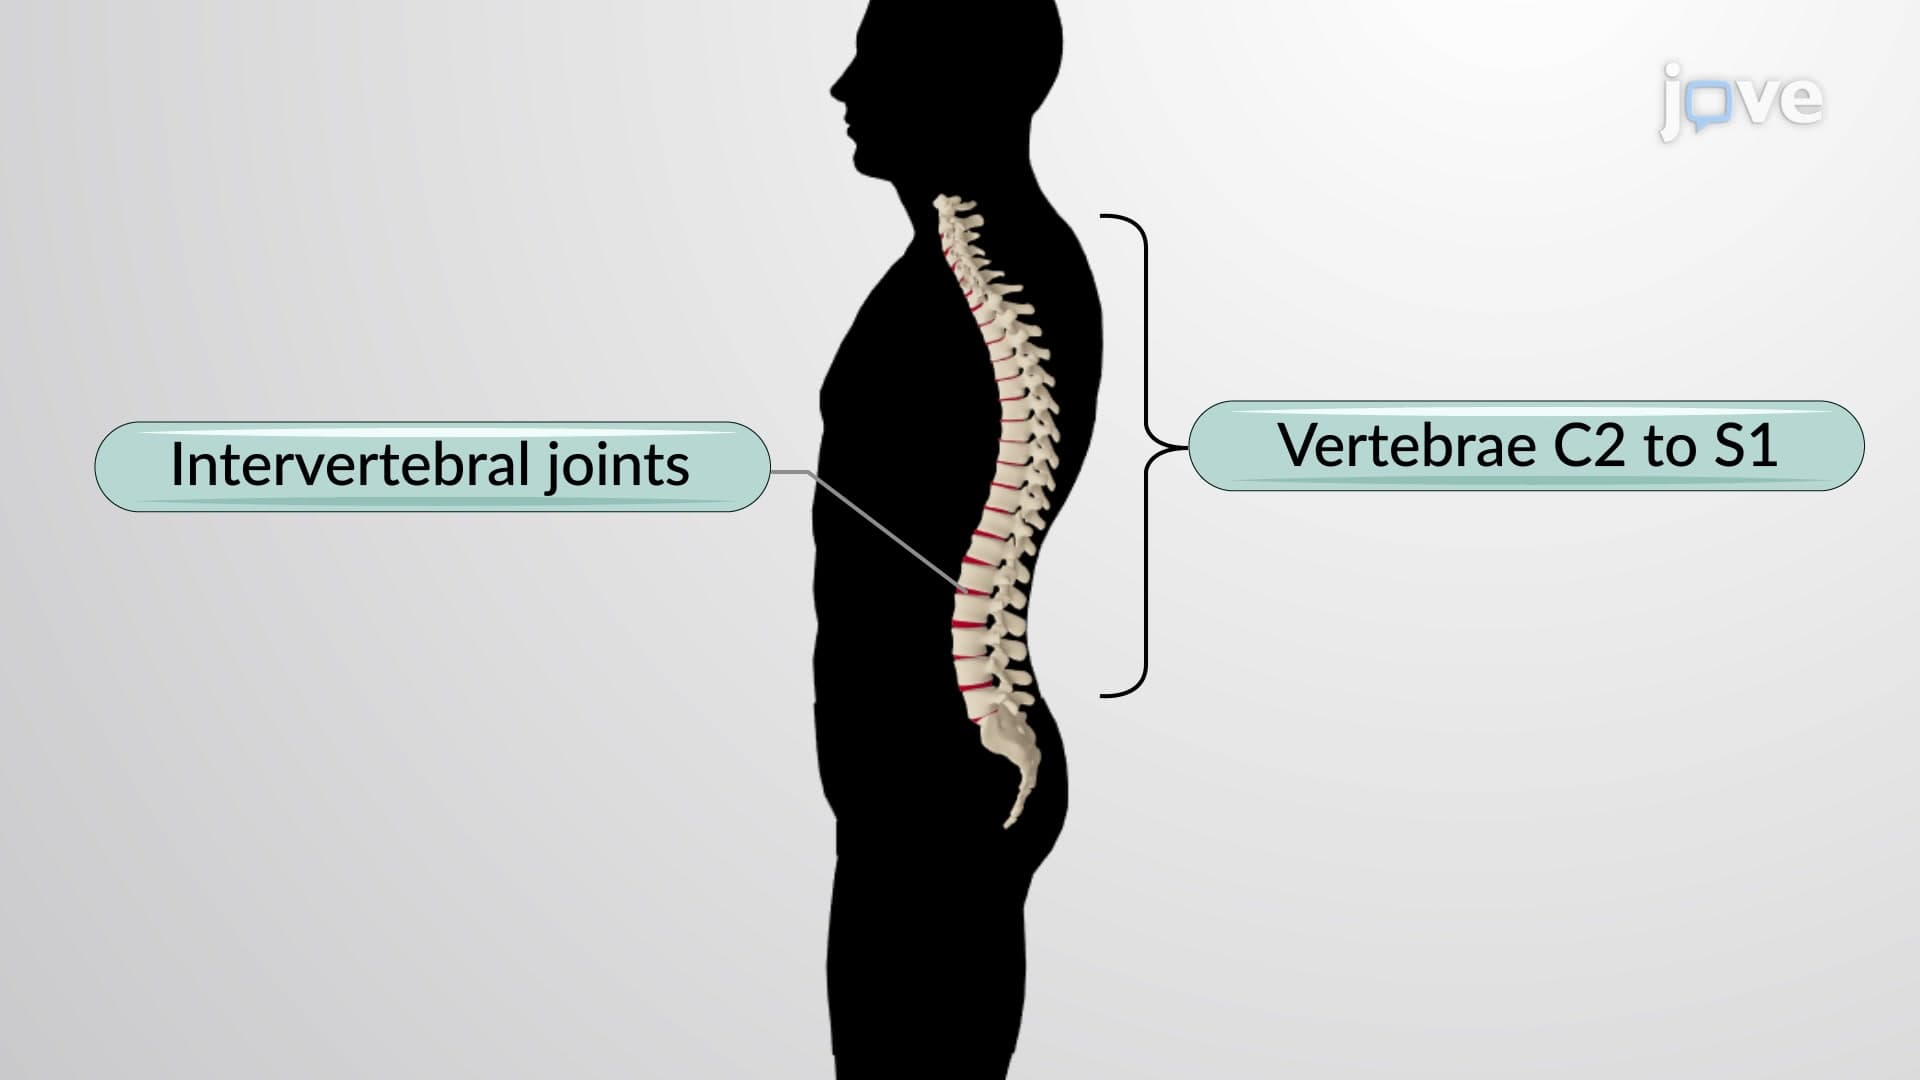 01:28
Articulations of the Vertebral Column
 01:10
Ankle Joint