Mitral valve repair using leaflet expansion and subpartial annuloplasty in children
Related Experiment Video
Updated: Jul 18, 2026
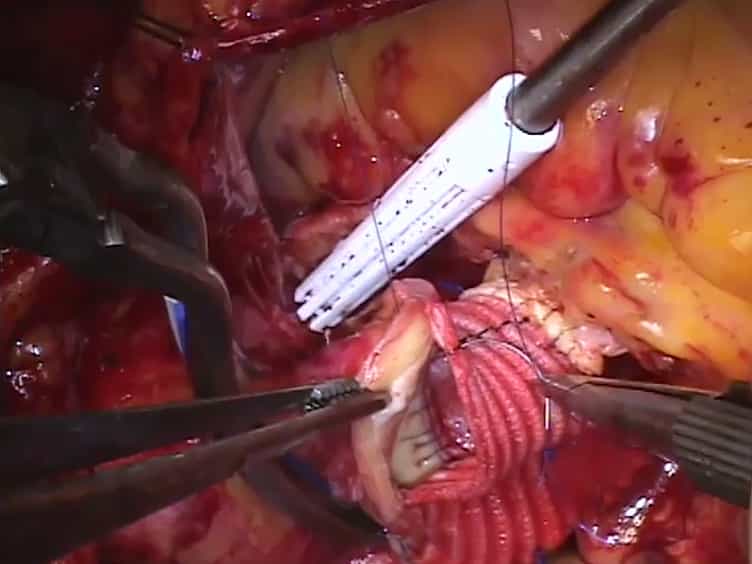
Standardized Technique of Aortic Valve Re-implantation for Valve-sparing Aortic Root Replacement
Published on: December 11, 2017
Per Wierup1,2, Jens Johansson Ramgren1, Johan Sjögren2
1Department of Pediatric Heart Surgery, Skane University Hospital, Lund, Sweden.

Objective:
Mitral valve reconstruction in the pediatric population is a challenge due to the frequent combination of annular dilatation and leaflet restriction and the need for growth. We present a novel strategy using leaflet expansion and subpartial annuloplasty with polytetrafluoroethylene reinforcement.
Methods:
From January 2014 through May 2021, 11 children aged 5 months to 14 years (median, 24 months) underwent elective mitral valve repair due to severe mitral valve regurgitation. The mitral valve abnormalities included congenital malformations (n = 7), postoperative leakage following commissurotomy (n = 1), and functional mitral valve regurgitation due to dilated cardiomyopathy (n = 3). Surgery consisted of leaflet expansions with autologous, untreated pericardium and subpartial annuloplasty with polytetrafluoroethylene reinforcement.
Results:
All children survived their surgeries with uneventful postoperative courses, except for 1 patient who needed an early reoperation to resolve a functional stenosis due to a spinnaker phenomenon. At discharge, mean gradient was 3.5 ± 3.9 mm Hg, with trivial mitral regurgitation in 9 patients (82%). All patients were alive and asymptomatic during the median follow-up of 3 years (range, 1-7 years). Their echocardiographic data showed a mean transmitral gradient of 4.4 ± 1.7 mm Hg and remained unchanged. Residual mitral valve regurgitation was trivial or mild in 9 patients (82%) and moderate in 2 patients (18%).
Conclusions:
Leaflet expansion with autologous pericardium and subpartial annuloplasty with polytetrafluoroethylene reinforcement for mitral regurgitation in the pediatric population gives stable and satisfactory results both early and at intermediate follow-up, permitting growth of the mitral valve.
Related Concept Videos
 01:27
Mitral Valve Prolapse I: Introduction
 01:22
Mitral Valve Prolapse II: Assessment and Management
 01:20
Mitral Regurgitation I: Introduction
 01:25
Mitral Regurgitation III: Medical Management
 01:22
Mitral Stenosis I: Introduction
 01:26
Mitral Stenosis III: Medical Management