Related Experiment Video
Updated: Jul 3, 2025

Assessment of Vascular Function in Patients With Chronic Kidney Disease
Published on: June 16, 2014
Urinary Prostaglandin E2 Excretion and the Risk of Cardiovascular and Kidney Disease
Frank Geurts1,2, Layal Chaker1,2, Anna C van der Burgh2
1Department of Internal Medicine, Erasmus Medical Center University Medical Center Rotterdam Rotterdam The Netherlands.

Background:
Inhibition of prostaglandin synthesis by nonsteroidal anti-inflammatory drugs is associated with cardiovascular mortality and kidney disease. This study hypothesizes that urinary prostaglandin E2 (PGE2) and PGE2 metabolite (PGEM) excretions are markers of cardiovascular and kidney health, because they reflect both systemic and kidney-derived PGE2 production.
Methods And Results:
PGE2 and PGEM were measured in spot urine samples from 2291 participants (≥55 years old) of the population-based Rotterdam Study. Urinary PGE2 and PGEM excretions were analyzed using linear regression analyses to identify cross-sectional associations with cardiovascular risk factors and baseline estimated glomerular filtration rate (eGFR). Longitudinal associations with cardiovascular mortality and kidney outcomes (eGFR <60 or <45 mL/min per 1.73 m2 and the composite outcome 40% eGFR loss or kidney failure) were assessed with Cox regression. Urinary PGE2 and PGEM excretions were higher with increasing age, lower eGFR, smoking, diabetes, and albuminuria. A 2-fold higher urinary PGE2 and PGEM excretion was associated with a higher risk of cardiovascular mortality (28 825 patient-years; 160 events; PGE2 hazard ratio [HR], 1.27, [95% CI, 1.06-1.54]; PGEM HR, 1.36 [95% CI, 1.10-1.67]). Higher PGE2 excretions were also associated with a higher risk of incident eGFR <60 mL/min per 1.73 m2 (31 530 person-years; 691 events; HR, 1.13 [95% CI, 1.02-1.25]) with similar HRs for the other kidney outcomes.
Conclusions:
Urinary PGE2 and PGEM excretions are novel markers for the presence and progression of cardiovascular and kidney disease. Future studies should address whether these associations are causal and can be targeted to improve cardiovascular and kidney outcomes.


Related Concept Videos
 01:28
Renal Drug Excretion: Tubular Secretion
 01:23
Treatment for Pulmonary Arterial Hypertension: Prostacyclin Receptor Agonists
These agonists bind to the IPR receptor situated on the plasma membrane of the pulmonary artery smooth muscle cells. This binding triggers a cascade of reactions known as the GS-AC-cAMP-PKA pathway. This pathway results in the relaxation of smooth muscle...
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...
 01:25
Renal Drug Excretion: Tubular Reabsorption
 01:15
Drug Elimination by Renal Route: Tubular Secretion
 01:15
Renal Drug Excretion: Overview
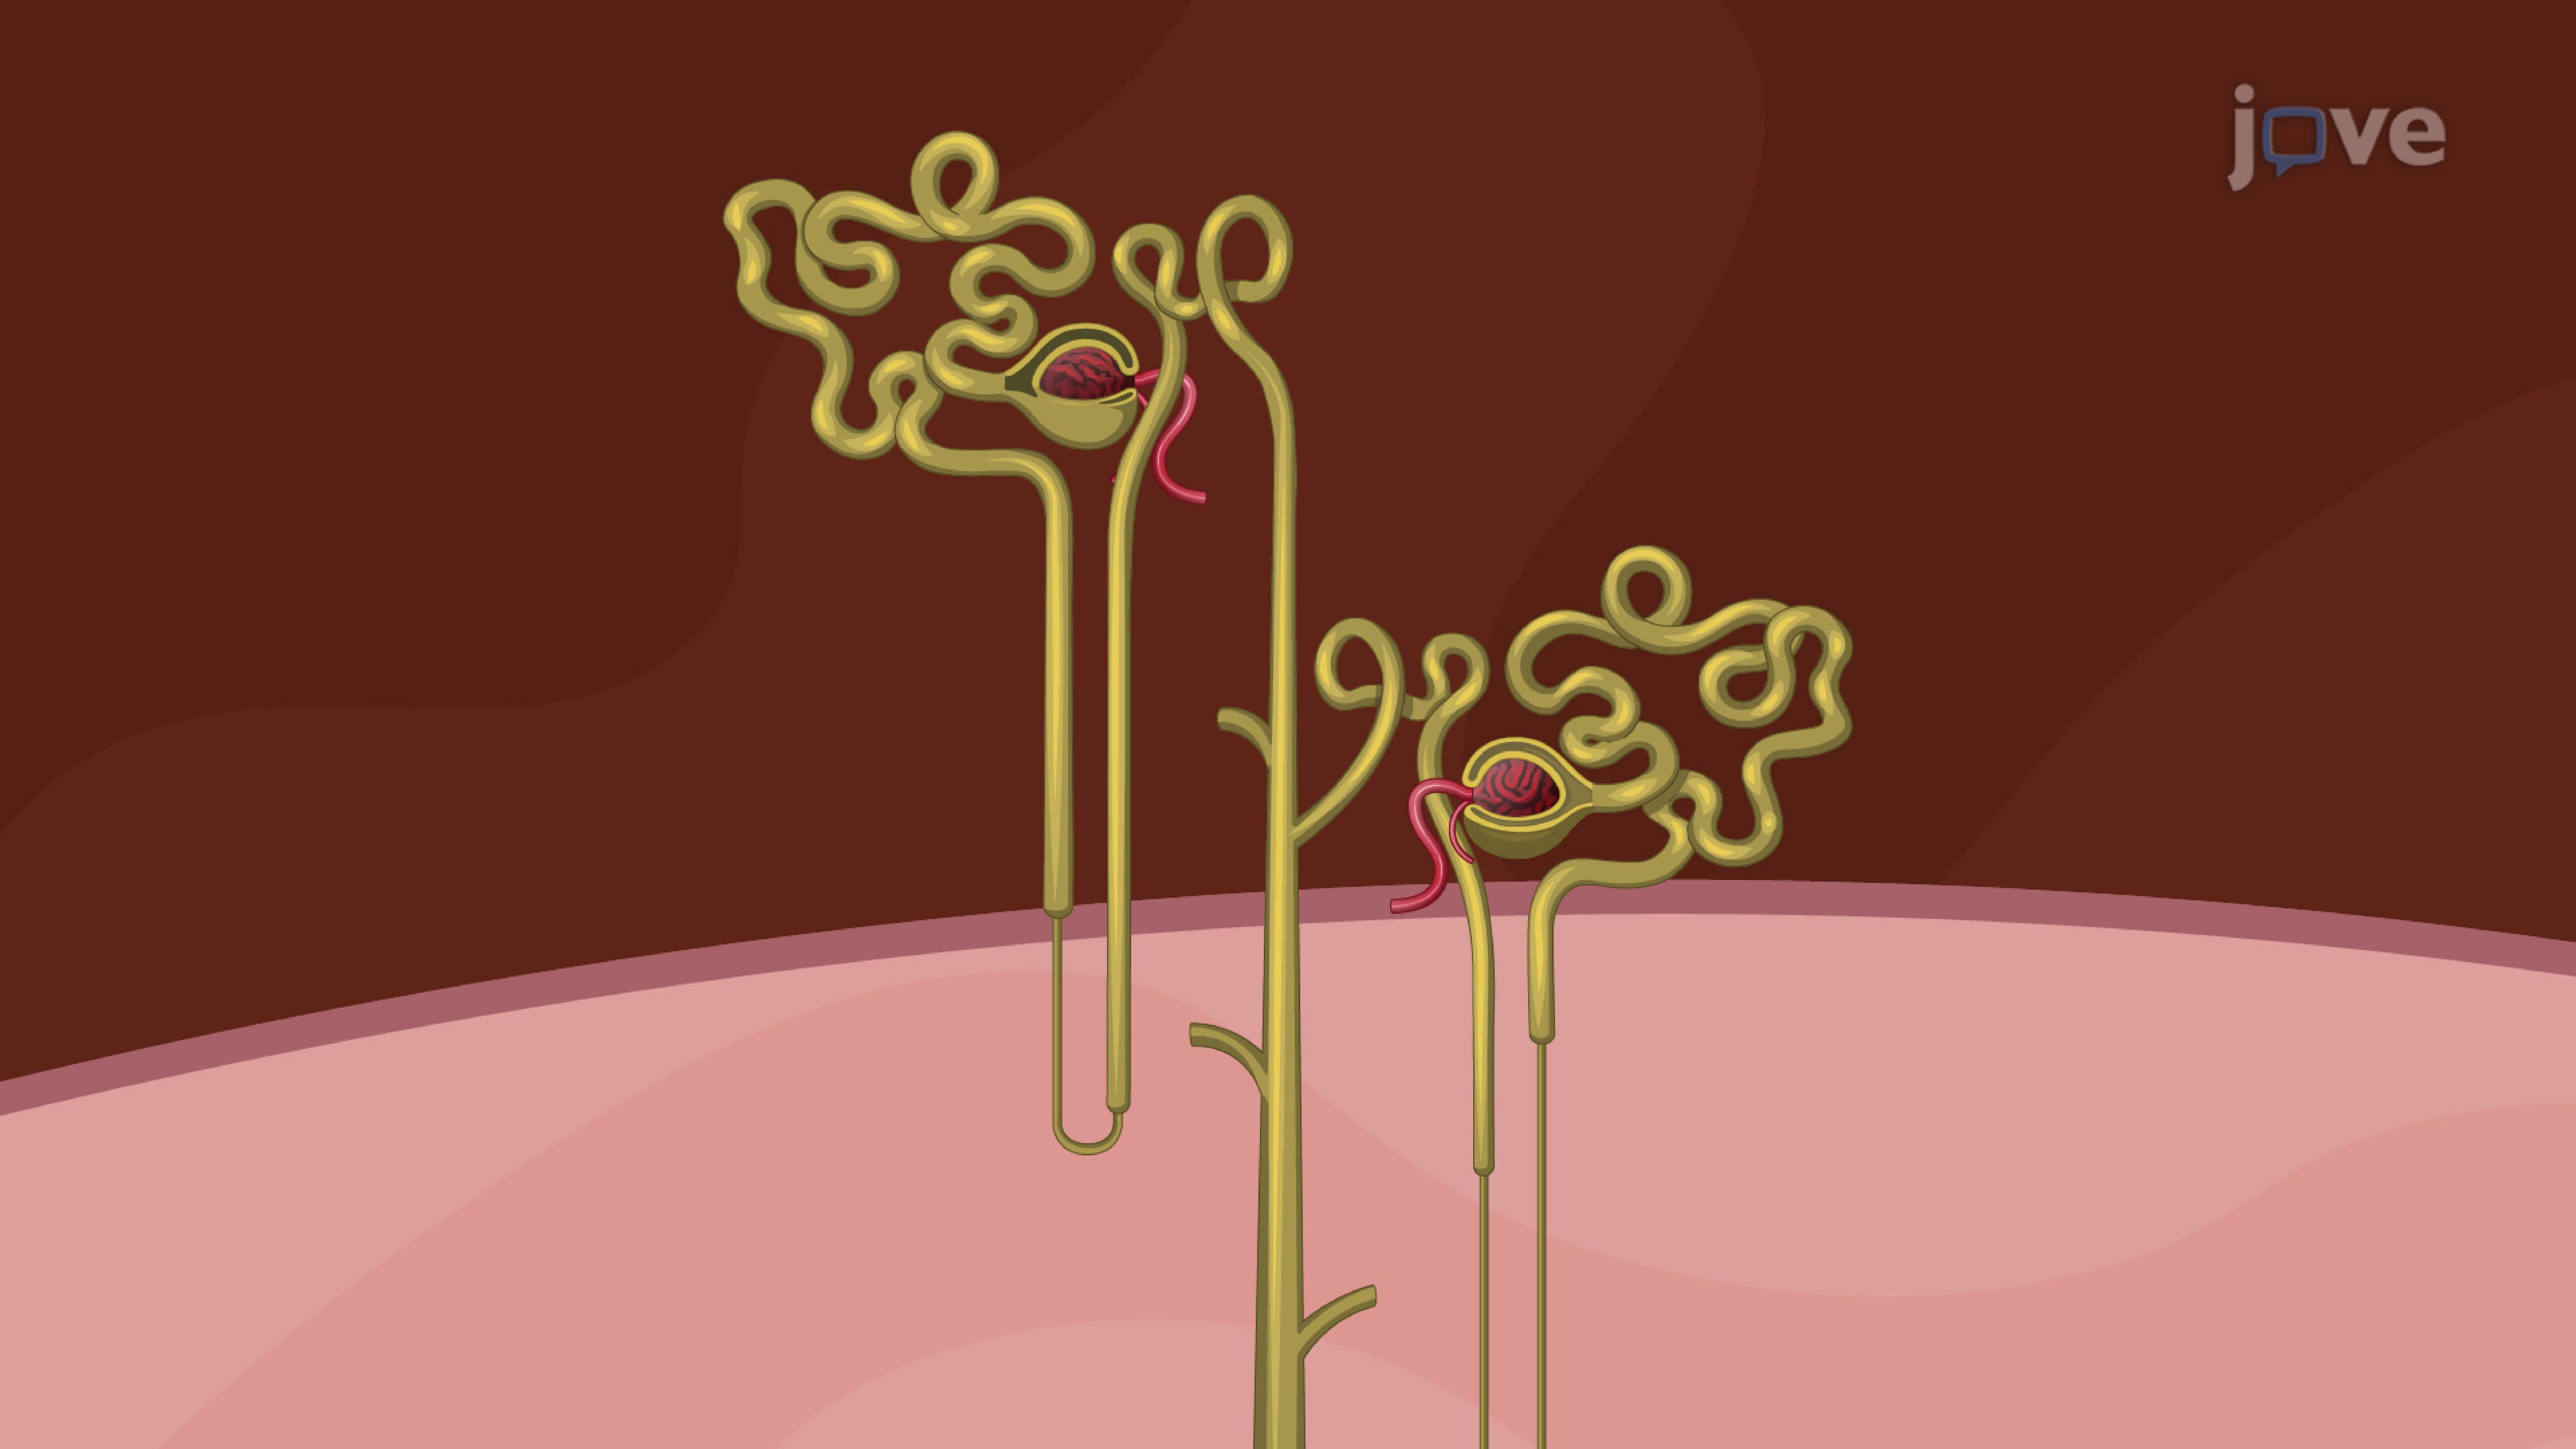
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...