Related Experiment Video
Updated: Jul 2, 2025


Methods for Studying Uterine Contributions to Pregnancy Establishment in an Ovariectomized Mouse Model
Published on: April 7, 2023
Luteal Phase Defects and Progesterone Supplementation
Lucas C Collins1, Luke A Gatta2, Sarah K Dotters-Katz3
1Medical Student (MS2), Duke University School of Medicine, 201 Trent Drive, Durham, NC.

Importance:
Luteal phase defects (LPDs), or an insufficiency of progesterone production during the luteal phase of the menstrual cycle, have been identified as a potential cause of recurrent pregnancy loss (RPL), but its exact contribution to RPL is not well-defined. In addition, the role of exogenous progesterone supplementation during pregnancy remains controversial.
Objective:
The goal of this review is to provide an updated, evidence-based summary of LPD, including prevalence and potential pathophysiologic mechanisms, and to explore the current controversies regarding progesterone supplementation for management and treatment of RPL.
Evidence Acquisition:
A literature review identified relevant research using a PubMed search, Cochrane summaries, review articles, textbook chapters, databases, and society guidelines.
Results:
Endogenous progesterone plays a crucial role in the first trimester of pregnancy, and therefore, insufficiency may contribute to RPL. However, the precise relationship between LPD and RPL remains unclear. Luteal phase defect is primarily a clinical diagnosis based on a luteal phase less than 10 days. Although there may be a possibility of incorporating a combined clinical and biochemical approach in defining LPD, the current lack of validated diagnostic criteria creates a challenge for its routine incorporation in the workup of infertility. Moreover, no treatment modality has demonstrated efficacy in improving fertility outcomes for LPD patients, including progesterone supplementation, whose inconsistent data do not sufficiently support its routine use, despite its minimal risk. It is imperative that women diagnosed with LPD should be worked up for other potential conditions that may contribute to a shortened luteal phase. Future work needs to focus on identifying a reproducible diagnostic test for LPD to guide treatment.
Conclusions And Relevance:
Currently, the perceived relationship between LPD and RPL is challenged by conflicting data. Therefore, patients with an abnormal luteal phase should undergo a thorough workup to address any other potential etiologies. Although supplemental progesterone is commonly utilized for treatment of LPD and RPL, inconsistent supporting data call for exogenous hormone therapy to be only used in a research setting or after a thorough discussion of its shortcomings.


Related Concept Videos
 01:27
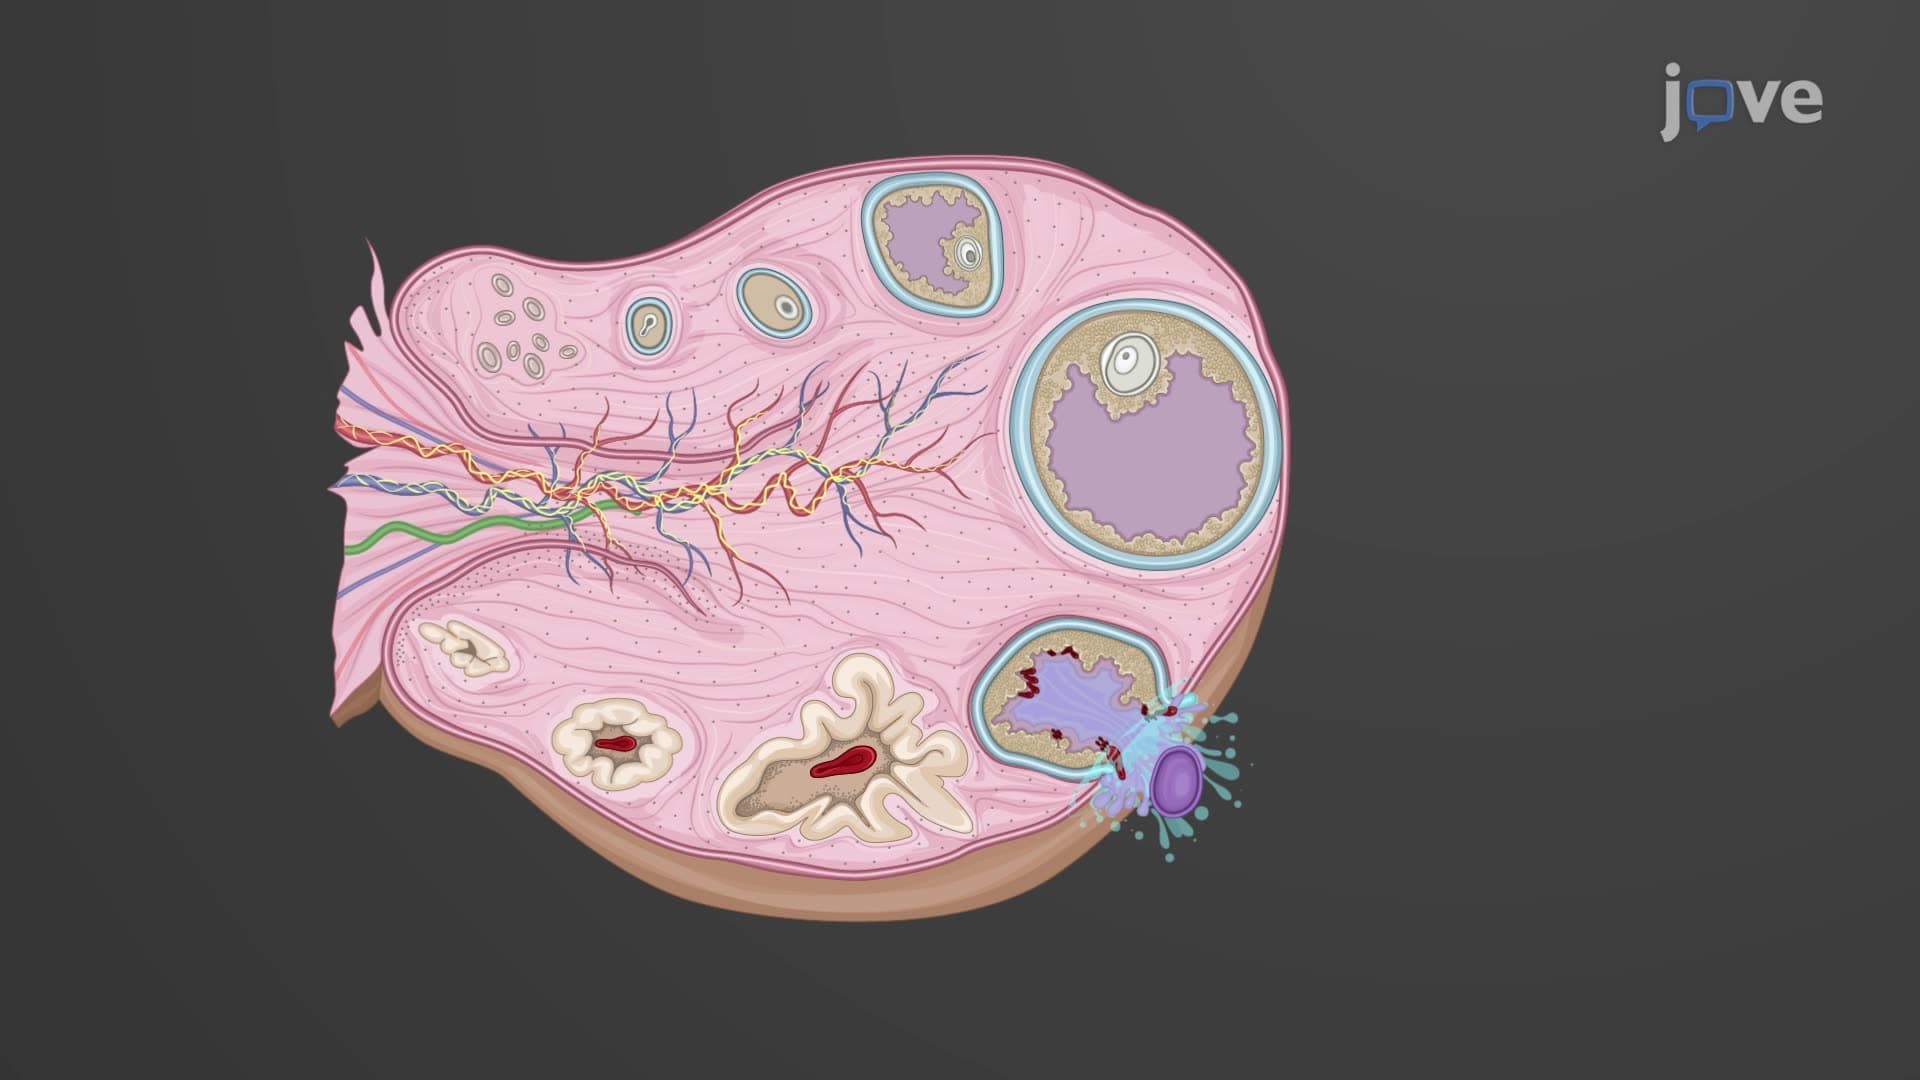
Ovarian Cycle
 01:20
Proliferative Phase
Notably, the stratum basale, the basal layer of the endometrium, including the basal parts of the uterine glands, remains unaffected by menstruation. Stem cells in this layer undergo mitosis, regenerating the stratum functionalis and thickening the...
 01:19
Secretory Phase
Following ovulation, the corpus luteum, a temporary endocrine structure, produces progesterone and estrogens. These hormones stimulate the growth and coiling of endometrial...
 01:18
Menses Phase
When fertilization does not occur, the corpus luteum deteriorates, causing a significant drop in the levels of estrogen and progesterone in the body. This hormonal decrease triggers the release of prostaglandins, which cause the uterine...
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH...
 01:24
Gonadal and Placental Hormones
In males, testosterone is the primary gonadal androgen. It plays a central role in the maturation of male reproductive organs — the penis and testes. Additionally, testosterone is instrumental in the development of secondary sexual characteristics — a deep voice as well as facial and pubic hair...