Related Experiment Video
Updated: Jul 2, 2025


Author Spotlight: Enhancing Upper Limb Rehabilitation in Stroke Patients Through Advanced Robotic and Neuromodulation Technologies
Published on: October 11, 2024
The effects of respiratory muscle training on respiratory function and functional capacity in patients with early
Yun-Shan Zhang1, Kai Zhang2, Lang Huang3
1Department of Rehabilitation Medicine, The First Affiliated Hospital of Guangxi Medical University, Nanning, 530021, China. 835969435@qq.com.

Background:
Respiratory muscle training is a continuous and standardized training of respiratory muscles, but the evidence of the effects on early stroke patients is not clear. This meta-analysis aimed to investigate the effects of respiratory muscle training on respiratory function and functional capacity in patients with early stroke.
Methods:
PubMed, Embase, PEDro, ScienceDirect, AMED, CINAHL, and China National Knowledge Infrastructure databases were searched from inception to December 8, 2023 for articles about studies that 1) stroke patients with age ≥ 18 years old. Early stroke < 3 months at the time of diagnosis, 2) respiratory muscle training, including inspiratory and expiratory muscle training, 3) the following measurements are the outcomes: respiratory muscle strength, respiratory muscle endurance, pulmonary function testing, dyspnea fatigue score, and functional capacity, 4) randomized controlled trials. Studies that met the inclusion criteria were extracted data and appraised the methodological quality and risk of bias using the Physiotherapy Evidence Database scale and the Cochrane Risk of Bias tool by two independent reviewers. RevMan 5.4 with a random effect model was used for data synthesis and analysis. Mean differences (MD) or standard mean differences (SMD), and 95% confidence interval were calculated (95%CI).
Results:
Nine studies met inclusion criteria, recruiting 526 participants (mean age 61.6 years). Respiratory muscle training produced a statistically significant effect on improving maximal inspiratory pressure (MD = 10.93, 95%CI: 8.51-13.36), maximal expiratory pressure (MD = 9.01, 95%CI: 5.34-12.69), forced vital capacity (MD = 0.82, 95%CI: 0.54-1.10), peak expiratory flow (MD = 1.28, 95%CI: 0.94-1.63), forced expiratory volume in 1 s (MD = 1.36, 95%CI: 1.13-1.59), functional capacity (SMD = 0.51, 95%CI: 0.05-0.98) in patients with early stroke. Subgroup analysis showed that inspiratory muscle training combined with expiratory muscle training was beneficial to the recovery of maximal inspiratory pressure (MD = 9.78, 95%CI: 5.96-13.60), maximal expiratory pressure (MD = 11.62, 95%CI: 3.80-19.43), forced vital capacity (MD = 0.87, 95%CI: 0.47-1.27), peak expiratory flow (MD = 1.51, 95%CI: 1.22-1.80), forced expiratory volume in 1 s (MD = 0.76, 95%CI: 0.41-1.11), functional capacity (SMD = 0.61, 95%CI: 0.08-1.13), while inspiratory muscle training could improve maximal inspiratory pressure (MD = 11.60, 95%CI: 8.15-15.05), maximal expiratory pressure (MD = 7.06, 95%CI: 3.50-10.62), forced vital capacity (MD = 0.71, 95%CI: 0.21-1.21), peak expiratory flow (MD = 0.84, 95%CI: 0.37-1.31), forced expiratory volume in 1 s (MD = 0.40, 95%CI: 0.08-0.72).
Conclusions:
This study provides good-quality evidence that respiratory muscle training is effective in improving respiratory muscle strength, pulmonary function, and functional capacity for patients with early stroke. Inspiratory muscle training combined with expiratory muscle training seems to promote functional recovery in patients with early stroke more than inspiratory muscle training alone.
Trial Registration:
Prospero registration number: CRD42021291918.
More Related Videos
 00:07
Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
 09:37
Evaluation of Respiratory Muscle Activation Using Respiratory Motor Control Assessment RMCA in Individuals with Chronic Spinal Cord Injury
Published on: July 19, 2013
Related Concept Videos
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:21
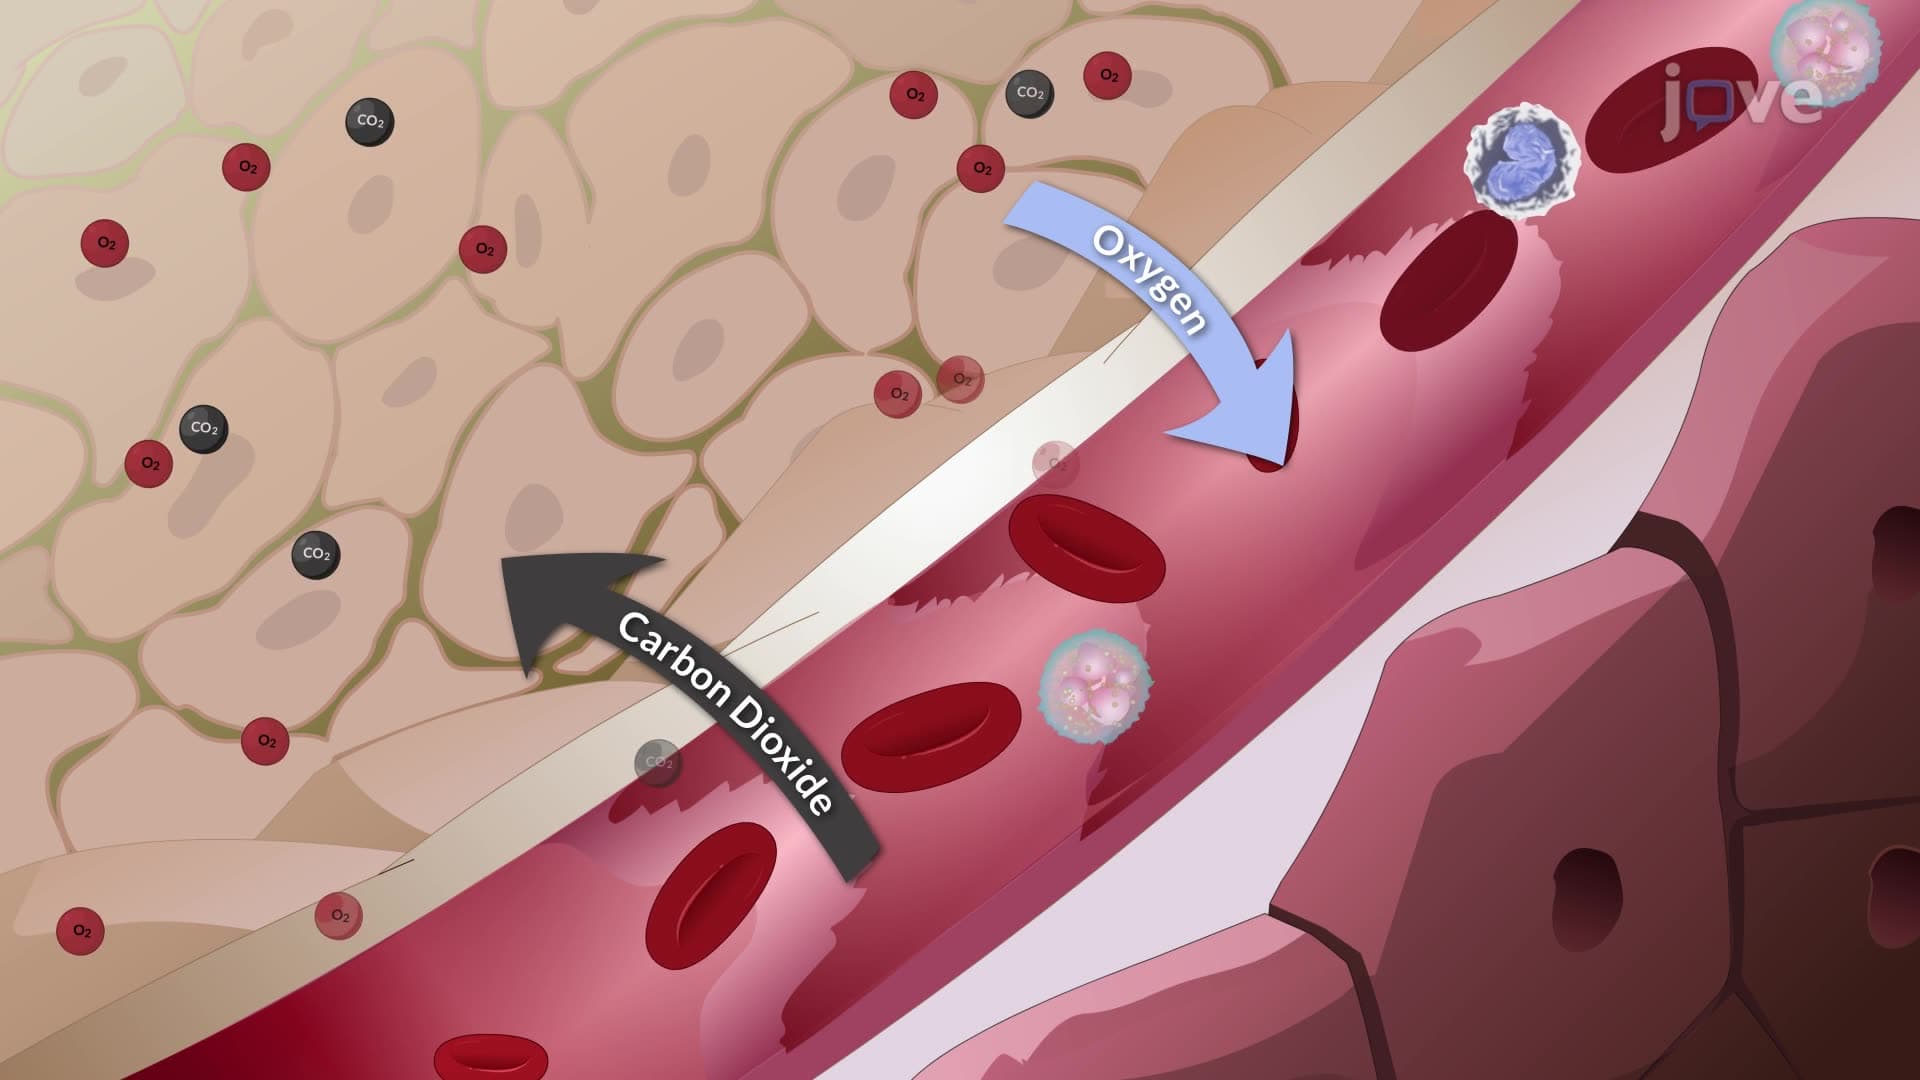
Mechanism of Breathing III: The Accessory Muscles
The respiratory system is a complex network that relies on primary respiratory muscles like the diaphragm, but also involves accessory muscles to enhance lung expansion and airflow during both inhalation and exhalation.
Enhancing Inhalation with Accessory Muscles:
Accessory muscles such as the sternocleidomastoid, scalene, intercostal, and abdominal muscles are crucial when additional respiratory effort is required, such as during deep...