Related Experiment Video
Updated: Jul 29, 2026
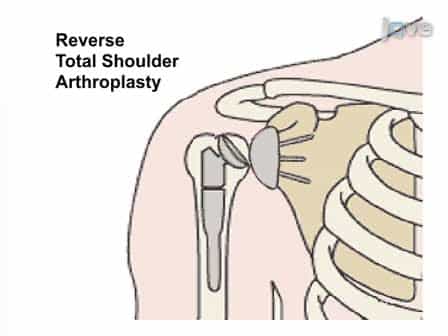

Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
High failure rate of 2-stage revision for the infected total elbow arthroplasty: a single institution's experience
Corey J Schiffman1, William Baker2, Daniel Kwak3
1Department of Orthopaedic Surgery, The University of Washington, Seattle, WA, USA.

Background:
Despite 2-stage revision being a common treatment for elbow prosthetic joint infection (PJI), failure rates are high. The purpose of this study was to report on a single institution's experience with 2-stage revisions for elbow PJI and determine risk factors for failed eradication of infection. The secondary purpose was to determine risk factors for needing allograft bone at the second stage of revision in the setting of compromised bone stock.
Methods:
We retrospectively analyzed all 2-stage revision total elbow arthroplasties (TEAs) performed for infection at a single institution between 2006 and 2020. Data collected included demographics and treatment course prior to, during, and after 2-stage revision. Radiographs obtained after explantation and operative reports were reviewed to evaluate for partial component retention and incomplete cement removal. The primary outcome was failed eradication of infection, defined as the need for repeat surgery to treat infection after the second-stage revision. The secondary outcome was the use of allograft for compromised bone stock during the second-stage revision. Risk factors for both outcomes were determined.
Results:
Nineteen patients were included. Seven patients (37%) had either the humeral or ulnar component retained during the first stage, and 10 (53%) had incomplete removal of cement in either the humerus or ulna. Nine patients (47%) had allograft strut used during reimplantation and reconstruction. Nine patients (47%) failed to eradicate the infection after 2-stage revision. Demographic data were similar between the repeat-infection and nonrepeat-infection groups. Six patients (60%) with retained cement failed compared with 3 patients (33%) with full cement removal (P = .370). Two patients (29%) with a retained component failed compared to 7 patients (58%) with full component removal (P = .350). Allograft was used less frequently when a well-fixed component or cement was retained, with no patients with a retained component needing allograft compared to 9 with complete component removal (P = .003). Three patients (30%) with retained cement needed allograft, compared with 6 patients (67%) who had complete cement removal (P = .179).
Conclusion:
Nearly half of the patients failed to eradicate infection after 2-stage revision. The data did not demonstrate a clear association between retained cement or implants and risk of recurrent infection. Allograft was used less frequently when a component and cement were retained, possibly serving as a proxy for decreased bone loss during the first stage of revision. Therefore, the unclear benefit of removing well-fixed components and cement need to be carefully considered as it likely leads to compromised bone stock that complicates the second stage of revision.
Insights
Two-stage revision for elbow prosthetic joint infection (PJI) has high failure rates. Retaining components or cement during revision surgery did not clearly increase infection recurrence but reduced allograft use, suggesting careful consideration of removal necessity.
Area of Science:
- Orthopedic surgery
- Infectious disease
- Arthroplasty revision
Background:
- Elbow prosthetic joint infection (PJI) presents a significant challenge, with high failure rates associated with the common two-stage revision treatment.
- Understanding risk factors for treatment failure and the need for bone grafting is crucial for improving outcomes.
Purpose of the Study:
- To report on a single institution's experience with two-stage revision for elbow PJI.
- To identify risk factors associated with failed infection eradication after two-stage revision.
- To determine risk factors for allograft bone use during the second stage of revision in cases of compromised bone stock.
Main Methods:
- Retrospective analysis of two-stage revision total elbow arthroplasties (TEAs) for infection (2006-2020).
- Data collection included demographics, treatment course, and review of radiographs/operative reports for component/cement retention.
- Primary outcome: failed infection eradication; Secondary outcome: allograft use; Risk factor analysis performed.
Main Results:
- Nearly half (47%) of patients failed to eradicate infection after two-stage revision.
- Component or cement retention did not show a statistically significant association with recurrent infection.
- Allograft use was significantly lower when components or cement were retained (P=.003 for component retention).
Conclusions:
- Two-stage revision for elbow PJI has a high failure rate, with nearly half of patients experiencing recurrent infection.
- The decision to retain or remove well-fixed components and cement requires careful consideration, as removal may compromise bone stock.
- Retaining components/cement may reduce the need for allograft, potentially indicating less bone loss during the initial stage.